
 한국어
 English
 日本語
 中文(简体)
 Viewing now
Zejula 100 mg Tablet (Niraparib tosylate monohydrate)
Niraparib Tosylate Monohydrate 159.3mg
Tablet · Prescription medication
Takeda Pharmaceutical Co., Ltd.
MFDS item code 202401351 · Approved 2024.05.31 · Insurance code 696300760
Maintenance monotherapy for platinum-responsive ovarian cancer and recurrent ovarian cancer (such as fallopian tube cancer)
This medicine is used as a single-agent maintenance therapy for patients with ovarian cancer, tubal cancer, or primary peritoneal cancer who have responded to first-line platinum-based chemotherapy. It is also utilized as a single-agent maintenance therapy for platinum-sensitive recurrent high-grade serous ovarian cancer patients who have responded to second-line or higher platinum-based chemotherapy. It helps to safely maintain therapy in specific situations related to ovarian cancer, continuing to improve the treatment effect for patients.
The recommended starting dose of this medicine is 200 mg (two 100mg tablets) administered orally once daily. However, for patients weighing at least 77kg and with a platelet count of at least 150,000/µl, the recommended starting dose is 300 mg (three 100mg tablets) administered orally once daily. For first-line maintenance treatment of ovarian cancer, patients should start treatment with this medicine within 12 weeks after their most recent platinum-based chemotherapy. For maintenance treatment of recurrent ovarian cancer after second-line or later therapy, patients should start treatment with this medicine within 8 weeks after their most recent platinum-based chemotherapy. This medicine should be continued until disease progression or unacceptable toxicity occurs. This medicine should be taken at approximately the same time each day. Do not chew, crush, or split the tablets before swallowing them whole. This medicine may be taken with food or on an empty stomach. Taking it at bedtime may help manage nausea. If you miss a dose of this medicine, do not take the missed dose; take the next dose at the regularly scheduled time. If you vomit or miss a dose of this medicine, do not take an additional dose. To manage adverse reactions, consider treatment interruption, dose reduction, or temporary discontinuation. Recommended dose modifications according to adverse reactions are presented in Tables 1, 2, and 3 Starting dose 200 mg/day (two 100mg tablets) 300 mg/day (three 100mg tablets) First dose reduction 100 mg/day 200 mg/day (two 100mg tablets) Second dose reduction Discontinue the medicine 100 mg/daya aIf a further dose reduction to below 100 mg/day is required, discontinue treatment with this medicine. Persistent nonhematologic adverse reactions of CTCAE* Grade ≥ 3 despite medical management ․ Withhold treatment with this medicine for up to 28 days or until the adverse reaction resolves. ․ Resume treatment with this medicine at a reduced dose according to Table 1. If a patient experiences a treatment-related adverse reaction of CTCAE ≥ Grade 3 that persists for more than 28 days while receiving 100 mg of this medicine once daily Discontinue the medicine. Monitor complete blood counts weekly during the first month of treatment, monthly for the next 11 months, and periodically thereafter. Platelet count <100,000/μL First occurrence: ․ Withhold treatment with this medicine for up to 28 days and monitor blood counts weekly until the platelet count returns to ≥100,000/μL. ․ Resume treatment with this medicine at the same or a reduced dose according to Table 1. ․ If the platelet count falls to <75,000/μL, resume treatment at a reduced dose. Second occurrence: ․ Withhold treatment with this medicine for up to 28 days and monitor blood counts weekly until the platelet count returns to ≥100,000/μL. ․ Resume treatment with this medicine at a reduced dose according to Table 1. ․ If the platelet count does not return to an acceptable level within 28 days after treatment interruption, or if the patient has already had the dose reduced to 100 mg once daily, discontinue treatment with this medicine.* Neutrophil count <1,000/μL or hemoglobin <8 g/dL ․ Withhold treatment with this medicine for up to 28 days and monitor blood counts weekly until the neutrophil count returns to ≥1,500/μL or the hemoglobin level returns to ≥9 g/dL. ․ Resume treatment with this medicine at a reduced dose according to Table 1. ․ If the neutrophil count and/or hemoglobin level does not return to an acceptable level within 28 days after treatment interruption, or if the patient has already had the dose reduced to 100 mg once daily, discontinue treatment with this medicine.* Hematologic adverse reactions requiring transfusion ․ Platelet transfusion should be considered for patients with a platelet count of ≤10,000/μL. If other risk factors are present, such as concomitant use of anticoagulants or antiplatelet agents, consider discontinuing these medicines and/or transfusing at a higher platelet count. ․ Resume treatment with this medicine at a reduced dose. *If myelodysplastic syndrome or acute myeloid leukemia (MDS/AML) is confirmed, permanently discontinue treatment with this medicine. For patients with moderate hepatic impairment, administer a starting dose of this medicine of 200mg once daily. Monitor for hepatotoxicity and reduce the dose further if necessary.
This medication can cause serious blood disorders such as myelodysplastic syndrome and acute myeloid leukemia, so blood status should be periodically monitored during treatment. It may harm the fetus during pregnancy, thus women of childbearing age should ensure effective contraception while taking this medication and for 6 months after its discontinuation. This medication should not be used in patients with allergies to its components or specific genetic disorders such as lactose intolerance. During treatment, various side effects such as nausea, thrombocytopenia, anemia, fatigue, constipation, myalgia, and vomiting may occur; if symptoms worsen, patients must promptly notify healthcare professionals. Dosage adjustment or discontinuation may be necessary based on blood test results, especially if platelet counts are low or if severe anemia symptoms occur. Patients with hypertension or cardiovascular diseases should frequently monitor their blood pressure and heart rate while taking this medication and receive appropriate treatment if necessary. Reversible posterior leukoencephalopathy syndrome, a rare neurological effect may occur, requiring immediate hospital visits if there are headaches, vision changes, or changes in mental state. Caution is needed when driving or operating machinery as fatigue or dizziness may occur due to this medication. Pregnant or breastfeeding women should avoid this medication; it is recommended to discontinue breastfeeding while taking this medication. Patients with impaired kidney or liver function may require dosage adjustment based on the physician's instructions. There is no specific antidote for overdose, and treatment will be symptomatic based on the patient's condition. This medication should be kept out of reach of children, and expired medications should not be used.
Myelodysplastic syndromes, acute myeloid leukemia, nausea, thrombocytopenia, anemia, fatigue, constipation, myalgia, abdominal pain, vomiting, neutropenia, appetite loss, leukopenia, insomnia, headache, dyspnea, rash, diarrhea, hypertension, cough, dizziness, acute kidney injury, urinary tract infection, magnesium deficiency, intestinal obstruction, bowel perforation, pleural effusion, pancytopenia, hypersensitivity, reversible posterior leukoencephalopathy syndrome, confusion, stupor, hallucinations, cognitive impairment, non-infectious pneumonia, photosensitivity, hypertensive crisis, palpitations, mucositis, stomatitis, dyspepsia, dry mouth, low back pain, dysgeusia, anxiety, nasopharyngitis, tachycardia, peripheral edema, hypokalemia, bronchitis, conjunctivitis, increased gamma-glutamyl transferase, increased serum creatinine, increased serum alkaline phosphatase, weight loss, depression, nosebleeds
Not everyone experiences these, and they can vary from person to person.
This medication should be stored in a tightly sealed container to prevent exposure to air or moisture. It is important to maintain storage temperatures between 15 to 30 degrees Celsius.
This medication is a gray oval film-coated tablet engraved with the number '100' on one side and 'Zejula' on the other side.
30 tablets/box [10 tablets/PTPX3]
Even with the same ingredient, strength, dosage form and how it is taken can differ.
Viewing nowNiraparib Tosylate Monohydrate 159.3mg
Tablet · Prescription medication
Takeda Pharmaceutical Co., Ltd.
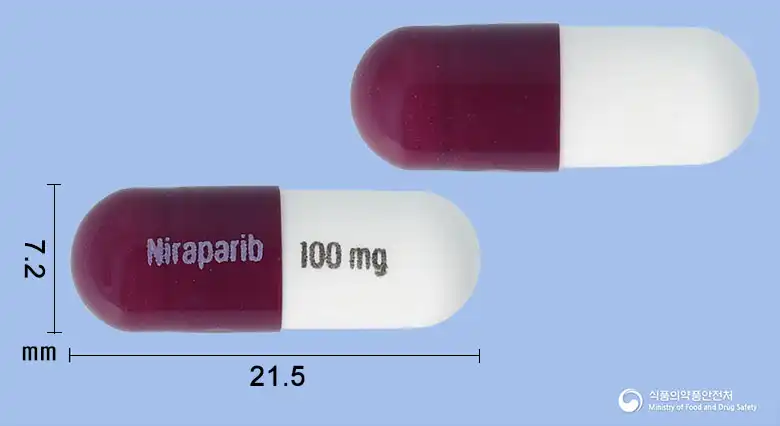
Niraparib Tosylate Monohydrate 159.4mg
Hard capsule · Prescription medication
Takeda Korea Pharmaceutical Co., Ltd.
Even with the same ingredient, the dose and directions can differ by strength and dosage form. Talk to a doctor or pharmacist before switching from a medication you are already taking.
No questions yet.
For anything that needs medical judgment, consult a doctor or pharmacist.
This drug information is based on data provided by the Korea Ministry of Food and Drug Safety.
Consult a doctor or pharmacist for accurate dosage, administration, and usage instructions.