
 한국어
 English
 日本語
 中文(简体)
 Viewing now
Rixisaban Tablet 30 mg (Edoxaban Tosilate Hydrate)
Edoxaban Tosylate Hydrate 40.41mg
Tablet · Prescription medication
Shinil Pharmaceutical Co., Ltd.
MFDS item code 202301250 · Approved 2023.04.14
Prevention of stroke and systemic embolism; treatment and prevention of recurrence of deep vein thrombosis and pulmonary embolism
This medication is used to reduce the risk of stroke and systemic embolism in patients with non-valvular atrial fibrillation. It also treats venous thromboembolism and pulmonary embolism and reduces the risk of recurrence of these diseases. It helps to safely prevent and treat thrombotic disorders.
This medicine should be taken with water, with or without food. 1. Adults 1) Reduction of the risk of stroke and systemic embolism in patients with nonvalvular atrial fibrillation • Body weight ≤ 60kg: The recommended dose of this medicine is 30mg once daily. • Body weight > 60kg: The recommended dose of this medicine is 60mg once daily. However, for patients with one or more of the following factors, the recommended dose of this medicine is 30mg once daily. ‣ Moderate to severe renal impairment (15 ≤ CrCL ≤ 50mL/min) ‣ Concomitant use of P-gp inhibitors (cyclosporine, dronedarone, erythromycin, ketoconazole) For elderly patients at high risk of bleeding, a dose of 15mg once daily may be used depending on age and condition. (See section '9. Administration to the elderly' under Precautions for Use.) 2) Treatment of deep vein thrombosis and pulmonary embolism/reduction of the risk of recurrent deep vein thrombosis and pulmonary embolism Administer this medicine after at least 5 days of parenteral anticoagulant use. • Body weight ≤ 60kg: The recommended dose of this medicine is 30mg once daily. • Body weight > 60kg: The recommended dose of this medicine is 60mg once daily. However, for patients with one or more of the following factors, the recommended dose of this medicine is 30mg once daily. ‣ Moderate to severe renal impairment (15 ≤ CrCL ≤ 50mL/min) ‣ Concomitant use of P-gp inhibitors (cyclosporine, dronedarone, erythromycin, ketoconazole) 2. Switching medications 2.1 Switching from another medicine to this medicine 1) Switching from a vitamin K antagonist to this medicine Discontinue vitamin K antagonist therapy and start this medicine when the International Normalized Ratio (INR) is 2.5 or lower. 2) Switching from an oral anticoagulant other than a vitamin K antagonist (dabigatran, rivaroxaban, apixaban) to this medicine Discontinue oral anticoagulant therapy and start this medicine at the time of the next scheduled dose of the oral anticoagulant. 3) Switching from a parenteral anticoagulant to this medicine (1) Low molecular weight heparin (LMWH) Discontinue LMWH and start this medicine at the time of the next scheduled LMWH dose. (2) Unfractionated heparin (UFH) Discontinue intravenous UFH infusion and start this medicine 4 hours later. 2.2 Switching from this medicine to another medicine 1) Switching from this medicine to a vitamin K antagonist Inadequate anticoagulation may occur when switching from this medicine to a vitamin K antagonist. Adequate anticoagulant effect should be maintained continuously while switching to another anticoagulant. (1) Oral option For patients receiving 60mg of this medicine, administer 30mg of this medicine once daily together with an appropriate dose of a vitamin K antagonist. For patients receiving 30mg of this medicine, administer 15mg of this medicine once daily together with an appropriate dose of a vitamin K antagonist. During the first 14 days of concomitant administration, it is recommended that INR be measured at least 3 times; measurements should be taken before administration of this medicine to minimize its effect on INR measurement. Once INR ≥ 2.0 is stably achieved, discontinue this medicine and continue vitamin K antagonist therapy. (2) Parenteral option Discontinue this medicine and administer a parenteral anticoagulant and a vitamin K antagonist at the time of the next scheduled dose of this medicine. Once INR ≥ 2.0 is stably achieved, discontinue the parenteral anticoagulant and continue vitamin K antagonist therapy. 2) Switching from this medicine to an oral anticoagulant other than a vitamin K antagonist (dabigatran, rivaroxaban, apixaban) Discontinue this medicine and start the oral anticoagulant at the time of the next scheduled dose of this medicine. 3) Switching from this medicine to a parenteral anticoagulant Discontinue this medicine and start the parenteral anticoagulant at the time of the next scheduled dose of this medicine. 3. Patients with renal impairment No dose adjustment of this medicine is necessary in patients with mild renal impairment (50 < CrCL ≤ 80mL/min). The recommended dose of this medicine is 30mg once daily in patients with moderate to severe renal impairment (15 ≤ CrCL ≤ 50mL/min). For the reduction of the risk of stroke and systemic embolism in patients with nonvalvular atrial fibrillation, a dose of 15mg once daily should be considered, depending on age and condition, for elderly patients at high risk of bleeding with creatinine clearance of 15 ≤ CrCL < 30 mL/min (see section '9. Administration to the elderly' under Precautions for Use). 4. If you forget to take this medicine If you forget to take this medicine, take it as soon as possible on the same day, and take the next dose the following day according to the recommended dosage and administration. Do not take twice the recommended daily dose to make up for a missed dose. 5. Patients who cannot swallow tablets For patients who cannot swallow tablets, this medicine may be crushed immediately before use, mixed with water or a beverage such as applesauce, and administered orally. Alternatively, this medicine may be crushed, suspended in a small amount of water, and administered through a nasogastric tube, followed by flushing the tube with water. The crushed medicine is stable in water and applesauce for up to 4 hours.
This medication may increase the risk of bleeding, leading to serious hemorrhagic events, and should be used with caution in patients at high risk of bleeding. If a fatal bleeding event occurs, the medication should be stopped immediately and the site of bleeding should be promptly assessed. Patients at high risk of bleeding should be carefully monitored for signs of bleeding or anemia following the administration of this medication. This medication should not be used in patients with allergies to its ingredients, those with clinically significant hemorrhage, or those with severe renal or liver disease. It should also be avoided in patients with recent gastrointestinal ulcers, intracranial hemorrhage, or surgical history, as well as when used in conjunction with other anticoagulants. Extra caution is required when this medication is used with drugs that increase the risk of bleeding, such as acetylsalicylic acid, antiplatelet agents, and nonsteroidal anti-inflammatory drugs. Patients with hepatic impairment or reduced renal function should undergo regular renal and liver function tests before and during treatment. Before any surgical or invasive procedures, this medication should be discontinued to reduce the risk of bleeding, and it should be resumed only after hemostasis is confirmed post-procedure. Pregnant or breastfeeding women should not take this medication, and women of childbearing potential must discuss their pregnancy plans with their doctor. Elderly patients or those with impaired renal function may require dosage adjustments and should follow their doctor's instructions. The effectiveness of this medication cannot be accurately assessed with routine blood clotting tests, thus special testing may be necessary in certain situations. In case of overdose, the risk of bleeding is significantly increased, so immediate medical attention should be sought, and there is currently no antidote for this medication. It is very important to consult with medical personnel immediately if any signs of bleeding or adverse reactions occur while taking this medication.
Not everyone experiences these, and they can vary from person to person.
This medication should be stored in a tightly closed container to protect it from air and moisture, and it should be kept at room temperature between 1 to 30 degrees Celsius.
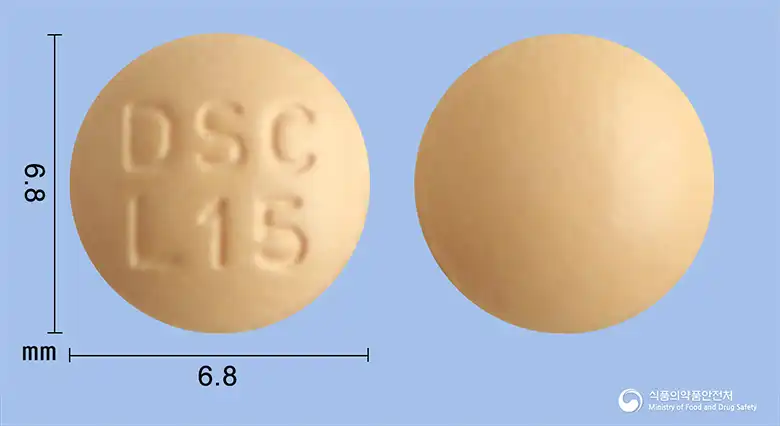
Pink round film-coated tablet
28 tablets/box, 30 tablets/box [10 tablets/PTP x 3]
Even with the same ingredient, strength, dosage form and how it is taken can differ.
Viewing nowEdoxaban Tosylate Hydrate 40.41mg
Tablet · Prescription medication
Shinil Pharmaceutical Co., Ltd.
Edoxaban Tosylate Hydrate 20.205mg
Tablet · Prescription medication
Dong-A Socio Holdings Co., Ltd.

Edoxaban Tosylate Hydrate 40.41mg
Tablet · Prescription medication
Hanmi Daiichi Sankyo Co., Ltd.

Edoxaban Tosylate Hydrate 80.82mg
Tablet · Prescription medication
Daichi Sankyo Korea Co., Ltd.
Edoxaban Tosylate Hydrate 20.205mg
Orally disintegrating Tablet · Prescription medication
Dong-A ST Co., Ltd.
Edoxaban Tosylate Hydrate 80.82mg
Orally disintegrating Tablet · Prescription medication
Dong-A ST Co., Ltd.
Edoxaban Tosylate Hydrate 40.41mg
Orally disintegrating Tablet · Prescription medication
Dong-A ST Co., Ltd.

Edoxaban Tosylate Hydrate 80.82mg
Tablet · Prescription medication
Shinil Pharmaceutical Co., Ltd.
Even with the same ingredient, the dose and directions can differ by strength and dosage form. Talk to a doctor or pharmacist before switching from a medication you are already taking.
No questions yet.
For anything that needs medical judgment, consult a doctor or pharmacist.
This drug information is based on data provided by the Korea Ministry of Food and Drug Safety.
Consult a doctor or pharmacist for accurate dosage, administration, and usage instructions.