
 한국어
 English
 日本語
 中文(简体)
 Viewing now
Certican Tablets 1.0 mg (Everolimus)
Everolimus 1mg
Tablet · Prescription medication
Jongkundang Co., Ltd.
MFDS item code 201804562 · Approved 2018.11.16 · Insurance code 643308220
Prevention of rejection after liver, kidney, and heart transplantation
This medication is used to prevent organ rejection that may occur after kidney, heart, and liver transplants. In particular, in kidney and heart transplant patients, it is taken in combination with microemulsion formulations of cyclosporine and corticosteroids to control immune response. For liver transplant patients, it is effectively combined with tacrolimus and corticosteroids to prevent transplant rejection. The main purpose of this medication is to protect the function of the transplanted organ, increase the success rate of transplants, and help maintain the health of the patient. Therefore, this medication is used for stable recovery and improved long-term survival rates after organ transplantation.
Adults: In kidney and heart transplant patients, this medicine should be administered orally at an initial dose of 0.75mg twice daily (total daily dose of 1.5mg) as soon as possible after transplantation. In liver transplant patients, an initial dose of 1.0mg twice daily (total daily dose of 2.0mg) should be administered orally approximately 4 weeks after transplantation. The total daily dose of this medicine should always be administered consistently either with food or on an empty stomach, in 2 divided doses per day, and in combination with cyclosporine in microemulsion formulation or tacrolimus. The dose may be adjusted according to the blood concentration, tolerability, individual patient response, changes in concomitant medications, and clinical status of patients receiving this medicine. Dose adjustments may be made at intervals of 4-5 days. In kidney transplant patients receiving everolimus 3.0mg/day, the efficacy benefit of the 3.0mg/day dose over the 1.5mg/day dose has not been established, and patients receiving everolimus 3.0mg/day had poorer tolerability than those receiving 1.5mg/day and MMF. In heart transplant patients, the 3.0mg/day dose provided an efficacy benefit over everolimus 1.5mg/day; however, patients receiving everolimus 3.0mg/day had poorer tolerability than those receiving 1.5mg/day and azathioprine (see Precautions for Use). Elderly patients (65 years and older): Although clinical experience in patients aged 65 years and older is limited, no clear differences in the pharmacokinetics of everolimus have been observed between patients aged 65-70 years and older and healthy adult patients. Patients with renal impairment: No dose adjustment is required. Patients with hepatic impairment: Whole-blood trough concentrations of everolimus should be monitored closely in patients with hepatic impairment. In patients with mild hepatic impairment (Child-Pugh Class A), the dose should be reduced to approximately 2/3 of the normal dose. For patients with moderate hepatic impairment (Child-Pugh B), the dose should be reduced to approximately 1/2 of the normal dose, and for patients with severe hepatic impairment (Child-Pugh C), it should be reduced to approximately 1/3 of the normal dose. The dose should then be adjusted based on therapeutic drug monitoring. <Dose reduction of this medicine in patients with hepatic impairment> Normal hepatic function / Mild hepatic impairment (Child-Pugh A) / Moderate hepatic impairment (Child-Pugh B) / Severe hepatic impairment (Child-Pugh C) Kidney and heart transplantation: 0.75 mg twice daily / 0.5 mg twice daily / 0.5 mg twice daily / 0.25 mg twice daily Liver transplantation: 1 mg twice daily / 0.75 mg twice daily / 0.5 mg twice daily / 0.5 mg twice daily Therapeutic drug monitoring: Patients with whole-blood trough concentrations of everolimus of at least 3.0ng/ml have been found to have a lower incidence of biopsy-proven acute rejection in kidney, heart, and liver transplantation than patients with trough concentrations below 3.0ng/ml. An upper limit of the therapeutic range of 8ng/ml is recommended; concentrations exceeding 12ng/ml have not been studied. Optimal dose adjustment for this medicine should be based on the whole-blood trough concentration measured 4-5 days after the previous dose change. Cyclosporine interacts with everolimus, and consequently, everolimus concentrations may decrease if cyclosporine exposure is substantially reduced (e.g., blood trough concentration<50ng/ml). Recommended cyclosporine dose in kidney transplantation: This medicine should not be used long term with a full dose of cyclosporine. Based on experience from study A2309, the reduction in cyclosporine exposure should begin immediately after transplantation according to the following recommended whole-blood trough concentration ranges. <Recommended target cyclosporine whole-blood trough concentration ranges in kidney transplantation> Target cyclosporine whole-blood trough concentration C0(ng/ml) Month 1: This medicine treatment group 100-200 Months 2-3: This medicine treatment group 75-150 Months 4-5: This medicine treatment group 50-100 Months 6-12: This medicine treatment group 25-50 Before reducing the cyclosporine dose, confirm that the whole-blood trough concentration of everolimus at steady state is at least 3ng/ml. Data on administration of this medicine with cyclosporine trough concentrations of 25-50ng/ml after 12 months are limited in kidney transplant patients. Recommended cyclosporine dose in heart transplantation: To improve renal function, the cyclosporine dose should be reduced in heart transplant patients during the maintenance phase. If renal impairment progresses further or the calculated creatinine clearance is below 60ml/min, the dose should be adjusted. In heart transplant patients, the cyclosporine dose may be based on the blood trough concentration of cyclosporine. In clinical trials, serum creatinine levels were significantly higher in the groups receiving this medicine than in the azathioprine group at 3, 6, 9, 18, and 24 months; the increase occurred from 1 month after treatment in the 3.0mg/day group and from 3 months after treatment in the 1.5mg/day group. Renal function should be monitored regularly and closely in all patients receiving this medicine in combination with a full dose of cyclosporine, and cyclosporine dose reduction should be considered in patients with elevated serum creatinine concentrations. Data are limited on administration of this medicine in heart transplant patients with cyclosporine blood trough concentrations below 175ng/ml during the first 3 months, below 135ng/ml at 6 months, and below 100ng/ml after 6 months. Before reducing the cyclosporine dose, confirm that the whole-blood trough concentration of everolimus at steady state is at least 3ng/ml. Recommended tacrolimus dose in liver transplantation: Starting approximately 3 weeks after initiating concomitant administration of this medicine and tacrolimus, adjust tacrolimus to achieve a blood trough concentration of 3-5ng/ml. There are no controlled clinical trials of this medicine in combination with a full dose of tacrolimus.
Children under 18 years: The safety and efficacy of this medicine have not been established in children under 18 years of age.
This medication helps suppress immune function to prevent the body from rejecting the transplanted organ. However, caution is needed as acute rejection may increase if not used in conjunction with calcinurins and other immunosuppressants. While this medication has experience with multiple immunosuppressants, sufficient research has not been conducted on some combinations. In particular, using it with a drug called thymoglobulin may significantly increase the risk of infection. Immune suppression increases the risk of various opportunistic infections such as bacterial, viral, and fungal, and can lead to serious infections or sepsis. During the use of this medication, necessary antibiotic treatment for infection prevention may be recommended. Additionally, this medication is metabolized in the liver by a specific enzyme (CYP3A4), so caution is advised when taken with drugs that strongly inhibit or activate this enzyme, as drug concentrations can vary greatly. Patients taking this medication may have an increased risk of developing malignancies such as lymphoma or skin cancer, so it is necessary to protect the skin from ultraviolet light and undergo regular check-ups. Side effects such as vascular edema may occur, especially when taken with blood pressure medications like ACE inhibitors. There is a risk of renal function worsening when using this medication with calcinurins, so regular kidney function tests are necessary, and the dosage of calcinuran imused should be adjusted as needed. There may be an increase in proteinuria, so it is important to continuously monitor protein excretion through urinalysis. There is a risk of thrombosis in the renal vessels within the first 30 days post-transplant, so caution is required. Delayed wound healing at the surgical site or the occurrence of complications such as wound infections and incisional hernias should be managed carefully. Serious side effects related to blood disorders or pulmonary diseases, interstitial lung disease have been rarely reported, so immediate consultation with healthcare professionals is warranted upon symptom occurrence. This medication should not be administered to patients with allergies to specific components or lactose intolerance. Patients must undergo regular blood sugar, lipid, blood tests, liver and kidney function tests, and should report any abnormal symptoms immediately. It is safer for women who are pregnant or breastfeeding to refrain from taking this medication and to use effective contraception during treatment. In case of overdose, supportive treatment according to symptoms is required, as there are no specific antidotes. This medication should be taken whole and not crushed or broken.
Acute rejection reaction, severe infection, septicemia, BK virus-associated kidney disease, JC virus-associated progressive multifocal leukoencephalopathy, Pneumocystis pneumonia, cytomegalovirus infection, angioedema, kidney function impairment, proteinuria, renal artery and vein thrombosis, wound infection, wound rupture, incisional hernia, seroma, fluid retention, lymphatic cyst, pericardial effusion, pleural effusion, thrombotic microangiopathy, interstitial lung disease, non-infectious pneumonia, anemia, erythrocytopenia, leukopenia, thrombocytopenia, pancytopenia, thrombotic microangiopathy, male hypogonadism, hyperlipidemia, new-onset diabetes, hypokalemia, insomnia, anxiety, headache, pericardial effusion, tachycardia, hypertension, venous thromboembolism, bleeding, lymphorrhea, tissue thrombosis, pleural effusion, cough, dyspnea, diarrhea, nausea, vomiting, abdominal pain, pharyngeal pain, pancreatitis, gastritis, oral ulcer, non-infectious hepatitis, jaundice, acne, rash, myalgia, arthralgia, proteinuria, renal tubular necrosis, erectile dysfunction, pain, fever, peripheral edema, healing failure, incisional hernia, liver enzyme abnormalities, leukoclastic vasculitis, pulmonary proteinosis, erythema multiforme, ovarian cyst, constipation, pruritus, dyspepsia, osteoporosis, acute pyelonephritis, osteopenia, dizziness, chest pain, stomatitis, urticaria, peripheral artery occlusive disease, limb pain, menorrhagia, tremors, rhinorrhea, increased serum parathyroid hormone, chest discomfort, hepatic steatosis, paresthesia, hypoesthesia, subarachnoid hemorrhage, acute pyelonephritis, ear infection, muscle calcification, muscle weakness, folliculitis, cystitis, pollakiuria, halitosis, renal necrosis, systemic lupus erythematosus, furuncle, anal abscess, increased serum creatinine, transplant rejection, pneumonia, urinary tract infection, acute pyelonephritis, gastroenteritis, influenza, bronchopneumonia, transplant loss, infectious colitis, subarachnoid hemorrhage, osteonecrosis, convulsions, airway infection, cerebral infarction, femoral neck fracture, palpitations, headache, fever, anemia, upper gastrointestinal bleeding, renal tubular disorder, renal necrosis, compression fracture, gastritis, pharyngitis, carbon monoxide poisoning, seroma, bleeding, prolonged bleeding time, Clostridium difficile colitis, Pneumocystis pneumonia, Staphylococcus wound infection, oliguria, lower gastrointestinal bleeding, anal abscess, laryngitis, aspiration pneumonia
Not everyone experiences these, and they can vary from person to person.
This medication should be stored in a tightly closed container to prevent air and moisture from entering. Additionally, it should be kept away from direct sunlight and in a cool place below 30 degrees Celsius to maintain its effectiveness.
White to yellow round tablets
60 tablets (10 tablets/ptp x 6)
Even with the same ingredient, strength, dosage form and how it is taken can differ.
Viewing nowEverolimus 1mg
Tablet · Prescription medication
Jongkundang Co., Ltd.
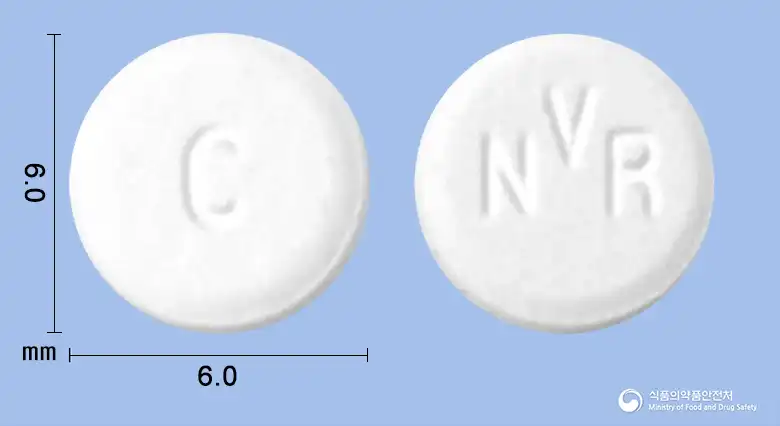
Everolimus 0.25mg
Tablet · Prescription medication
Korea Novartis Co., Ltd.
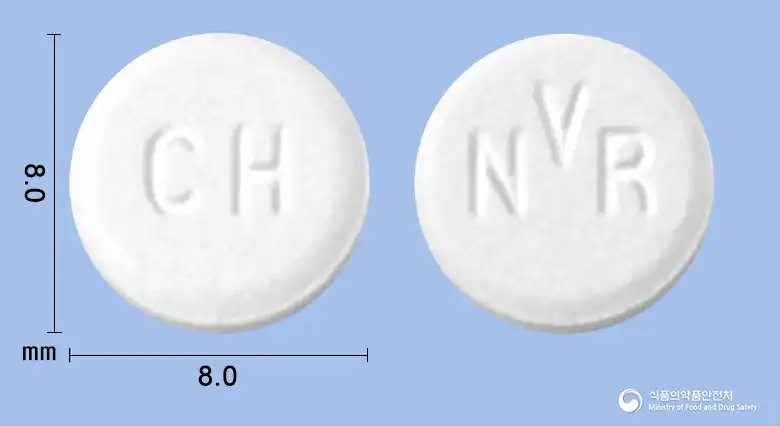
Everolimus 0.5mg
Tablet · Prescription medication
Korea Novartis Co., Ltd.

Everolimus 0.75mg
Tablet · Prescription medication
Novartis Korea Co., Ltd.

Everolimus 1mg
Tablet · Prescription medication
Novartis Korea Co., Ltd.
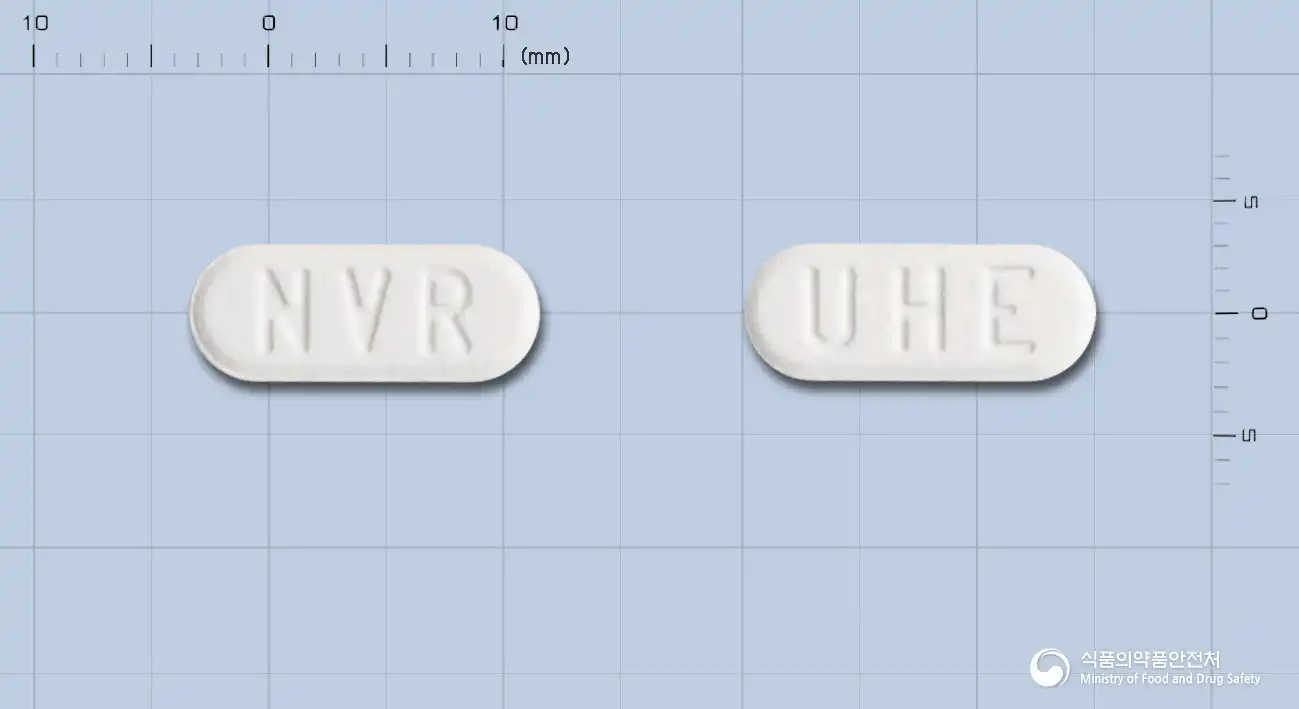
Everolimus 10mg
Tablet · Prescription medication
Novartis Korea Co., Ltd.
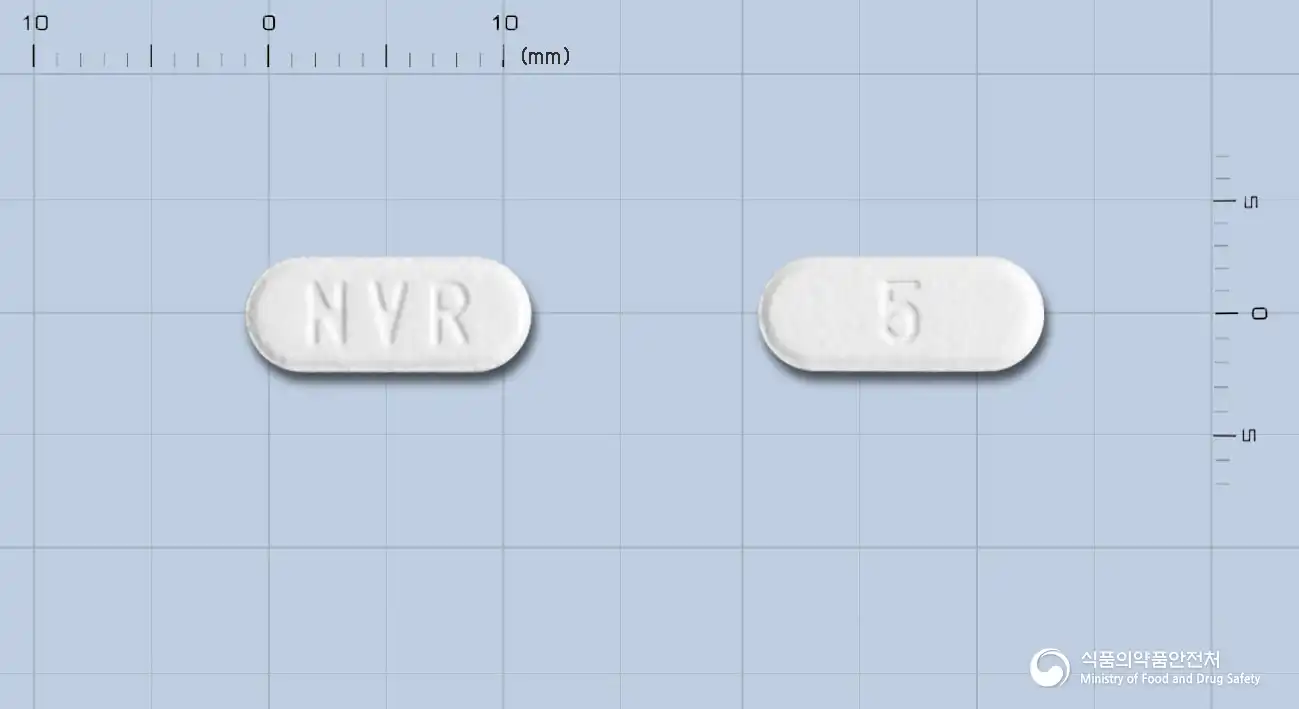
Everolimus 5mg
Tablet · Prescription medication
Novartis Korea Co., Ltd.
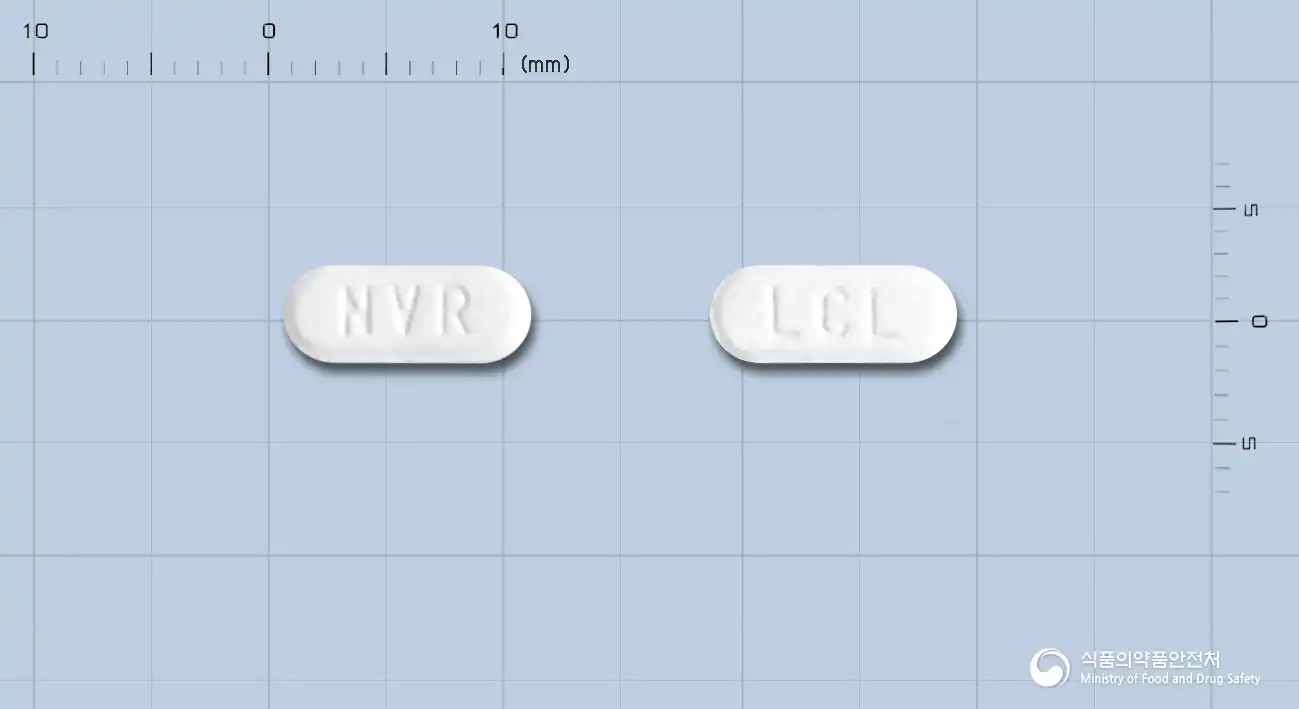
Everolimus 2.5mg
Tablet · Prescription medication
Novartis Korea Co., Ltd.
Even with the same ingredient, the dose and directions can differ by strength and dosage form. Talk to a doctor or pharmacist before switching from a medication you are already taking.
No questions yet.
For anything that needs medical judgment, consult a doctor or pharmacist.
This drug information is based on data provided by the Korea Ministry of Food and Drug Safety.
Consult a doctor or pharmacist for accurate dosage, administration, and usage instructions.