
 한국어
 English
 日本語
 中文(简体)
 Viewing now
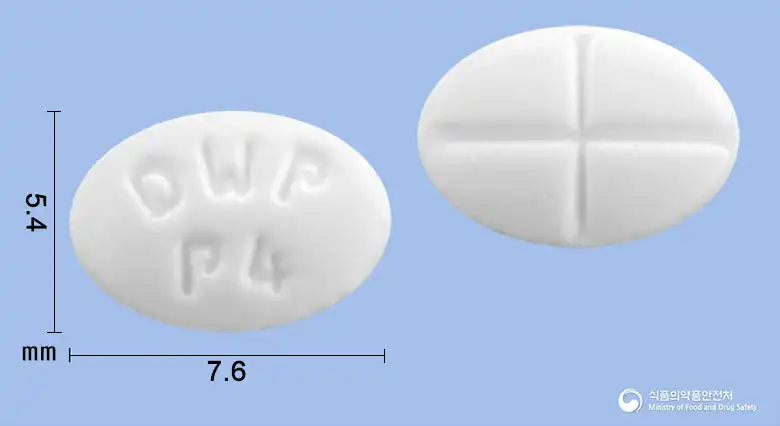
PDI-Wonjeong (Methylprednisolone)
Methylprednisolone 4mg
Tablet · Prescription medication
Dae Won Pharmaceutical Co., Ltd.
MFDS item code 201803542 · Approved 2018.08.30 · Insurance code 671806680
Treatment of inflammatory and allergic conditions, endocrine, hematologic, and edematous disorders, and neoplastic and infectious diseases
This medication is effectively used for various endocrine disorders, rheumatic diseases, and collagen diseases. It helps with endocrine-related issues such as adrenal cortical insufficiency, congenital adrenal hyperplasia, and hypercalcemia, and is also used during acute exacerbations of inflammatory diseases like rheumatoid arthritis and tendinitis. Additionally, it is utilized for the prevention and maintenance treatment of exacerbations of collagen diseases such as systemic lupus erythematosus and dermatomyositis as well as acute rheumatic myocarditis. In dermatological conditions, it is used for severe psoriasis, pemphigus, severe allergic diseases, ophthalmic inflammatory conditions, gastrointestinal inflammation, respiratory issues, palliative care for malignant tumors, and neurologic and edematous diseases. This drug plays a critical role in treating various inflammatory and immune-related disorders and alleviating symptoms.
1. The initial dose may vary from 4mg to 48mg per day as methylprednisolone, depending on the symptoms of the specific disease. A low dose is generally sufficient for less severe conditions, although a high initial dose may be required in certain patients. The initial dose should be maintained or adjusted until a satisfactory response is obtained. If a satisfactory clinical result is not achieved after a reasonable period, discontinue administration and switch to another appropriate treatment. The dose must be determined individually according to the various diseases being treated and the patient's response. After an adequate response is achieved, determine the appropriate maintenance dose by reducing the initial dose at suitable intervals until the lowest dose that maintains an adequate clinical response is reached. Continuous monitoring of the dose is required. Situations that may require dose adjustment include improvement or worsening of the disease, individual patient response to the drug, and the effect on the patient of exposure to stressful circumstances that are not directly related to the symptoms of the disease being treated. In the latter case, it may be necessary to increase the dose for a period sufficient to achieve a satisfactory effect on the patient's condition. After long-term treatment, gradual dose reduction is recommended when discontinuing the drug. 2. Multiple sclerosis For treatment of acute exacerbations of multiple sclerosis, administration of prednisolone 200mg daily for 1 week, followed by prednisolone 80mg every other day for 1 month, is effective (methylprednisolone 4mg is equivalent to prednisolone 5mg). 3. ADT (Alternate Day Therapy) Alternate day therapy is a regimen in which twice the daily dose is administered in the morning on one of every 2 days. The purpose of this regimen is to enhance the effects of corticosteroids in patients requiring long-term drug therapy and to minimize adverse effects such as suppression of the pituitary-adrenal axis, Cushingoid state, corticosteroid withdrawal symptoms, and growth suppression in children. The rationale for this treatment plan is based on the following 2 important premises: 1) The anti-inflammatory and therapeutic effects of corticosteroids last longer than their physical presence and metabolic effects, and 2) Taking corticosteroids in the morning every other day restores nearly normal hypothalamus-pituitary-adrenal (HPA) activity on days when corticosteroids are not administered. A brief overview of HPA physiology may help explain this rationale. Free cortisol acts primarily through the hypothalamus; therefore, a decrease in free cortisol stimulates the pituitary gland to increase production of adrenocorticotropic hormone (ACTH), whereas an increase in free cortisol suppresses ACTH secretion. Normally, the HPA system is characterized by a 24-hour activity rhythm. Serum ACTH levels rise from a low level at 10 p.m. to a peak at 6 a.m. The increased ACTH levels stimulate adrenal cortical activity, causing plasma cortisol to peak between 2-8 a.m. This increase in cortisol decreases ACTH production and, consequently, adrenal cortical synthesis. This progressively lowers plasma corticosteroid levels throughout the day, reaching a minimum around midnight. The 24-hour HPA rhythm is absent in Cushing's disease, a condition characterized by hyperfunction of the adrenal cortex, with symptoms including obesity with centripetal fat distribution, thin skin that bruises easily, weakness and muscle wasting, hypertension, latent diabetes, osteoporosis, and electrolyte imbalance. The same clinical symptoms of hyperadrenocorticism may typically occur during long-term corticosteroid therapy administered in divided doses throughout the day. If they occur, disruption of the diurnal rhythm due to maintenance of elevated corticosteroid levels during the night is likely to play an important role in the development of corticosteroid adverse effects. Avoiding continuously elevated plasma concentrations, even for a short period, may help prevent adverse effects. During typical pharmacologic-dose corticosteroid therapy, ACTH production is suppressed along with inhibition of cortisol production by the adrenal cortex. The time required for recovery of normal HPA activity varies according to the dose and duration of treatment. During this period, the patient is susceptible to any stressful circumstances. Although a single morning dose causes substantially less adrenal suppression than taking prednisolone (10mg) in 4 divided doses every 6 hours, there is evidence that, at pharmacologic doses, some suppression of adrenal activity continues into the following day. In addition, adrenal cortical suppression has been observed for 2 days or longer after a single dose of any corticosteroid. Methylprednisolone, hydrocortisone, prednisone, prednisolone, and other corticosteroids are considered short-acting (a single dose causes adrenal cortical suppression for 1¼ to 1½ days) and are therefore recommended for alternate day therapy. The following points should be kept in mind when using alternate day therapy. 1) The basic principles and indications for corticosteroid therapy should be applied. The benefits of ADT should not encourage indiscriminate use of corticosteroids. 2) ADT is a treatment technique that should be considered as the basic plan for patients requiring long-term corticosteroid drug therapy. 3) ADT may be used initially for less severe diseases for which corticosteroid therapy is indicated. For more severe conditions, a regimen of high doses divided throughout the day will usually be required for initial control of disease progression. The initial suppressive dose should be continued until a satisfactory clinical response is achieved, usually for 4 to 10 days for many allergic and collagen diseases. It is important to keep the initial suppressive-dose period as short as possible, particularly if continued use of alternate day therapy is intended. Once control is achieved, two options are possible. ① Switch to ADT and gradually reduce the amount of corticosteroid given every other day. ② Reduce the daily dose of corticosteroid to the minimum effective level as soon as possible, according to control of disease progression, and then switch to an alternate day schedule. Theoretically, approach ① is more desirable. 4) Because of the benefits of ADT, this form of treatment is desirable for patients who have been taking corticosteroids daily for a long time (for example, rheumatoid arthritis). Since the HPA axis may already be suppressed in these patients, it may be difficult to establish ADT, and it is not always successful. However, regular attempts to make the change are recommended. If there are difficulties, it is preferable to administer 3 or even 4 times the daily dose every other day rather than simply doubling the daily dose. Once the patient is controlled again, attempts should be made to reduce this dose to the minimum. 5) As mentioned above, some corticosteroids are not recommended for alternate day therapy because they suppress adrenal function for a long time (for example, dexamethasone, betamethasone). 6) Maximum adrenal cortical activity occurs from 2 a.m. to 8 a.m., and minimum activity from 4 p.m. to midnight. When administered during the period of maximum activity (in the morning), exogenous corticosteroids suppress adrenal cortical activity the least. 7) As with any treatment setting, it is important to provide individualized and appropriate treatment for each patient when using ADT. Complete control of symptoms is not possible in every patient. Explaining the benefits of ADT will help patients understand and tolerate unstable symptoms that may occur later in the day when corticosteroids are not administered. If necessary, other symptomatic treatments may be added or increased during this period. 8) If an acute exacerbation occurs during the course of the disease, it may be necessary to return to a fully suppressive dose of corticosteroids divided throughout the day to achieve control. Once control is achieved, the established alternate day regimen may be attempted again. 9) Although many adverse effects of corticosteroid therapy may be minimized with ADT, as with any treatment setting, the physician must carefully weigh the benefit-risk ratio of treatment for each patient being considered for corticosteroid therapy.
This drug should not be used in certain patients. For example, individuals who are allergic to this drug or its constituents should not be administered this medication. It should also not be used in patients with infections that are not effectively countered by antimicrobial agents or systemic fungal infections, as it poses a risk of exacerbating infections. Patients with herpes simplex, shingles, and chickenpox should also refrain from using this drug, and those who are receiving live or attenuated live vaccines should not be treated with this medication. This drug contains lactose, and it should not be given to those with lactose intolerance or related genetic problems. This medication should be used cautiously in some patients. Glaucoma patients should take care as intraocular pressure may rise, worsening symptoms. Patients with tuberculous diseases or herpes simplex keratitis may experience worsening of symptoms due to its immunosuppressive effect. Cataract patients may also see a deterioration in their condition with this drug. Patients with electrolyte imbalances or hypertension may worsen due to changes in electrolyte metabolism, and those with thrombosis may have enhanced blood coagulation leading to deterioration. Recent patients who have undergone bowel anastomosis may be at risk for delayed wound healing. Patients with a history of acute myocardial infarction, diverticulitis, peptic ulcer disease, mental illness, severe osteoporosis, etc., should also be treated with caution. This drug may suppress immune function in patients with infections, leading to exacerbation of infections, so careful monitoring is important, and diabetic patients should be attentive to potential blood sugar increases and control their levels. Patients with renal failure or congestive heart failure may experience exacerbation of symptoms due to sodium retention. Patients with hypothyroidism, fatty liver, fat embolism, severe myasthenia gravis, the elderly, epilepsy, ulcerative colitis, etc., require special caution when using this drug. While taking this medication, various side effects may occur, so symptoms should be carefully monitored. Possible side effects include fluid retention, edema, hypertension, muscle weakness, osteoporosis, gastrointestinal issues (nausea, vomiting, abdominal pain, appetite changes, etc.), skin changes (thinning of the skin, hair loss, acne, etc.), neuropsychiatric abnormalities (headaches, insomnia, depression, etc.), endocrine issues (growth suppression, Cushing's syndrome, diabetes exacerbation, etc.), and eye issues (glaucoma, cataracts, infections, etc.). Prolonged use may lead to adrenal insufficiency, so it should not be abruptly discontinued but rather gradually tapered. In stress situations such as surgery or infection, dosages may need to be temporarily increased. The immunosuppressive effects make patients particularly cautious against infections like chickenpox or measles, and vaccinations are also limited. This medication has many drug interactions, so caution is necessary when used concomitantly with others. Side effects may be enhanced or effects may change when used with certain antiarrhythmics, antibiotics, anticoagulants, diuretics, antihypertensives, etc. Therefore, always consult with a physician or pharmacist. During pregnancy, it should only be used cautiously when necessary, as it can affect the fetus, and during breastfeeding, it is best to avoid its administration. In children, there may be growth retardation, so it should be administered at the lowest possible dose with careful observation. The elderly are at increased risk for side effects related to infections, diabetes, osteoporosis, ocular diseases, etc., and should be used cautiously. This drug may cause hypokalemia, so potassium levels should be tested regularly, and care should be taken during skin tests or vaccinations. Additionally, in rare cases, serious allergic reactions or tumor-related complications have been reported, so any abnormal symptoms should be promptly discussed with healthcare professionals.
Edema, sodium retention, potassium loss, fluid retention, hypokalemic alkalosis, congestive heart failure, hypertension, myasthenia, aseptic necrosis of femoral and humeral epiphyses, steroid myopathy, loss of muscular tissue, pathological fractures of the pelvis, osteoporosis, vertebral compression fractures, arthralgia, tendon rupture, increased ALT, increased AST, increased ALP, nausea, thirst, vomiting, stomach pain, loss of appetite, increased appetite, peptic ulcer, abdominal distention, pancreatitis, esophagitis, diarrhea, delayed wound healing, facial erythema, thin and delicate skin, abnormal sweating, petechiae, purpura, skin reaction suppression, purpura, acne, hirsutism, hair loss, pigmentation, nipple edema, increased intracranial pressure, seizures, dizziness, headache, insomnia, euphoria, depression, Cushing's syndrome, menstrual irregularities, growth suppression, latent diabetes symptoms, secondary adrenal insufficiency, pituitary unresponsiveness, impaired glucose tolerance, increased demand for insulin or oral hypoglycemics, suppression of adrenocorticotropic hormone secretion, increased intraocular pressure, glaucoma, posterior capsule cataract, secondary eye infections, retinal disorders, exophthalmos, negative nitrogen balance due to protein catabolism, immune system disorders, allergic reactions, shock, urticaria, anaphylactic reactions, hypersensitivity reactions
Not everyone experiences these, and they can vary from person to person.
This drug should be stored in a tightly sealed container to protect it from air and moisture. It is important to maintain storage temperatures between 1 to 30 degrees Celsius. Proper storage helps retain the drug's effectiveness and safety for an extended period.
White oval-shaped tablets
30 tablets/bottle, 500 tablets/bottle
Even with the same ingredient, strength, dosage form and how it is taken can differ.
Viewing nowMethylprednisolone 4mg
Tablet · Prescription medication
Dae Won Pharmaceutical Co., Ltd.
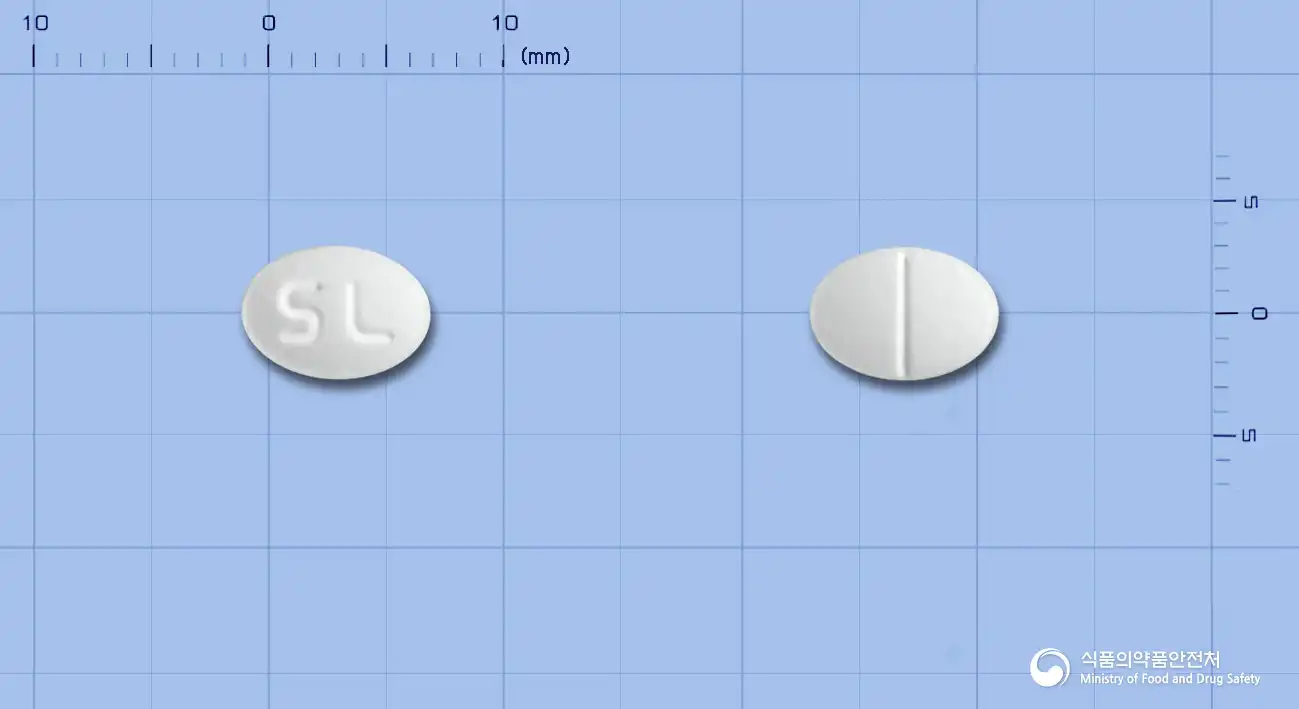
Methylprednisolone 4mg
Tablet · Prescription medication
Aprogen Biosciences, Inc.
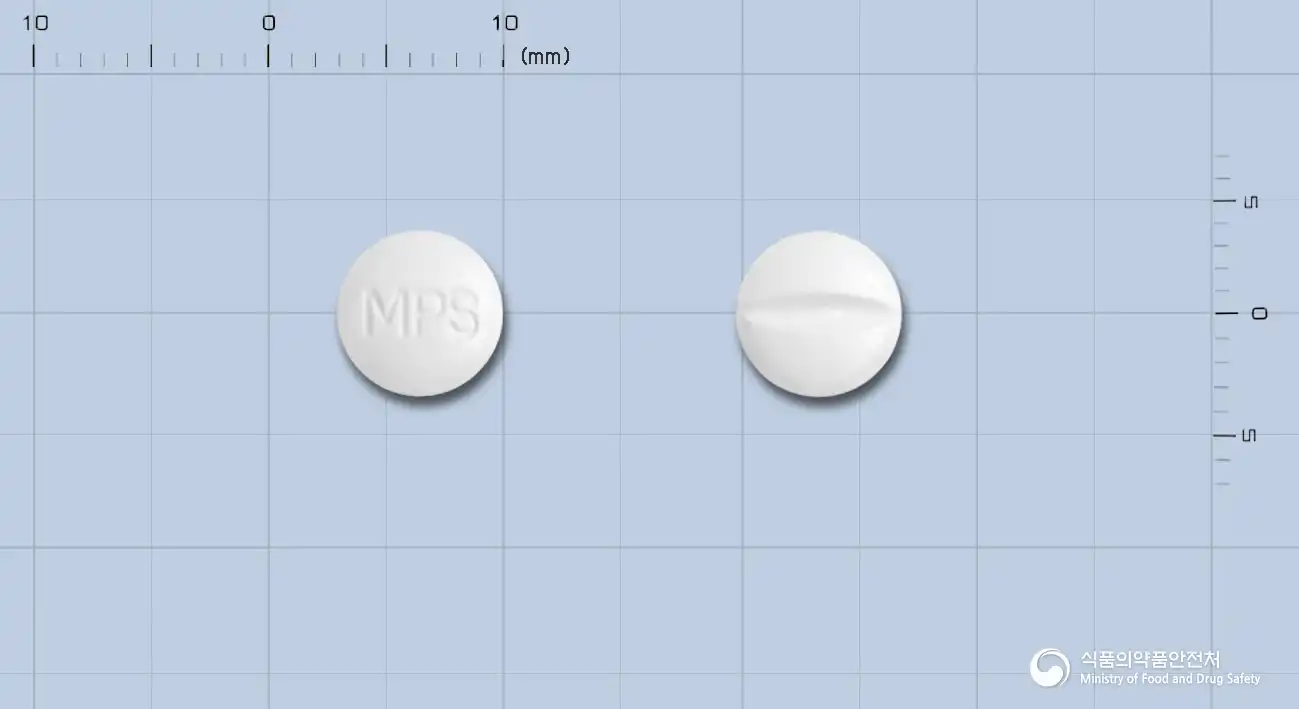
Methylprednisolone 4mg
Tablet · Prescription medication
BC World Pharmaceutical Co., Ltd.
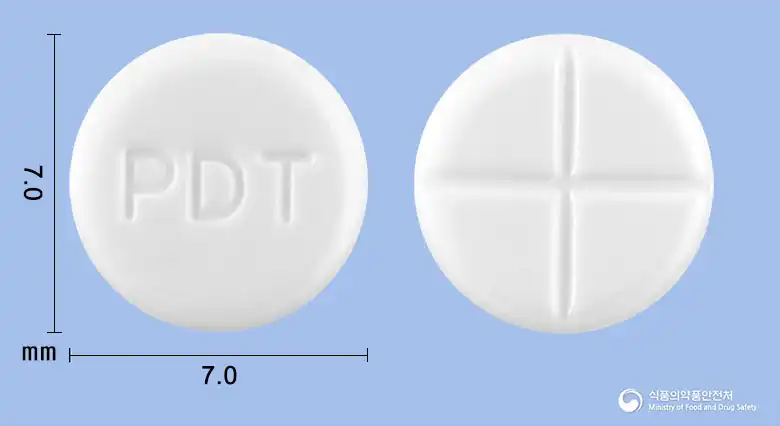
Methylprednisolone 4mg
Tablet · Prescription medication
JW Shin Pharmaceutical Co., Ltd.
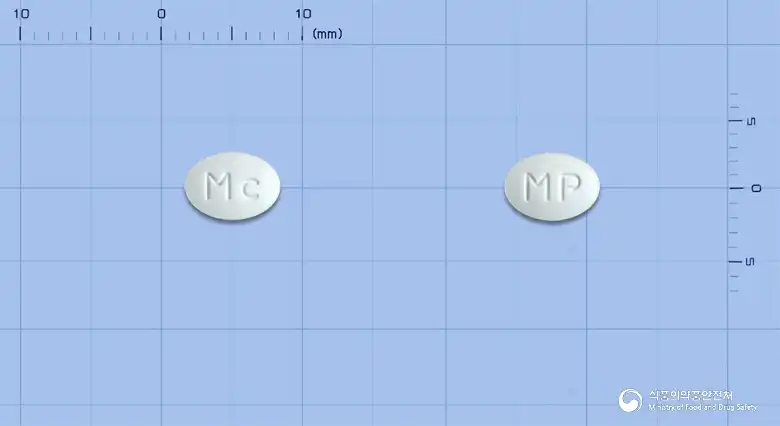
Methylprednisolone 4mg
Tablet · Prescription medication
MacNulty Pharmaceutical Co., Ltd.

Methylprednisolone 4mg
Tablet · Prescription medication
Dongkwang Pharmaceutical Co., Ltd.
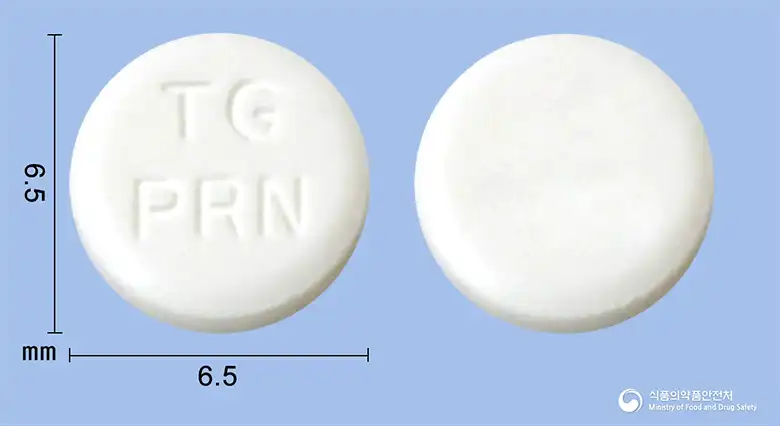
Methylprednisolone 4mg
Tablet · Prescription medication
Taegeuk Pharmaceutical Co., Ltd.
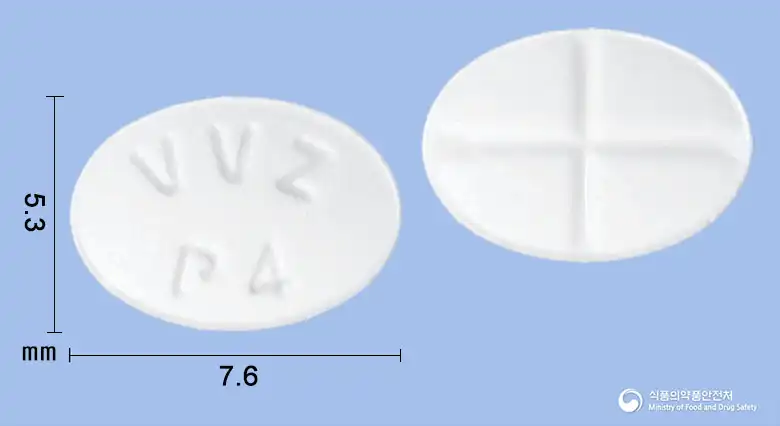
Methylprednisolone 4mg
Tablet · Prescription medication
Vivozon Pharmaceutical Co., Ltd.
Even with the same ingredient, the dose and directions can differ by strength and dosage form. Talk to a doctor or pharmacist before switching from a medication you are already taking.
No questions yet.
For anything that needs medical judgment, consult a doctor or pharmacist.
This drug information is based on data provided by the Korea Ministry of Food and Drug Safety.
Consult a doctor or pharmacist for accurate dosage, administration, and usage instructions.