
 한국어
 English
 日本語
 中文(简体)
 Viewing now
Lenaldocapsule 10mg (Lenalidomide)
Lenalidomide 10mg
Hard capsule · Prescription medication
Kwangdong Pharmaceutical Co., Ltd.
MFDS item code 201706898 · Approved 2017.08.31 · Insurance code 641806390
Treatment of multiple myeloma, anemia associated with myelodysplastic syndrome, and lymphoma (mantle cell and follicular)
This medication is primarily used in the treatment of various forms of blood cancers. In multiple myeloma patients, it is administered in combination with dexamethasone based on previous treatment experiences or along with melphalan and prednisone, and is effective for newly diagnosed patients and those who have undergone autologous hematopoietic stem cell transplantation. It is also effective in treating transfusion-dependent anemia in low-risk or intermediate-risk myelodysplastic syndromes associated with 5q chromosomal abnormalities. It is utilized in treatment alongside rituximab for patients with mantle cell lymphoma and follicular lymphoma. Overall, this drug is utilized in various ways for the treatment of complex hematologic malignancies.
1. Multiple myeloma 1) Combination therapy with dexamethasone for the treatment of patients who have received at least one prior therapy Treatment should not be initiated if the absolute neutrophil count is <1,000/㎕ and/or the platelet count is <75,000/㎕. The recommended initial dose is 25mg once daily. Take 25mg capsules on days 1~21 of each 28-day cycle. The recommended dose of dexamethasone is 40mg once daily on days 1~4, 9~12, and 17~20 during the first 4 cycles, based on a 28-day cycle. After 4 cycles, administer 40mg once daily only on days 1~4 of each 28-day cycle. Dose adjustments during treatment ① Dose adjustment according to platelet count Table 1. Platelet count Recommended dose If decreased to <30,000/㎕ Interrupt treatment and monitor complete blood counts weekly When recovered to ≧30,000/㎕ Resume at 15mg once daily For each subsequent decrease to <30,000/㎕ Interrupt treatment When recovered to ≧30,000/㎕ Resume at a dose reduced by 5mg from the dose being administered. Do not reduce the dose below 5mg once daily. ② Dose adjustment according to absolute neutrophil count (ANC) Table 2. Absolute neutrophil count Recommended dose If decreased to <1,000/㎕ Interrupt treatment, add G-CSF, and monitor complete blood counts weekly When recovered to ≧1,000/㎕ and neutropenia is the only toxicity Resume at 25mg once daily When recovered to ≧1,000/㎕ and other toxicities have occurred Resume at 15mg once daily For each subsequent decrease to <1,000/㎕ Interrupt treatment When recovered to ≧1,000/㎕ Resume at a dose reduced by 5mg from the dose being administered. Do not reduce the dose below 5mg once daily. For neutropenia, the use of growth factors should be considered for patient management. 2) Combination therapy with dexamethasone for the treatment of newly diagnosed patients who are ineligible for transplantation Treatment should not be initiated if the absolute neutrophil count is <1,000/㎕ and/or the platelet count is <50,000/㎕. The recommended initial dose is 25mg once daily. Take 25 mg capsules on days 1~21 of each 28-day cycle. The recommended dose of dexamethasone is 40mg once daily on days 1, 8, 15, and 22 of each 28-day cycle. For patients aged 75 years or older, the recommended dose of dexamethasone is 20mg once daily on days 1, 8, 15, and 22 of each 28-day cycle. Continue treatment until disease progression or unacceptable toxicity occurs. Dose adjustments during treatment <Dose reduction levels> This drug Dexamethasone Initial dose 25 mg 40 mg 1st dose reduction 20 mg 20 mg 2nd dose reduction 15 mg 12 mg 3rd dose reduction 10 mg 8 mg 4th dose reduction 5 mg 4 mg 5th dose reduction 2.5 mg N/A ① Dose adjustment according to platelet count Table 3. Platelet count Recommended dose If decreased to <25,000/㎕ Interrupt this drug and dexamethasone and monitor complete blood counts weekly When recovered to ≧50,000/㎕ Resume at one dose level below the dose being administered ② Dose adjustment according to absolute neutrophil count (ANC) Table 4. Absolute neutrophil count Recommended dose If decreased to <500/㎕ Interrupt this drug and dexamethasone and monitor complete blood counts weekly When recovered to ≧1,000/㎕ and neutropenia is the only toxicity Resume at the starting dose When recovered to ≧500/㎕ and dose-dependent hematologic toxicity other than neutropenia has occurred Resume at one dose level below the dose being administered For each subsequent decrease to <500/㎕ Interrupt this drug and dexamethasone When recovered to ≧500/㎕ Resume at one dose level below the dose being administered For neutropenia, the use of growth factors should be considered for patient management. ③ Dose adjustment for febrile neutropenia (fever ≥38.5℃ and ANC<1,000/㎕): Interrupt treatment and monitor complete blood counts weekly. If the patient is not receiving a growth factor, use of a growth factor should be considered. At the start of the next treatment cycle, if neutropenia is the only dose-limiting toxicity, resume treatment at the dose being administered, continuing growth factor use if necessary. Otherwise, resume treatment at one dose level below the dose being administered. If the patient is not receiving a growth factor, administer a growth factor. If this drug was reduced due to hematologic dose-limiting toxicity (dose limiting toxicity, DLT), and bone marrow function improves with continued treatment (no DLT for at least 2 consecutive cycles and, at the start of a new cycle at the current dose level, absolute neutrophil count ≥1,500/㎕ and platelet count ≥100,000/㎕), treatment may be resumed at a higher dose of this drug, at the physician’s discretion (up to the maximum starting dose). 3) Combination therapy with melphalan and prednisolone for the treatment of newly diagnosed patients who are ineligible for transplantation Treatment should not be initiated if the absolute neutrophil count is <1,500/㎕ and/or the platelet count is <75,000/㎕. The recommended initial dose is 10mg once daily. Take 10 mg capsules on days 1~21 of each 28-day cycle. Through cycle 9, administer melphalan orally at a dose of 0.18mg/kg on days 1~4 of each 28-day cycle, and prednisolone orally at a dose of 2mg/kg on days 1~4 of each 28-day cycle. For patients who have completed 9 cycles or who are unable to complete combination therapy due to tolerability, take this drug alone at 10mg once daily on days 1~21 of each 28-day cycle until disease progression. Dose adjustments during treatment <Dose reduction levels> This drug Melphalan Prednisolone Initial dose 10 mg 0.18 mg/kg 2 mg/kg 1st dose reduction 7.5 mg 0.14 mg/kg 1 mg/kg 2nd dose reduction 5 mg 0.10 mg/kg 0.5 mg/kg 3rd dose reduction 2.5 mg N/A 0.25 mg/kg ① Dose adjustment according to platelet count Table 5. Platelet count Recommended dose If decreased to <25,000/㎕ Interrupt this drug, melphalan, and prednisolone and monitor complete blood counts weekly When recovered to ≧25,000/㎕ Resume this drug and melphalan at doses reduced by one dose level For each subsequent decrease to <30,000/㎕ Interrupt this drug, melphalan, and prednisolone When recovered to ≧30,000/㎕ Resume this drug and melphalan at doses reduced by one dose level from the doses being administered ② Dose adjustment according to absolute neutrophil count (ANC) Table 6. Absolute neutrophil count Recommended dose If decreased to <500/㎕ Interrupt this drug, melphalan, and prednisolone and monitor complete blood counts weekly When recovered to ≧500/㎕ and neutropenia is the only toxicity Resume at the starting dose When recovered to ≧500/㎕ and dose-dependent hematologic toxicity other than neutropenia has occurred Resume this drug and melphalan at doses reduced by one dose level For each subsequent decrease to <500/㎕ Interrupt this drug, melphalan, and prednisolone When recovered to ≧500/㎕ Resume this drug and melphalan at doses reduced by one dose level from the doses being administered For neutropenia, the use of growth factors should be considered for patient management. ③ Dose adjustment for febrile neutropenia (fever≥38.5℃ and ANC<1,000/㎕): Interrupt this drug, melphalan, and prednisolone and monitor complete blood counts weekly. If the patient is not receiving a growth factor, use of a growth factor should be considered. At the start of the next treatment cycle, if neutropenia is the only dose-limiting toxicity, resume treatment at the dose being administered, continuing growth factor use if necessary. Otherwise, resume treatment at one dose level below the dose being administered. If the patient is not receiving a growth factor, administer a growth factor. 4) Combination therapy with bortezomib and dexamethasone for the treatment of newly diagnosed patients (1) Combination therapy with bortezomib and dexamethasone for the treatment of newly diagnosed patients who are ineligible for transplantation Treatment should not be initiated if the absolute neutrophil count is <1,000/㎕ and/or the platelet count is <80,000/㎕. The recommended initial dose of this drug is 25mg once daily, taken on days 1~14 of each 21-day cycle. Administer bortezomib by subcutaneous injection at a dose of 1.3mg/m2 per body surface area on days 1, 4, 8, and 11 of each 21-day cycle. The recommended dose of dexamethasone is 20mg once daily, taken on days 1, 2, 4, 5, 8, 9, 11, and 12 of each 21-day cycle. Patients should receive 8 cycles (24 weeks total) of treatment as initial therapy. After initial therapy, take this drug 25mg once daily in combination with dexamethasone on days 1-21 of each 28-day cycle. The recommended dosage regimen for dexamethasone is 40mg once daily on days 1, 8, 15, and 22 of each 28-day cycle. For patients aged 75 years or older, the starting dose of dexamethasone is 20mg once daily on days 1, 8, 15, and 22 of each 28-day cycle. Treatment may continue until disease progression or unacceptable toxicity occurs. (2) Induction combination therapy with dexamethasone and bortezomib for the treatment of newly diagnosed patients who are eligible for transplantation Treatment should not be initiated if the absolute neutrophil count is <1,000/㎕ and/or the platelet count is <80,000/㎕. The recommended initial dose of this drug is 25mg once daily, taken on days 1~21 of each 28-day cycle. Administer bortezomib by subcutaneous injection at a dose of 1.3mg/m2 per body surface area on days 1, 4, 8, and 11 of each 28-day cycle. The recommended dose of dexamethasone is 40mg once daily, taken on days 1-4 and 9-12 of each 28-day cycle. Patients should receive 6 cycles (24 weeks total) of treatment as induction therapy. Dose adjustments during treatment <Dose reduction levels> This drug Initial dose 25 mg 1st dose reduction 20 mg 2nd dose reduction 15 mg 3rd dose reduction 10 mg 4th dose reduction 5 mg 5th dose reduction 2.5 mg ① Dose adjustment according to platelet count Platelet count Recommended dose If decreased to <30,000/㎕ Interrupt treatment and monitor complete blood counts weekly When recovered to ≧50,000/㎕ Resume at one dose level below the dose being administered For each subsequent decrease to <30,000/㎕ Interrupt treatment When recovered to ≧50,000/㎕ Resume at one dose level below the dose being administered ② Dose adjustment according to absolute neutrophil count (ANC) Neutrophil count Recommended dose If decreased to <500/㎕ Interrupt treatment and monitor complete blood counts weekly When recovered to ≧1,000/㎕ and neutropenia is the only toxicity Resume at the starting dose When recovered to ≧500/㎕ and dose-dependent hematologic toxicity other than neutropenia has occurred Resume at one dose level below the dose being administered For each subsequent decrease to <500/㎕ Interrupt treatment When recovered to ≧500/㎕ Resume at one dose level below the dose being administered For neutropenia, the use of growth factors should be considered for patient management. *For dose adjustments of concomitant drugs, refer to the prescribing information for the relevant product. 5) Maintenance therapy in patients with newly diagnosed disease who have undergone autologous hematopoietic stem cell transplantation Maintenance therapy with this drug should be initiated in patients with no evidence of disease progression after adequate hematologic recovery following autologous hematopoietic stem cell transplantation. Treatment should not be initiated if the absolute neutrophil count is <1,000/㎕ and/or the platelet count is <75,000/㎕. The recommended initial dose is 10mg once daily. Take 10 mg capsules on days 1~28 of each 28-day cycle until intolerance or disease progression occurs. After 3 cycles of maintenance therapy with this drug, the dose may be increased to 15mg once daily if tolerated. Dose adjustments during treatment <Dose reduction levels> Starting dose (10mg) If the dose has been increased (15mg)* 1st dose reduction 5 mg 10 mg 2nd dose reduction 5mg (days 1~21 of each 28-day cycle) 5 mg 3rd dose reduction N/A 5mg (days 1~21 of each 28-day cycle) Do not reduce the dose below 5mg (days 1~21 of each 28-day cycle). *After 3 cycles of maintenance therapy with this drug, the dose may be increased to 15mg once daily if tolerated. ① Dose adjustment according to platelet count Table 7. Platelet count Recommended dose If decreased to <30,000/㎕ Interrupt treatment and monitor complete blood counts weekly When recovered to ≧30,000/㎕ Resume at one dose level below the dose being administered For each subsequent decrease to <30,000/㎕ Interrupt treatment When recovered to ≧30,000/㎕ Resume at one dose level below the dose being administered ② Dose adjustment according to absolute neutrophil count (ANC) Table 8. Absolute neutrophil count Recommended dose If decreased to <500/㎕ Interrupt treatment and monitor complete blood counts weekly When recovered to ≧500/㎕ Resume at one dose level below the dose being administered For each subsequent decrease to <500/㎕ Interrupt treatment When recovered to ≧500/㎕ Resume at one dose level below the dose being administered For neutropenia, the use of growth factors should be considered for patient management. 2. Myelodysplastic syndromes Treatment should not be initiated if the absolute neutrophil count is <500/㎕ and/or the platelet count is <25,000/㎕. The recommended initial dose is 10mg once daily. Take 10 mg capsules on days 1~21 of each 28-day cycle. Dose adjustments during treatment <Dose reduction levels> This drug Initial dose 10 mg once daily on days 1~21 of each 28-day cycle 1st dose reduction 5 mg once daily on days 1~28 of each 28-day cycle 2nd dose reduction 2.5 mg once daily on days 1~28 of each 28-day cycle 3rd dose reduction 2.5 mg every other day on days 1~28 of each 28-day cycle ① Dose adjustment according to platelet count Table 9. Platelet count Recommended dose If decreased to <25,000/㎕ Interrupt treatment and monitor complete blood counts weekly When recovered to ≧50,000/㎕ or recovered to ≧25,000/㎕~<50,000/㎕ at least 2 times over 7 days or longer Resume at one dose level below the dose being administered ② Dose adjustment according to absolute neutrophil count (ANC) Table 10. Absolute neutrophil count Recommended dose If decreased to <500/㎕ Interrupt treatment and monitor complete blood counts weekly When recovered to ≧500/㎕ Resume at one dose level below the dose being administered For neutropenia, the use of growth factors should be considered for patient management. Treatment with this drug should be discontinued in patients who have not achieved at least a minor erythroid response (demonstrated by a reduction in transfusion requirements of at least 50%, or, if no transfusions were given, an increase in hemoglobin of 1g/dl) within 4 months after starting treatment. 3. Mantle cell lymphoma The recommended initial dose is 25mg once daily. Take 25mg capsules on days 1~21 of each 28-day cycle. Dose adjustments during treatment <Dose reduction levels> This drug Initial dose 25mg once daily on days 1~21 of each 28-day cycle 1st dose reduction 20mg once daily on days 1~21 of each 28-day cycle 2nd dose reduction 15mg once daily on days 1~21 of each 28-day cycle 3rd dose reduction 10mg once daily on days 1~21 of each 28-day cycle 4th dose reduction 5mg once daily on days 1~21 of each 28-day cycle 5th dose reduction 2.5mg once daily on days 1~21 of each 28-day cycle 5mg every other day on days 1~21 of each 28-day cycle ① Dose adjustment according to platelet count Table 11. Platelet count Recommended dose If decreased to <50,000/㎕ Interrupt treatment and monitor complete blood counts weekly When recovered to ≧60,000/㎕ Resume at one dose level below the dose being administered For each subsequent decrease to <50,000/㎕ Interrupt treatment and monitor complete blood counts weekly When recovered to ≧60,000/㎕ Resume at one dose level below the dose being administered Do not reduce the dose below 2.5mg once daily or 5mg every other day. ② Dose adjustment according to absolute neutrophil count (ANC) Table 12. Absolute neutrophil count Recommended dose If decreased to <1,000/㎕ for at least 7 days or if decreased to <1,000/㎕ with fever (body temperature ≧38.5℃) or if decreased to <500/㎕ Interrupt treatment and monitor complete blood counts weekly When recovered to ≧1,000/㎕ Resume at one dose level below the dose being administered For each subsequent decrease to <1,000/㎕ for at least 7 days or if decreased to <1,000/㎕ with fever (body temperature ≧38.5℃) or if decreased to <500/㎕ Interrupt treatment. When recovered to ≧1,000/㎕ Resume at one dose level below the dose being administered Do not reduce the dose below 2.5mg once daily or 5mg every other day. For neutropenia, the use of growth factors should be considered for patient management. 4. Follicular lymphoma Treatment should not be initiated if the absolute neutrophil count is <1,000/㎕ and/or the platelet count is <50,000/㎕ (except in cases secondary to lymphoma infiltration of the bone marrow). The recommended initial dose is 20mg once daily. Take 20mg capsules on days 1~21 of each 28-day cycle. Take for a maximum of 12 treatment cycles. The recommended initial dose of rituximab is based on a 28-day cycle; during cycle 1, administer 375 mg/m2 intravenously once weekly (days 1, 8, 15, and 22). During cycles 2~5, administer 375 mg/m2 intravenously only on day 1 of each 28-day cycle. Dose adjustments during treatment <Dose reduction levels> This drug Initial dose 20mg once daily on days 1~21 of each 28-day cycle 1st dose reduction 15mg once daily on days 1~21 of each 28-day cycle 2nd dose reduction 10mg once daily on days 1~21 of each 28-day cycle 3rd dose reduction 5mg once daily on days 1~21 of each 28-day cycle For dose adjustments due to rituximab toxicity, refer to the relevant prescribing information. ① Dose adjustment according to platelet count Table 13. Platelet count Recommended dose If decreased to <50,000/㎕ Interrupt this drug and monitor complete blood counts weekly When recovered to ≥50,000/㎕ Resume at one dose level below the dose being administered For each subsequent decrease to <50,000/㎕ Interrupt this drug and monitor complete blood counts weekly When recovered to ≥50,000/㎕ Resume at one dose level below the dose being administered Do not reduce the dose below 5mg once daily. ② Dose adjustment according to absolute neutrophil count (ANC) Table 14. Absolute neutrophil count Recommended dose If decreased to <1,000/㎕ for at least 7 days or if decreased to <1,000/㎕ with fever (body temperature ≥38.5°C) or if decreased to <500/㎕ Interrupt this drug and monitor complete blood counts weekly When recovered to ≥1,000/㎕ Resume at one dose level below the dose being administered For each subsequent decrease to <1,000/㎕ for at least 7 days or if decreased to <1,000/㎕ with fever (body temperature ≥38.5°C) or if decreased to <500/㎕ Interrupt this drug and monitor complete blood counts weekly When recovered to ≥1,000/㎕ Resume at one dose level below the dose being administered Do not reduce the dose below 5mg once daily. Mantle cell lymphoma or follicular lymphoma Tumor lysis syndrome (TLS) All patients should receive prophylaxis for tumor lysis syndrome (allopurinol, rasburicase, or an equivalent regimen according to institutional treatment guidelines) and should be adequately hydrated orally during the first week of the first treatment cycle or for a longer period if clinically necessary. To monitor for tumor lysis syndrome, patients should have a chemistry panel during the first cycle and weekly if clinically necessary. For patients with laboratory TLS or grade 1 clinical TLS, this drug may be continued at the same dose or, at the physician’s discretion, continued at a dose reduced by one dose level. Provide adequate intravenous hydration and appropriate medical management according to standard practice until electrolyte abnormalities are corrected. Rasburicase treatment may be needed to reduce hyperuricemia. Hospitalization is at the physician’s discretion. For patients with grade 2-4 clinical TLS, interrupt this drug and perform a chemistry panel weekly or as clinically necessary. Provide adequate intravenous hydration and appropriate medical management according to standard practice until electrolyte abnormalities are corrected. Rasburicase treatment and hospitalization are at the physician’s discretion. Once TLS improves to grade 0, resume treatment at a dose reduced by one dose level, at the physician’s discretion. Tumor flare reaction (TFR) For patients who develop grade 1/2 tumor flare reaction, this drug may be continued without interruption or dose reduction, at the prescriber’s discretion. Non-steroidal anti-inflammatory drugs (NSAIDs), a limited course of corticosteroids, and/or opioid analgesics may be administered at the prescriber’s discretion. For patients who develop grade 3/4 tumor flare reaction, interrupt this drug and initiate treatment with NSAIDs, corticosteroids, and/or opioid analgesics. When the reaction resolves to grade 1 or lower, resume treatment at the same dose for the remainder of the cycle. Patients may be managed symptomatically according to the guidance for treatment of grade 1/2 tumor flare reaction. 5. Dose adjustment for other grade 3/4 toxicities If other grade 3/4 toxicities associated with this drug occur, interrupt treatment. Once the toxicity improves to grade 2 or lower, resume treatment at a dose reduced by one dose level below the dose being administered, at the prescriber’s discretion. 6. This drug should not be administered to patients with a history of grade 4 rash due to thalidomide. For grade 2-3 skin rash, interruption or discontinuation of this drug should be considered. If angioedema, an anaphylactic reaction, grade 4 rash, exfoliative or bullous rash occurs, or Stevens-Johnson syndrome, toxic epidermal necrolysis, or drug reaction with eosinophilia and systemic symptoms (DRESS syndrome) is suspected, treatment should be discontinued and should not be resumed even after these reactions resolve. 7. Dose in patients with renal impairment Because this drug is excreted through the kidneys, toxicity may be greater in patients with renal impairment. Since renal impairment is more common in elderly patients, care should be taken when selecting the dose, and renal function should be monitored carefully. The initial doses for patients with renal impairment are as follows. Patients with a creatinine clearance below 11 mL/min who are not on dialysis and patients with a creatinine clearance below 7 mL/min have not been studied. Table 15. Initial dose in patients with renal impairment_multiple myeloma or mantle cell lymphoma Category Renal function (Cockcroft-Gault CLcr) Dose adjustment in multiple myeloma/mantle cell lymphoma Dose adjustment in post-transplant maintenance therapy Moderate renal impairment 30 ≤ CLcr <50mL/min 10mg once daily* 5mg once daily Severe renal impairment CLcr <30mL/min (non-dialysis patients) 7.5mg once daily or 15mg every other day 2.5mg once daily End-stage renal disease CLcr <30mL/min (dialysis patients) 5mg once daily Administer after dialysis on dialysis days 2.5mg once daily Administer after dialysis on dialysis days *After the second treatment cycle, the dose may be increased to 15mg once daily if the patient does not respond to treatment and tolerates the treatment. Table 16. Initial dose in patients with renal impairment_myelodysplastic syndromes Category Renal function (Cockcroft-Gault CLcr) Dose adjustment in myelodysplastic syndromes Initial dose 1st dose reduction 2nd dose reduction Moderate renal impairment 30 ≤ CLcr <50mL/min 5mg once daily (days 1 ~ 21 of each 28-day cycle) 2.5mg once daily (days 1 ~ 28 of each 28-day cycle) 2.5mg every other day (days 1 ~ 28 of each 28-day cycle) Severe renal impairment CLcr <30mL/min (non-dialysis patients) 2.5mg once daily (days 1 ~ 21 of each 28-day cycle) 2.5mg every other day (days 1 ~ 28 of each 28-day cycle) 2.5mg twice weekly (days 1 ~ 28 of each 28-day cycle) End-stage renal disease CLcr <30mL/min (dialysis patients) 2.5mg once daily (days 1 ~ 21 of each 28-day cycle) 2.5mg every other day (days 1 ~ 28 of each 28-day cycle) 2.5mg twice weekly (days 1 ~ 28 of each 28-day cycle) Administer after dialysis on dialysis days Administer after dialysis on dialysis days Administer after dialysis on dialysis days Table 17. Dose in patients with renal impairment_follicular lymphoma Category Renal function (Cockcroft-Gault CLcr) Dose adjustment in follicular lymphoma (days 1 ~ 21 of each 28-day cycle) Moderate renal impairment 30 ≤ CLcr < 60mL/min 10mg once daily1,2 Severe renal impairment CLcr < 30mL/min (non-dialysis patients) No data3 End-stage renal disease CLcr < 30mL/min (dialysis patients) No data3 ¹After the second treatment cycle, the dose may be increased to 15mg once daily if tolerated by the patient. 2For patients receiving an initial dose of 10mg, if the dose is reduced due to grade 3/4 neutropenia or thrombocytopenia, or another grade 3/4 toxicity considered related to this drug, do not reduce below 5mg every other day or 2.5mg once daily. 3Patients with severe renal impairment and end-stage renal disease were excluded from clinical trials. After starting treatment with this drug, dose adjustments in patients with renal impairment should be made according to the tolerability of each individual patient, as described above. 8. Take with water. Do not crush, chew, or open the capsule. The dose may be adjusted according to clinical or laboratory test results.
This drug should not be taken during pregnancy due to a very high risk of severe birth defects or miscarriage. Women of childbearing potential must have two pregnancy tests before taking this medication and should use effective contraception methods for a specified period before and after treatment. Only doctors and pharmacists registered in the special pregnancy prevention program can prescribe and dispense this medication, and patients must adhere to the regulations of this program. There may be a decrease in white blood cells and platelets in the blood, so regular blood tests are necessary to monitor the status. Dose adjustments or additional treatment may be required if necessary. Cardiovascular issues such as heart attacks may occur, so patients with risk factors for heart disease must be observed more carefully. There is an increased risk of thrombosis, so patients with a history of thrombosis or risk factors require prevention and monitoring. If symptoms develop, immediate consultation with medical personnel is necessary. This drug may increase the risk of secondary primary malignancies, so regular cancer screenings and careful observation are required before and during treatment. Liver function may be impaired, so patients with a history of liver disease or suspected liver dysfunction should have regular liver function tests and may need dose adjustments. In patients with reduced kidney function, the excretion of this drug may be delayed, necessitating dose adjustments and monitoring of kidney function. In patients with high tumor burden, tumor flare reactions or tumor lysis syndrome may occur at the beginning of treatment, so these should be prevented and symptoms carefully monitored. Patients may be susceptible to infections; thus, prompt consultation with medical personnel is required if any infection symptoms arise, and attention must be paid to infection prevention. Patients with a history of herpes zoster or hepatitis B virus infections are at risk of reactivation of the virus, hence viral status should be checked before treatment, and close monitoring should continue during treatment. There have been reports of fatal pulmonary hypertension, so cardiopulmonary function should be evaluated before and during treatment, and immediate action should be taken if any abnormal symptoms arise. If severe skin reactions or allergy symptoms occur during treatment, patients should stop taking the medication immediately and inform medical personnel. Elderly patients, patients with reduced kidney function, and those with poor overall condition may be more sensitive to the side effects of this drug, so careful management of dosage and treatment response is necessary.
Skeletal dysplasia, congenital malformation, miscarriage, neutropenia, thrombocytopenia, febrile reactions, symptoms of bleeding, myocardial infarction, venous thromboembolism, arterial thromboembolism, secondary primary malignancy, acute myeloid leukemia, myelodysplastic syndrome, liver failure, acute liver failure, toxic hepatitis, cytolytic hepatitis, cholestatic hepatitis, liver dysfunction, vascular edema, anaphylactic reaction, Stevens-Johnson syndrome, toxic epidermal necrolysis, drug eruption syndrome with eosinophilia and systemic symptoms, pulmonary hypertension, tumor lysis reaction, tumor lysis syndrome, infection, pneumonia, renal failure, pulmonary embolism, lung infection, fever, fatigue, constipation, diarrhea, muscle cramps, anemia, rash, decreased appetite, cough, weakness, insomnia, back pain, lethargy, peripheral neuropathy, paresthesia, dizziness, tremor, dysgeusia, headache, stroke, syncope, neuralgia, ataxia, impaired balance, intracranial hemorrhage, transient ischemic attack, cerebral ischemia, cataract, blurring, visual impairment, blindness, hearing loss, tinnitus, atrial fibrillation, bradycardia, congestive heart failure, tachycardia, heart failure, myocardial ischemia, arrhythmia, QT prolongation, atrial flutter, ventricular ectopic beats, hypotension, hypertension, petechiae, vasculitis, ischemia, peripheral ischemia, intracranial venous sinus thrombosis, dyspnea, epistaxis, respiratory distress, pleuritic pain, hypoxia, voice disorder, abdominal pain, nausea, vomiting, dyspepsia, dry mouth, stomatitis, gastrointestinal bleeding, small bowel obstruction, colitis, appendicitis, increased alanine aminotransferase, increased aspartate aminotransferase, hepatotoxicity, hepatocellular damage, hyperbilirubinemia, urticaria, hyperhidrosis, dry skin, skin pigmentation, eczema, erythema, drug rash, skin depigmentation, photosensitivity reactions, muscle weakness, bone pain, musculoskeletal and connective tissue pain, arthralgia, joint edema, renal failure, renal tubular necrosis, hematuria, urinary retention, incontinence, acquired Fanconi syndrome, erectile dysfunction, edema, influenza-like symptoms, drowsiness, increased serum alkaline phosphatase, increased C-reactive protein, falls, contusions, pneumococcal pneumonia, sepsis, Pneumocystis pneumonia, Klebsiella pneumonia, Legionella pneumonia, Mycoplasma pneumonia, streptococcal pneumonia, viral pneumonia, pulmonary abnormalities, interstitial pneumonia, pulmonary arterial hypertension, Stevens-Johnson syndrome, toxic epidermal necrolysis, DRESS syndrome, acquired hemophilia, pneumonia, septic shock, influenza, pulmonary embolism, pleural effusion, interstitial pneumonia, acute respiratory distress syndrome, bronchiectasis, pneumothorax, chronic obstructive pulmonary disease, congestion, tachypnea, oropharyngeal pain, mediastinal emphysema, pulmonary edema, pulmonary congestion, pulmonary mass, bronchial obstruction, respiratory abnormalities, hiccups, peripheral motor neuropathy, dementia, myoclonus, neuralgic pain, speech disorder, epilepsy, intracranial mass, chronic polyneuropathy, cauda equina syndrome, discomfort in the head, hemiplegia, seizures, neuritis, uremic encephalopathy, cognitive impairment, paresthesia of the jaw, third cranial nerve palsy, Parkinson's disease, post-herpetic neuralgia, action tremor, hyperkalemia, hypercalcemia, hypoalbuminemia, hypoglycemia, hyperphosphatemia, diabetic ketoacidosis, metabolic acidosis, iron deficiency, delirium, anxiety, bipolar disorder, changes in mental status, attention deficit disorder, shock, pericardial effusion, stress-induced cardiomyopathy, subendocardial ischemia, cardiac arrest, restrictive cardiomyopathy, Prinzmetal angina, vertebral compression fracture, rib fracture, femoral neck fracture, radiation pneumonia, spinal cord injury, spinal fracture, forearm fracture, thoracic vertebra fracture, acute kidney injury, dysuria, azotemia, end-stage renal disease, polyuria, nocturia, urinary abnormalities, urethral discharge, mucosal inflammation, swelling, multiple organ failure, multiorgan dysfunction, death, warmth, injection site pain, blisters, petechiae, skin hyperpigmentation, papular scaly rash, chronic pigmented erythema, exfoliative dermatitis, macules, purpuric rash, contact dermatitis, hair loss, skin reactions, skin lesions, skin peeling, subcutaneous hemorrhage, jaw pain, osteoporosis, joint stiffness, bone resorption, limb discomfort, rhabdomyolysis, chest wall mass, pustular rash, gingivitis, increased serum creatinine, weight gain, decreased renal creatinine clearance, increased serum alkaline phosphatase, increased international normalized ratio, positive influenza A virus test, increased blood urea, increased serum lactate dehydrogenase, conjunctival hemorrhage, borderline glaucoma, myopia, dry eyes, eyelid swelling, eye pain, retinal disorders, retinopathy, diplopia, blepharitis, periorbital edema, pericardial effusion, stress-induced cardiomyopathy, subendocardial ischemia, cardiac arrest, restrictive cardiomyopathy, atrial fibrillation, cardiac arrest, benign prostatic hyperplasia, female genital fistula, cervical dysplasia, vaginal discharge, vaginal bleeding, perineal rash, hyperbilirubinemia, liver dysfunction, fatty liver disease, acute cholangitis, acute cholecystitis, bile duct stones, jaundice, adrenal insufficiency, Cushing's syndrome, inappropriate antidiuretic hormone secretion, cervical dysplasia, diplopia, ear discomfort, ear pus, hearing loss, hemolytic uremic syndrome, hypoglobulinemia, Candidaemia
Not everyone experiences these, and they can vary from person to person.
This medication should be stored in a tightly closed container to prevent exposure to air or moisture. Additionally, it should be kept in a cool place between 15 to 30 degrees Celsius to maintain its efficacy.
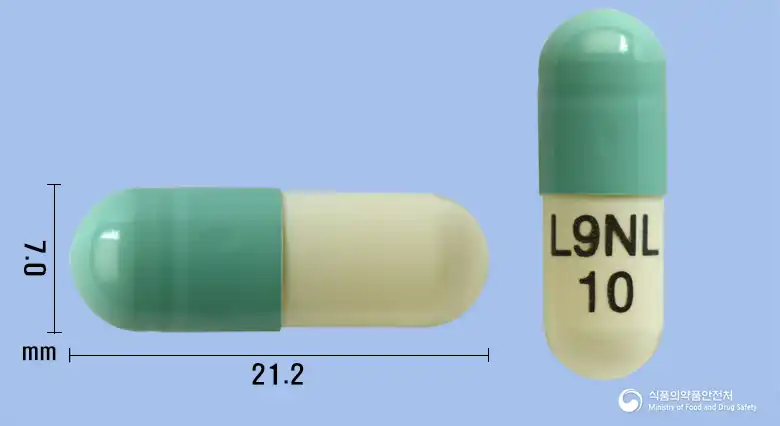
Opaque green hard capsule with opaque yellow bottom containing white or nearly white powder
21 capsules/case (3 capsules/PTPX7)
Even with the same ingredient, strength, dosage form and how it is taken can differ.
Viewing nowLenalidomide 10mg
Hard capsule · Prescription medication
Kwangdong Pharmaceutical Co., Ltd.

Lenalidomide Hemihydrate 5.17mg
Hard capsule · Prescription medication
(Yoo) Korea BMS Pharmaceuticals Co., Ltd.

Lenalidomide Hemihydrate 10.35mg
Hard capsule · Prescription medication
Korea BMS Pharmaceutical Co., Ltd.

Lenalidomide Hemihydrate 15.52mg
Hard capsule · Prescription medication
(Yoo) Han-kook BMS Pharmaceutical Co., Ltd.

Lenalidomide Hemihydrate 25.87mg
Hard capsule · Prescription medication
Korea BMS Pharmaceutical Co., Ltd.
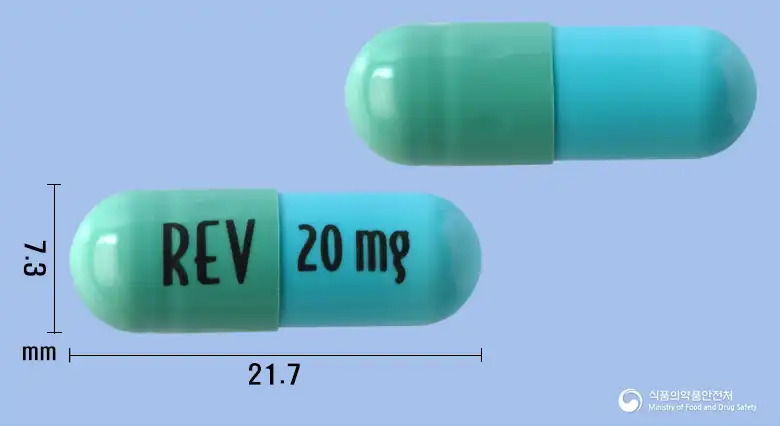
Lenalidomide Hydrate 20.7mg
Hard capsule · Prescription medication
Korean BMS Pharmaceutical Co., Ltd.
Lenalidomide Hydrate 7.76mg
Prescription medication
Celgene Corp.
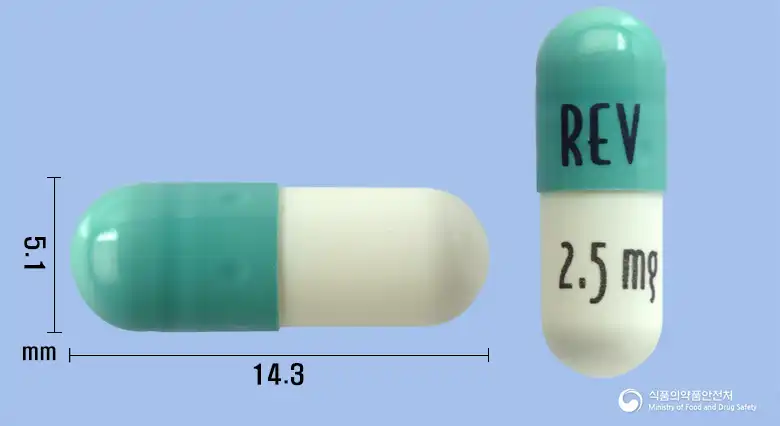
Lenalidomide Hydrate 2.59mg
Hard capsule · Prescription medication
Korea BMS Pharmaceutical Co., Ltd.
Even with the same ingredient, the dose and directions can differ by strength and dosage form. Talk to a doctor or pharmacist before switching from a medication you are already taking.
No questions yet.
For anything that needs medical judgment, consult a doctor or pharmacist.
This drug information is based on data provided by the Korea Ministry of Food and Drug Safety.
Consult a doctor or pharmacist for accurate dosage, administration, and usage instructions.