
 한국어
 English
 日本語
 中文(简体)
 Viewing now
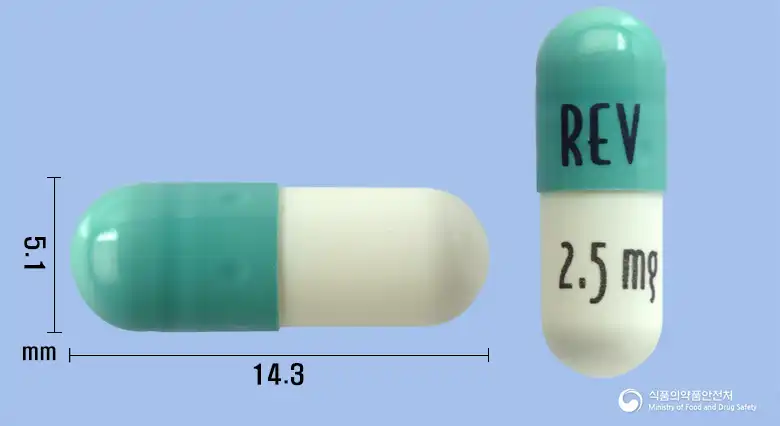
Revlimid Capsule 2.5 mg (Lenalidomide)
Lenalidomide Hydrate 2.59mg
Hard capsule · Prescription medication
Korea BMS Pharmaceutical Co., Ltd.
MFDS item code 201600615 · Approved 2016.01.29 · Insurance code 658700920,691800160
Treatment of multiple myeloma, lymphoma (mantle cell and follicular), and anemia due to myelodysplastic syndromes
This medication is used for the treatment of multiple myeloma, myelodysplastic syndromes with 5q cytogenetic deletion, mantle cell lymphoma, and follicular lymphoma. In particular, for multiple myeloma, it is used in various combination therapies for patients who have been previously treated as well as for newly diagnosed patients, and is also utilized for maintenance therapy. It is administered to improve anemia in cases of myelodysplastic syndromes, and provides effective treatment for certain types of lymphoma. This therapy helps achieve optimal effects tailored to the patient's condition. Therefore, this medication is widely used for the treatment of various blood cancers and related hematological disorders.
This medicine should be administered only to patients who agree to comply with the requirements specified in the Pregnancy Prevention Program (see “5. General Precautions” under Precautions for Use). In addition, this medicine should be prescribed only by physicians registered with the Pregnancy Prevention Program and dispensed only by pharmacists registered with the program. When prescribing to women of childbearing potential, negative pregnancy test results must be confirmed continuously according to the schedule specified in this program. 1. Multiple myeloma 1) In combination with dexamethasone for the treatment of patients who have received at least one prior therapy Treatment should not be initiated if the absolute neutrophil count is <1,000/㎕ and/or the platelet count is <75,000/㎕. The recommended initial dose is 25mg once daily. Take 25mg capsules on days 1–21 of each 28-day cycle. The recommended dose of dexamethasone is 40mg once daily on days 1–4, 9–12, and 17–20 of each 28-day cycle for the first 4 cycles. After 4 cycles, administer 40mg once daily only on days 1–4 of each 28-day cycle. Dose adjustments during treatment ① Dose adjustment according to platelet count Table 1. Platelet count Recommended dose If decreased to <30,000/㎕ Interrupt treatment and monitor complete blood counts weekly When recovered to ≧30,000/㎕ Resume treatment at 15mg once daily If subsequently decreased to <30,000/㎕ Interrupt treatment When recovered to ≧30,000/㎕ Resume at a dose reduced by 5mg from the dose being administered. Do not reduce the dose to less than 5mg once daily. ② Dose adjustment according to absolute neutrophil count (ANC) Table 2. Absolute neutrophil count Recommended dose If decreased to <1,000/㎕ Interrupt treatment, add G-CSF, and monitor complete blood counts weekly When recovered to ≧1,000/㎕ and neutropenia is the only toxicity Resume treatment at 25mg once daily When recovered to ≧1,000/㎕ and other toxicities have occurred Resume treatment at 15mg once daily If subsequently decreased to <1,000/㎕ Interrupt treatment When recovered to ≧1,000/㎕ Resume at a dose reduced by 5mg from the dose being administered. Do not reduce the dose to less than 5mg once daily. For neutropenia, use of growth factors should be considered for patient management. 2) In combination with dexamethasone for the treatment of newly diagnosed patients who are not eligible for transplantation Treatment should not be initiated if the absolute neutrophil count is <1,000/㎕ and/or the platelet count is <50,000/㎕. The recommended initial dose is 25mg once daily. Take 25 mg capsules on days 1–21 of each 28-day cycle. The recommended dose of dexamethasone is 40mg once daily on days 1, 8, 15, and 22 of each 28-day cycle. For patients aged 75 years or older, the recommended dose of dexamethasone is 20mg once daily on days 1, 8, 15, and 22 of each 28-day cycle. Continue treatment until disease progression or unacceptable toxicity occurs. Dose adjustments during treatment <Dose reduction levels> This medicine Dexamethasone Initial dose 25 mg 40 mg First dose reduction 20 mg 20 mg Second dose reduction 15 mg 12 mg Third dose reduction 10 mg 8 mg Fourth dose reduction 5 mg 4 mg Fifth dose reduction 2.5 mg N/A ① Dose adjustment according to platelet count Table 3. Platelet count Recommended dose If decreased to <25,000/㎕ Interrupt this medicine and dexamethasone and monitor complete blood counts weekly When recovered to ≧50,000/㎕ Resume at one dose level below the dose being administered ② Dose adjustment according to absolute neutrophil count (ANC) Table 4. Absolute neutrophil count Recommended dose If decreased to <500/㎕ Interrupt this medicine and dexamethasone and monitor complete blood counts weekly When recovered to ≧1,000/㎕ and neutropenia is the only toxicity Resume treatment at the starting dose When recovered to ≧500/㎕ and dose-dependent hematologic toxicity other than neutropenia has occurred Resume at one dose level below the dose being administered If subsequently decreased to <500/㎕ Interrupt this medicine and dexamethasone When recovered to ≧500/㎕ Resume at one dose level below the dose being administered For neutropenia, use of growth factors should be considered for patient management. ③ Dose adjustment for febrile neutropenia (fever ≥38.5℃ and ANC <1,000/㎕): Interrupt treatment and monitor complete blood counts weekly. If the patient is not receiving a growth factor, use of a growth factor should be considered. On the first day of the next treatment cycle, if neutropenia was the only dose-limiting toxicity, resume treatment at the dose being administered, continuing growth factor use if necessary. Otherwise, resume treatment at one dose level below the dose being administered. If the patient is not receiving a growth factor, administer a growth factor. If this medicine was reduced because of hematologic dose-limiting toxicity (DLT), treatment may be resumed at an increased dose, at the physician’s discretion (up to the maximum starting dose), if bone marrow function improves during continued treatment (no DLT for at least 2 consecutive cycles, and, at the start of a new cycle at the current dose level, an absolute neutrophil count ≥1,500/㎕ and platelet count ≥100,000/㎕). 3) In combination with melphalan and prednisolone for the treatment of newly diagnosed patients who are not eligible for transplantation Treatment should not be initiated if the absolute neutrophil count is <1,500/㎕ and/or the platelet count is <75,000/㎕. The recommended initial dose is 10mg once daily. Take 10 mg capsules on days 1–21 of each 28-day cycle. Through cycle 9, administer melphalan orally at a dose of 0.18mg/kg on days 1–4 of each 28-day cycle, and administer prednisolone orally at a dose of 2mg/kg on days 1–4 of each 28-day cycle. For patients who have completed 9 cycles or cannot complete combination therapy because of tolerability, administer this medicine alone at 10mg once daily on days 1–21 of each 28-day cycle until disease progression. Dose adjustments during treatment <Dose reduction levels> This medicine Melphalan Prednisolone Initial dose 10 mg 0.18 mg/kg 2 mg/kg First dose reduction 7.5 mg 0.14 mg/kg 1 mg/kg Second dose reduction 5 mg 0.10 mg/kg 0.5 mg/kg Third dose reduction 2.5 mg N/A 0.25 mg/kg ① Dose adjustment according to platelet count Table 5. Platelet count Recommended dose If decreased to <25,000/㎕ Interrupt this medicine, melphalan, and prednisolone and monitor complete blood counts weekly When recovered to ≧25,000/㎕ Resume treatment with this medicine and melphalan at one dose level below the dose being administered If subsequently decreased to <30,000/㎕ Interrupt this medicine, melphalan, and prednisolone When recovered to ≧30,000/㎕ Resume treatment with this medicine and melphalan at one dose level below the dose being administered ② Dose adjustment according to absolute neutrophil count (ANC) Table 6. Absolute neutrophil count Recommended dose If decreased to <500/㎕ Interrupt this medicine, melphalan, and prednisolone and monitor complete blood counts weekly When recovered to ≧500/㎕ and neutropenia is the only toxicity Resume treatment at the starting dose When recovered to ≧500/㎕ and dose-dependent hematologic toxicity other than neutropenia has occurred Resume treatment with this medicine and melphalan at one dose level below the dose being administered If subsequently decreased to <500/㎕ Interrupt this medicine, melphalan, and prednisolone When recovered to ≧500/㎕ Resume treatment with this medicine and melphalan at one dose level below the dose being administered For neutropenia, use of growth factors should be considered for patient management. ③ Dose adjustment for febrile neutropenia (fever ≥38.5℃ and ANC <1,000/㎕): Interrupt this medicine, melphalan, and prednisolone and monitor complete blood counts weekly. If the patient is not receiving a growth factor, use of a growth factor should be considered. On the first day of the next treatment cycle, if neutropenia was the only dose-limiting toxicity, resume treatment at the dose being administered, continuing growth factor use if necessary. Otherwise, resume treatment at one dose level below the dose being administered. If the patient is not receiving a growth factor, administer a growth factor. 4) In combination with bortezomib and dexamethasone for the treatment of newly diagnosed patients (1) In combination with bortezomib and dexamethasone for the treatment of newly diagnosed patients who are not eligible for transplantation Treatment should not be initiated if the absolute neutrophil count is <1,000/㎕ and/or the platelet count is <80,000/㎕. The recommended initial dose of this medicine is 25mg once daily, taken on days 1–14 of each 21-day cycle. Bortezomib is administered by subcutaneous injection at a dose of 1.3mg/m2 per body surface area on days 1, 4, 8, and 11 of each 21-day cycle. The recommended dose of dexamethasone is 20mg once daily, taken on days 1, 2, 4, 5, 8, 9, 11, and 12 of each 21-day cycle. Patients should receive 8 cycles (24 weeks total) of treatment as initial therapy. After initial therapy, take this medicine 25mg once daily in combination with dexamethasone on days 1–21 of each 28-day cycle. The recommended dose of dexamethasone is 40mg once daily on days 1, 8, 15, and 22 of each 28-day cycle. For patients aged 75 years or older, the starting dose of dexamethasone is 20mg once daily on days 1, 8, 15, and 22 of each 28-day cycle. Treatment may continue until disease progression or unacceptable toxicity occurs. (2) Induction therapy with dexamethasone and bortezomib for the treatment of newly diagnosed patients who are eligible for transplantation Treatment should not be initiated if the absolute neutrophil count is <1,000/㎕ and/or the platelet count is <80,000/㎕. The recommended initial dose of this medicine is 25mg once daily, taken on days 1–21 of each 28-day cycle. Bortezomib is administered by subcutaneous injection at a dose of 1.3mg/m2 per body surface area on days 1, 4, 8, and 11 of each 28-day cycle. The recommended dose of dexamethasone is 40mg once daily, taken on days 1–4 and 9–12 of each 28-day cycle. Patients should receive 6 cycles (24 weeks total) of treatment as induction therapy. Dose adjustments during treatment <Dose reduction levels> This medicine Initial dose 25 mg First dose reduction 20 mg Second dose reduction 15 mg Third dose reduction 10 mg Fourth dose reduction 5 mg Fifth dose reduction 2.5 mg ① Dose adjustment according to platelet count Platelet count Recommended dose If decreased to <30,000/㎕ Interrupt treatment and monitor complete blood counts weekly When recovered to ≧50,000/㎕ Resume at one dose level below the dose being administered If subsequently decreased to <30,000/㎕ Interrupt treatment When recovered to ≧50,000/㎕ Resume at one dose level below the dose being administered ② Dose adjustment according to absolute neutrophil count (ANC) Neutrophil count Recommended dose If decreased to <500/㎕ Interrupt treatment and monitor complete blood counts weekly When recovered to ≧1,000/㎕ and neutropenia is the only toxicity Resume treatment at the starting dose When recovered to ≧500/㎕ and dose-dependent hematologic toxicity other than neutropenia has occurred Resume at one dose level below the dose being administered If subsequently decreased to <500/㎕ Interrupt treatment When recovered to ≧500/㎕ Resume at one dose level below the dose being administered For neutropenia, use of growth factors should be considered for patient management. *For dose adjustments of concomitant medicines, refer to the prescribing information for the respective product. 5) Maintenance therapy for newly diagnosed patients who have undergone autologous hematopoietic stem cell transplantation Maintenance therapy with this medicine should be initiated after adequate hematologic recovery following autologous hematopoietic stem cell transplantation in patients with no evidence of disease progression. Treatment should not be initiated if the absolute neutrophil count is <1,000/㎕ and/or the platelet count is <75,000/㎕. The recommended initial dose is 10mg once daily. Take 10 mg capsules on days 1–28 of each 28-day cycle until intolerance or disease progression occurs. After 3 cycles of maintenance therapy with this medicine, the dose may be increased to 15mg once daily if tolerated. Dose adjustments during treatment <Dose reduction levels> Starting dose (10mg) If the dose has been increased (15mg)* First dose reduction 5 mg 10 mg Second dose reduction 5mg (days 1–21 of each 28-day cycle) 5 mg Third dose reduction N/A 5mg (days 1–21 of each 28-day cycle) Do not reduce the dose to less than 5mg (days 1–21 of each 28-day cycle). *After 3 cycles of maintenance therapy with this medicine, the dose may be increased to 15mg once daily if tolerated. ① Dose adjustment according to platelet count Table 7. Platelet count Recommended dose If decreased to <30,000/㎕ Interrupt treatment and monitor complete blood counts weekly When recovered to ≧30,000/㎕ Resume treatment at one dose level below the dose being administered If subsequently decreased to <30,000/㎕ Interrupt treatment When recovered to ≧30,000/㎕ Resume treatment at one dose level below the dose being administered ② Dose adjustment according to absolute neutrophil count (ANC) Table 8. Absolute neutrophil count Recommended dose If decreased to <500/㎕ Interrupt treatment and monitor complete blood counts weekly When recovered to ≧500/㎕ Resume treatment at one dose level below the dose being administered If subsequently decreased to <500/㎕ Interrupt treatment When recovered to ≧500/㎕ Resume treatment at one dose level below the dose being administered For neutropenia, use of growth factors should be considered for patient management. 2. Myelodysplastic syndromes Treatment should not be initiated if the absolute neutrophil count is <500/㎕ and/or the platelet count is <25,000/㎕. The recommended initial dose is 10mg once daily. Take 10 mg capsules on days 1–21 of each 28-day cycle. Dose adjustments during treatment <Dose reduction levels> This medicine Initial dose 10 mg once daily on days 1–21 of each 28-day cycle First dose reduction 5 mg once daily on days 1–28 of each 28-day cycle Second dose reduction 2.5 mg once daily on days 1–28 of each 28-day cycle Third dose reduction 2.5 mg every other day on days 1–28 of each 28-day cycle ① Dose adjustment according to platelet count Table 9. Platelet count Recommended dose If decreased to <25,000/㎕ Interrupt treatment and monitor complete blood counts weekly When recovered to ≧50,000/㎕, or when recovered to ≧25,000/㎕ to <50,000/㎕ at least 2 times over 7 days or longer Resume at one dose level below the dose being administered ② Dose adjustment according to absolute neutrophil count (ANC) Table 10. Absolute neutrophil count Recommended dose If decreased to <500/㎕ Interrupt treatment and monitor complete blood counts weekly When recovered to ≧500/㎕ Resume at one dose level below the dose being administered For neutropenia, use of growth factors should be considered for patient management. Discontinue treatment with this medicine in patients who have not achieved at least a minor erythroid response within 4 months after starting treatment (demonstrated by at least a 50% reduction in transfusion requirements or, in patients who did not require transfusions, an increase in hemoglobin level of 1g/dl). 3. Mantle cell lymphoma The recommended initial dose is 25mg once daily. Take 25mg capsules on days 1–21 of each 28-day cycle. Dose adjustments during treatment <Dose reduction levels> This medicine Initial dose 25mg once daily on days 1–21 of each 28-day cycle First dose reduction 20mg once daily on days 1–21 of each 28-day cycle Second dose reduction 15mg once daily on days 1–21 of each 28-day cycle Third dose reduction 10mg once daily on days 1–21 of each 28-day cycle Fourth dose reduction 5mg once daily on days 1–21 of each 28-day cycle Fifth dose reduction 2.5mg once daily on days 1–21 of each 28-day cycle 5mg every other day on days 1–21 of each 28-day cycle ① Dose adjustment according to platelet count Table 11. Platelet count Recommended dose If decreased to <50,000/㎕ Interrupt treatment and monitor complete blood counts weekly When recovered to ≧60,000/㎕ Resume at one dose level below the dose being administered If subsequently decreased to <50,000/㎕ Interrupt treatment and monitor complete blood counts weekly When recovered to ≧60,000/㎕ Resume at one dose level below the dose being administered Do not reduce the dose to less than 2.5mg once daily or less than 5mg every other day. ② Dose adjustment according to absolute neutrophil count (ANC) Table 12. Absolute neutrophil count Recommended dose If decreased to <1,000/㎕ for at least 7 days, or if decreased to <1,000/㎕ with fever (temperature ≧38.5℃), or if decreased to <500/㎕ Interrupt treatment and monitor complete blood counts weekly When recovered to ≧1,000/㎕ Resume at one dose level below the dose being administered If subsequently decreased to <1,000/㎕ for at least 7 days, or if decreased to <1,000/㎕ with fever (temperature ≧38.5℃), or if decreased to <500/㎕ Interrupt treatment. When recovered to ≧1,000/㎕ Resume at one dose level below the dose being administered Do not reduce the dose to less than 2.5mg once daily or less than 5mg every other day. For neutropenia, use of growth factors should be considered for patient management. 4. Follicular lymphoma Treatment should not be initiated if the absolute neutrophil count is <1,000/㎕ and/or the platelet count is <50,000/㎕ (except when secondary to lymphoma involvement of the bone marrow). The recommended initial dose is 20mg once daily. Take 20mg capsules on days 1–21 of each 28-day cycle. Treat for up to 12 cycles. The recommended initial dose of rituximab is based on a 28-day cycle and is 375 mg/m2 administered intravenously once weekly during cycle 1 (days 1, 8, 15, and 22). During cycles 2–5, administer 375 mg/m2 intravenously only on day 1 of each 28-day cycle. Dose adjustments during treatment <Dose reduction levels> This medicine Initial dose 20mg once daily on days 1–21 of each 28-day cycle First dose reduction 15mg once daily on days 1–21 of each 28-day cycle Second dose reduction 10mg once daily on days 1–21 of each 28-day cycle Third dose reduction 5mg once daily on days 1–21 of each 28-day cycle For dose adjustments due to rituximab toxicity, refer to the relevant prescribing information. ① Dose adjustment according to platelet count Table 13. Platelet count Recommended dose If decreased to <50,000/㎕ Interrupt treatment with this medicine and monitor complete blood counts weekly When recovered to ≥50,000/㎕ Resume at one dose level below the dose being administered If subsequently decreased to <50,000/㎕ Interrupt treatment with this medicine and monitor complete blood counts weekly When recovered to ≥50,000/㎕ Resume at one dose level below the dose being administered Do not reduce the dose to less than 5mg once daily. ② Dose adjustment according to absolute neutrophil count (ANC) Table 14. Absolute neutrophil count Recommended dose If decreased to <1,000/㎕ for at least 7 days or if decreased to <1,000/㎕ with fever (temperature ≥38.5°C), or if decreased to <500/㎕ Interrupt treatment with this medicine and monitor complete blood counts weekly When recovered to ≥1,000/㎕ Resume at one dose level below the dose being administered If subsequently decreased to <1,000/㎕ for at least 7 days, or if decreased to <1,000/㎕ with fever (temperature ≥38.5°C), or if decreased to <500/㎕ Interrupt treatment with this medicine and monitor complete blood counts weekly When recovered to ≥1,000/㎕ Resume at one dose level below the dose being administered Do not reduce the dose to less than 5mg once daily. Mantle cell lymphoma or follicular lymphoma Tumor lysis syndrome (TLS) All patients should receive tumor lysis syndrome prophylaxis (allopurinol, rasburicase, or an equivalent regimen according to institutional treatment guidelines) and adequate oral hydration during the first week of the first treatment cycle, or for a longer period if clinically necessary. To monitor for tumor lysis syndrome, patients should undergo a chemistry panel during the first cycle and weekly when clinically necessary. For patients with laboratory TLS or grade 1 clinical TLS, this medicine may be continued at the same dose or, at the physician’s discretion, continued at a dose reduced by one level. Provide adequate intravenous hydration and appropriate medical management in accordance with standard treatment until electrolyte abnormalities have been corrected. Rasburicase treatment may be needed to reduce hyperuricemia. The decision to hospitalize the patient is at the physician’s discretion. For patients with grade 2–4 clinical TLS, discontinue this medicine and perform a chemistry panel weekly or as clinically necessary. Provide adequate intravenous hydration and appropriate medical management in accordance with standard treatment until electrolyte abnormalities have been corrected. The decision to use rasburicase and hospitalize the patient is at the physician’s discretion. When TLS improves to grade 0, resume treatment at one dose level lower, at the physician’s discretion. Tumor flare reaction (TFR) For patients who develop grade 1/2 tumor flare reaction, treatment with this medicine may continue without interruption or dose reduction, at the prescriber’s discretion. At the prescriber’s discretion, non-steroidal anti-inflammatory drugs (NSAIDs), a limited course of corticosteroids, and/or narcotic analgesics may be administered. For patients who develop grade 3/4 tumor flare reaction, discontinue this medicine and initiate treatment with NSAIDs, corticosteroids, and/or narcotic analgesics. When the reaction resolves to grade 1 or lower, resume treatment at the same dose for the remainder of the cycle. The patient may receive symptom management according to the guidance for treatment of grade 1/2 tumor flare reaction. 5. Dose adjustment for other grade 3/4 toxicities If other grade 3/4 toxicities associated with this medicine occur, interrupt treatment. Once the toxicity resolves to grade 2 or lower, resume treatment at a dose one level below the dose being administered, at the prescriber’s discretion. 6. This medicine should not be administered to patients with a history of grade 4 rash caused by thalidomide. For grade 2–3 skin rash, interruption or discontinuation of this medicine should be considered. If angioedema, anaphylactic reactions, grade 4 rash, exfoliative or bullous rash occurs, or Stevens-Johnson syndrome, toxic epidermal necrolysis, or drug reaction with eosinophilia and systemic symptoms (DRESS syndrome) is suspected, treatment should be discontinued and should not be resumed even after the reaction resolves. 7. Dosage in patients with renal impairment Because this medicine is excreted through the kidneys, toxicity may be greater in patients with renal impairment. Renal impairment is more common in elderly patients; therefore, caution is required when selecting the dose, and careful monitoring of renal function is necessary. The initial doses for patients with renal impairment are as follows. This medicine has not been studied in non-dialysis patients with creatinine clearance below 11 mL/min or in patients with creatinine clearance below 7 mL/min. Table 15. Initial dose in patients with renal impairment_Multiple myeloma or mantle cell lymphoma Category Renal function (Cockcroft-Gault CLcr) Dose adjustment for multiple myeloma/mantle cell lymphoma Dose adjustment for post-transplant maintenance therapy Moderate renal impairment 30 ≤ CLcr <50mL/min 10mg once daily* 5mg once daily Severe renal impairment CLcr <30mL/min (non-dialysis patient) 7.5mg once daily or 15mg every other day 2.5mg once daily End-stage renal disease CLcr <30mL/min (dialysis patient) 5mg once daily Administer after dialysis on dialysis days 2.5mg once daily Administer after dialysis on dialysis days *After the second treatment cycle, the dose may be increased to 15mg once daily if the patient has not responded to treatment and tolerates it. Table 16. Initial dose in patients with renal impairment_Myelodysplastic syndromes Category Renal function (Cockcroft-Gault CLcr) Dose adjustment for myelodysplastic syndromes Initial dose First dose reduction Second dose reduction Moderate renal impairment 30 ≤ CLcr <50mL/min 5mg once daily (days 1–21 of each 28-day cycle) 2.5mg once daily (days 1–28 of each 28-day cycle) 2.5mg every other day (days 1–28 of each 28-day cycle) Severe renal impairment CLcr <30mL/min (non-dialysis patient) 2.5mg once daily (days 1–21 of each 28-day cycle) 2.5mg every other day (days 1–28 of each 28-day cycle) 2.5mg twice weekly (days 1–28 of each 28-day cycle) End-stage renal disease CLcr <30mL/min (dialysis patient) 2.5mg once daily (days 1–21 of each 28-day cycle) 2.5mg every other day (days 1–28 of each 28-day cycle) 2.5mg twice weekly (days 1–28 of each 28-day cycle) Administer after dialysis on dialysis days Administer after dialysis on dialysis days Administer after dialysis on dialysis days Table 17. Dose in patients with renal impairment_Follicular lymphoma Category Renal function (Cockcroft-Gault CLcr) Dose adjustment for follicular lymphoma (days 1–21 of each 28-day cycle) Moderate renal impairment 30 ≤ CLcr < 60mL/min 10mg once daily1,2 Severe renal impairment CLcr < 30mL/min (non-dialysis patient) 5 mg once daily End-stage renal disease CLcr < 30mL/min (dialysis patient) 5 mg once daily; administer after dialysis on dialysis days ¹After the second treatment cycle, the dose may be increased to 15mg once daily if the patient tolerates it. 2For patients starting at 10mg, if the dose is reduced because of grade 3/4 neutropenia or thrombocytopenia, or other grade 3/4 toxicity considered related to this medicine, do not reduce the dose below 5mg every other day or 2.5mg once daily. After starting treatment with this medicine, dose adjustments in patients with renal impairment should be made according to the individual patient’s tolerability, as described above. 8. Take with water. Do not crush, chew, or open the capsules. The dose may be adjusted according to clinical or laboratory test results.
This medication can cause serious birth defects or miscarriage if taken during pregnancy, so women who are pregnant or may become pregnant must absolutely avoid taking it. Women of childbearing potential must undergo two pregnancy tests before taking this medication and should avoid sexual intercourse or use two or more forms of contraception from four weeks prior to treatment, during treatment, and for four weeks after treatment ends. This medication can reduce the number of white blood cells and platelets in the blood, so regular blood tests are required before and during treatment, and any signs of infection or bleeding should be immediately reported to healthcare professionals. Patients at risk of heart disease may have an increased risk of myocardial infarction when using this medication, so cardiovascular condition should be carefully monitored. This medication can increase the risk of thrombosis (blood clotting in blood vessels), so patients with risk factors for thrombosis should be particularly cautious and seek immediate treatment if symptoms occur. Long-term use of this medication may increase the risk of secondary malignancies, so regular cancer screenings and careful observation are necessary before and during treatment. Patients with impaired liver function may require dosage adjustments, and if liver dysfunction is suspected, they should undergo testing and receive necessary intervention immediately. Patients with impaired kidney function also require dosage adjustments and monitoring of kidney function. High-risk patients may experience rapid tumor progression or tumor lysis syndrome, requiring careful observation and preventive measures upon starting treatment and during dose escalation. As they may be susceptible to infections, any symptoms of infection (such as fever, cough, etc.) should be promptly reported to healthcare professionals. This medication can cause severe skin reactions (such as Stevens-Johnson syndrome and toxic epidermal necrolysis), so if any skin rashes or abnormal symptoms occur, use should be stopped immediately, and a healthcare professional should be consulted. Pulmonary diseases such as pulmonary hypertension may develop, so pulmonary status should be evaluated before and during treatment, and any abnormal symptoms should be reported to healthcare professionals immediately. This medication should not be given to patients with specific genetic problems (such as lactose intolerance). Various adverse reactions may occur during treatment, so any symptoms such as fatigue, rashes, blood disorders, gastrointestinal symptoms, or neurological abnormalities should be carefully monitored, and if symptoms worsen, consultation with healthcare professionals is advised.
Skeletal deformities, congenital malformations, miscarriage, neutropenia, thrombocytopenia, feverish reactions, bleeding, myocardial infarction, venous thromboembolism, arterial thromboembolism, secondary primary malignant tumors, acute myeloid leukemia, myelodysplastic syndromes, liver failure, toxic hepatitis, cytolytic hepatitis, cholestatic hepatitis, vascular edema, anaphylaxis, Stevens-Johnson syndrome, toxic epidermal necrolysis, drug rash syndrome with eosinophilia and systemic symptoms, pulmonary hypertension, tumor-related fever, tumor lysis syndrome, pneumonia, renal failure, diarrhea, fatigue, back pain, weakness, insomnia, rash, decreased appetite, cough, fever, muscle cramps, hypotension, lung infection, dehydration, peripheral neuropathy, cataracts, blurring, visual impairment, blindness, hearing loss, tinnitus, atrial fibrillation, bradycardia, congestive heart failure, tachycardia, heart failure, myocardial ischemia, arrhythmia, QT prolongation, atrial flutter, ventricular premature contractions, hypertension, purpura, vasculitis, ischemia, peripheral ischemia, intracranial venous sinus thrombosis, dyspnea, epistaxis, respiratory distress, pleuritic pain, hypoxemia, voice disorders, abdominal pain, nausea, vomiting, dyspepsia, dry mouth, stomatitis, gastrointestinal bleeding, small bowel obstruction, colitis, appendicitis, alanine aminotransferase increase, aspartate aminotransferase increase, hepatotoxicity, hepatocyte damage, hyperbilirubinemia, urticaria, hyperhidrosis, dry skin, skin pigmentation, eczema, erythema, drug rash, skin depigmentation, photosensitivity, muscle weakness, bone pain, musculoskeletal and connective tissue pain, arthralgia, renal failure, hematuria, urinary retention, urinary incontinence, acquired Fanconi syndrome, erectile dysfunction, fatigue, edema, fever, influenza-like symptoms, increased serum alkaline phosphatase, increased C-reactive protein, falls, contusions, pulmonary embolism, pneumonia, sepsis, influenza, bronchitis, rhinitis, soft tissue infection, urinary tract infection, sinusitis, basal cell carcinoma, squamous cell skin cancer, T-cell acute leukemia, hemolytic anemia, hypersensitivity, hypothyroidism, hypokalemia, hyperglycemia, hypoglycemia, hypocalcemia, hyponatremia, dehydration, decreased appetite, weight loss, diabetes, hypophosphatemia, hyperuricemia, depression, insomnia, decreased libido, paresthesia, dizziness, tremors, dysgeusia, headache, stroke, syncope, neuralgia, ataxia, sensory disturbances, intracranial hemorrhage, transient ischemic attack, cerebral ischemia, cataracts, hearing loss, tinnitus, atrial fibrillation, myocardial infarction, congestive heart failure, heart failure, myocardial ischemia, arrhythmia, QT prolongation, atrial flutter, ventricular premature contractions, hypotension, hypertension, ischemia, peripheral ischemia, intracranial venous sinus thrombosis, dyspnea, cough, rash, itching, cold sweats, dry skin, muscle cramps, back pain, muscle weakness, arthralgia, limb pain, renal failure, lethargy, chills, malaise, hiccups, anxiety, sleep disturbances, abdominal distension, gastroesophageal reflux disease, oral pain, toothache, oral ulceration, chronic gastritis, gastritis, dental caries, hemorrhoids, ascites, ischemic colitis, colon ulcers, colon perforation, colon polyps, epigastric discomfort, erosive esophagitis, esophagitis, gastric ulcer, gum swelling, hemorrhagic diverticulitis, bowel obstruction, bowel stricture, rectal pain, periodontal disease, anal erosions, bloody stools, pleural effusion, asthma, postnasal drip, hemoptysis, acute respiratory distress syndrome, bronchiectasis, pneumothorax, chronic obstructive pulmonary disease, congestion, tachypnea, oropharyngeal pain, mediastinal emphysema, pulmonary hypertension, pulmonary edema, pulmonary congestion, lung nodules, obstructive bronchitis, respiratory abnormalities, pleuritic pain, peripheral neuropathy, dementia, necrotizing myopathy, neurogenic pain, speech disorders, epilepsy, intracranial mass, chronic polyneuropathy, Klippel-Feil syndrome, head discomfort, hemiplegia, seizures, neuritis, uremic encephalopathy, cognitive impairment, paresthesia syndrome, third cranial nerve palsy, Parkinson's disease, postherpetic neuralgia, action tremor, hyperkalemia, hypercalcemia, hypoalbuminemia, hypoglycemia, hyperphosphatemia, iron deficiency, delirium, restlessness, bipolar disorder, changes in mental state, attention deficit disorder, rib fractures, limb injuries, upper limb fractures, femoral neck fractures, femur fractures, radiation pneumonia, osteosarcoma, laceration, traumatic fractures, lumbar fractures, ligament sprains, spinal cord injury, tooth fractures, forearm fractures, thoracic spine fractures, urethral discomfort, end-stage renal disease, polyuria, nocturia, urinary abnormalities, urethral discharge, mucosal inflammation, swelling, multiple organ failure, multiple organ dysfunction, heat sensation, injection site pain, blisters, petechiae, skin pigmentation excess, papulosquamous rash, chronic pigmentation macules, exfoliative dermatitis, spots, contact dermatitis, hair loss, skin reactions, skin peeling, subcutaneous hemorrhage, jaw pain, osteoporosis, spondylolisthesis, joint stiffness, bone resorption, limb discomfort, rhabdomyolysis, chest wall mass, increased serum creatinine, weight gain, decreased renal creatinine clearance, increased serum alkaline phosphatase, increased international normalized ratio, positive influenza A virus test, increased serum urea, increased serum lactate dehydrogenase, conjunctival hemorrhage, borderline glaucoma, myopia, dry eyes, eyelid edema, eye pain, retinal disorders, retinopathy, diplopia, blepharitis, periocular edema, cardiac effusion, stress cardiomyopathy, subendocardial ischemia, cardiac arrest, restrictive cardiomyopathy, benign prostatic hyperplasia, female reproductive tract fistula, cervical dysplasia, vaginal discharge, vaginal bleeding, perineal rash, hyperbilirubinemia, liver dysfunction, fatty liver, acute cholangitis, acute cholecystitis, bile duct stones, jaundice, adrenal insufficiency, Cushing's syndrome, inappropriate secretion of antidiuretic hormone, hepatocellular carcinoma, cholangiocarcinoma, malignant pleural effusion, gastric cancer, flushing, shock, ear discomfort, ear pus, hearing deterioration, splenomegaly, hemolytic uremic syndrome, candidemia
Not everyone experiences these, and they can vary from person to person.
This medication should be stored in a tightly sealed container that is well-ventilated and kept at room temperature between 15 degrees and 30 degrees Celsius. Storing it this way helps maintain the drug's efficacy and safety.
A hard capsule with a green-blue upper and a white lower containing a white powder
7 capsules/package
Even with the same ingredient, strength, dosage form and how it is taken can differ.
Viewing nowLenalidomide Hydrate 2.59mg
Hard capsule · Prescription medication
Korea BMS Pharmaceutical Co., Ltd.

Lenalidomide Hemihydrate 5.17mg
Hard capsule · Prescription medication
(Yoo) Korea BMS Pharmaceuticals Co., Ltd.

Lenalidomide Hemihydrate 10.35mg
Hard capsule · Prescription medication
Korea BMS Pharmaceutical Co., Ltd.

Lenalidomide Hemihydrate 15.52mg
Hard capsule · Prescription medication
(Yoo) Han-kook BMS Pharmaceutical Co., Ltd.

Lenalidomide Hemihydrate 25.87mg
Hard capsule · Prescription medication
Korea BMS Pharmaceutical Co., Ltd.
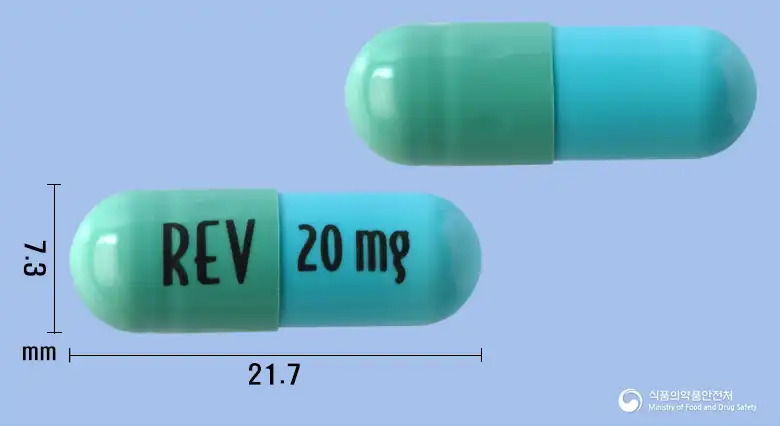
Lenalidomide Hydrate 20.7mg
Hard capsule · Prescription medication
Korean BMS Pharmaceutical Co., Ltd.
Lenalidomide Hydrate 7.76mg
Prescription medication
Celgene Corp.
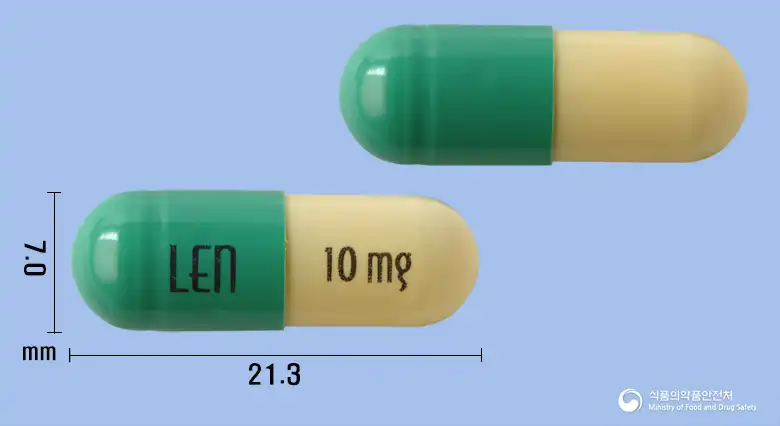
Lenalidomide Hemihydrate 10.35mg
Hard capsule · Prescription medication
Jongkundang Co., Ltd.
Even with the same ingredient, the dose and directions can differ by strength and dosage form. Talk to a doctor or pharmacist before switching from a medication you are already taking.
No questions yet.
For anything that needs medical judgment, consult a doctor or pharmacist.
This drug information is based on data provided by the Korea Ministry of Food and Drug Safety.
Consult a doctor or pharmacist for accurate dosage, administration, and usage instructions.