
 한국어
 English
 日本語
 中文(简体)
 Viewing now
Tarsin Capsule 1 mg (Tacrolimus Hydrate)
Tacrolimus Hydrate 1.02mg
Hard capsule · Prescription medication
Korea PMG Pharmaceutical Co., Ltd.
MFDS item code 201500518 · Approved 2015.01.30 · Insurance code 697100640
Prevention of transplant rejection and graft-versus-host disease; treatment of autoimmune diseases (e.g., rheumatoid arthritis)
This medication is used to inhibit rejection reactions that may occur after kidney and liver transplants. It also helps prevent graft rejection and graft-versus-host disease in patients who have received a bone marrow transplant. In cases of chronic rheumatoid arthritis where sufficient effects are not obtained with disease-modifying antirheumatic drugs (DMARDs), it is used. In lupus nephritis, when the response to steroid monotherapy is inadequate, it is used for a long time to help improve kidney symptoms. Finally, it is used in patients with myasthenia gravis when other immunosuppressants are ineffective or difficult to administer due to side effects, assisting in symptom relief. This drug is effectively used for the treatment and management of various immune-related disorders.
Suppression of rejection in kidney transplantation Usually, during the initial period, adults are administered tacrolimus orally at a dose of 0.10~0.15mg/kg twice daily, and the dose is gradually reduced thereafter. The maintenance dose should be adjusted as appropriate according to symptoms, with reference to the “recommended target trough blood concentration.” Suppression of rejection in liver transplantation Usually, during the initial period, adults are administered tacrolimus orally at a dose of 0.05~0.10mg/kg twice daily, and the dose is gradually reduced thereafter. The maintenance dose should be adjusted as appropriate according to symptoms, with reference to the “recommended target trough blood concentration.” General considerations for kidney and liver transplantation The initial doses given above are intended only as guidelines. Administration of this drug should be based primarily on clinical evaluation of rejection and tolerability in each patient, together with measurement of blood concentrations (see “Recommended target trough blood concentration” below). If clinical symptoms of rejection are evident, a change in the immunosuppressive treatment regimen should be considered. Recommended target trough blood concentration (whole blood trough level) in kidney and liver transplantation Several immunoassays, including semi-automated microparticle enzyme immunoassay (MEIA), are available for monitoring tacrolimus whole blood concentrations (whole blood level) to optimize the dose. Comparisons between blood concentrations reported in the literature and those measured in clinical practice should be made with a thorough understanding of the assay used. In current clinical practice, whole blood concentrations are monitored using immunoassays. Tacrolimus trough blood concentrations should be monitored continuously. When this drug is administered orally, the tacrolimus trough blood concentration should be measured immediately before the next dose (approximately 12 hours after the previous dose). The frequency of blood concentration measurements should be based on clinical need. Because tacrolimus has a low clearance, changes in blood concentrations may take several days to appear after a dose adjustment. During the initial period after transplantation, monitoring should be performed approximately twice a week, and regularly during the maintenance period. Trough blood concentrations should be monitored when adjusting the dose, changing immunosuppressive therapy, or concomitantly administering drugs that may affect tacrolimus whole blood concentrations (see “Interactions”). According to clinical trial analyses, successful outcomes were achieved in most patients when tacrolimus trough blood concentrations were maintained below 20ng/mL. The patient’s clinical condition should be taken into account when interpreting blood concentrations. Recommended target trough blood concentrations: In clinical practice, trough blood concentrations during the initial period after transplantation were 5~20ng/mL in liver transplant recipients and 10~20ng/mL in kidney transplant recipients. Thereafter, during the maintenance period, trough blood concentrations were 5-15ng/mL in liver and kidney transplant recipients. Bone marrow transplantation: Prevention of tissue graft rejection and graft-versus-host disease following bone marrow transplantation Usually, tacrolimus is administered orally at a dose of 0.06mg/kg twice daily, starting 1 day before transplantation. During the initial period after transplantation, tacrolimus is administered orally at a dose of 0.06mg/kg twice daily, and the dose is gradually reduced thereafter. In addition, if treatment with this drug is initiated after the onset of graft-versus-host disease, tacrolimus is usually administered orally at a dose of 0.15mg/kg twice daily. The dose should also be adjusted as appropriate according to symptoms. Chronic rheumatoid arthritis Adults are usually administered tacrolimus orally at a dose of 3mg once daily after the evening meal. Regular monitoring is required in patients who develop adverse reactions. Elderly patients are usually administered 1.5mg orally once daily after the evening meal; the dose may be increased to 3mg according to symptoms. Lupus nephritis Adults are usually administered tacrolimus orally at a dose of 3mg once daily after the evening meal. In clinical trials, when the effect was considered insufficient 12 weeks after treatment initiation and there were no safety concerns, 4 mg/day of this drug was administered for 4 weeks to confirm safety, after which the dose was increased to up to 5 mg/day. If adverse reactions occurred, the dose was appropriately reduced in increments of 0.5 mg or 1 mg, taking the patient’s condition into consideration. In addition, when a sufficient effect on lupus nephritis was achieved, this drug was reduced to the dose that maintained that effect. Myasthenia gravis Adults are administered tacrolimus orally at a dose of 3mg once daily after a meal.
Suppression of rejection in kidney transplantation: In children, administer 0.15mg/kg orally twice daily, followed by gradual dose reduction. Suppression of rejection in liver transplantation: In children, administer 0.15mg/kg orally twice daily, followed by gradual dose reduction.
As this drug suppresses the immune system, it may increase the risk of infections. Therefore, close monitoring for symptoms of infection is required when using this drug. Additionally, it can affect kidney function, so the health status of the kidneys should be checked frequently. If kidney function deteriorates, it may be necessary to adjust or discontinue the medication. This drug may cause hyperkalemia, so blood potassium levels should be tested regularly. Co-administration with potassium-sparing diuretics can be dangerous, therefore, avoidance of such combinations is advised. Furthermore, this drug may affect the nervous system, causing symptoms such as headaches, tremors, and seizures. In severe cases, coma or mental confusion may occur, so any abnormal symptoms should be reported to healthcare professionals immediately. Patients receiving this medication may have an increased risk of developing lymphoma or other malignant tumors, hence regular check-ups are necessary. Women who are pregnant or may become pregnant should consult their physician before using this medication, as it may affect the fetus. This drug can also be passed through breast milk, so it should be avoided during breastfeeding. Blood pressure and blood sugar should be monitored periodically during treatment, and actions should be taken if abnormalities occur. This drug has a high potential for drug interactions, so it is important to discuss any medications being taken with a doctor or pharmacist. Special care is needed when co-administering with cyclosporine, potassium-sparing diuretics, certain antifungal agents, and antibiotics. This medication should be taken strictly according to the instructions of a specialist, and medical supervision is required for any dose changes or discontinuation.
Increased susceptibility to infection, possibility of lymphoma development, nephrotoxicity, acute kidney injury, increased serum creatinine, hyperkalemia, decreased ureagenesis, hyperuricemia, chronic renal failure, tremors, headache, changes in motor function, changes in mental state, changes in sensory function, seizures, coma, delirium, posterior reversible encephalopathy syndrome (PRES), lymphoproliferative disorders, BK virus-associated nephropathy, JC virus-related PML, CMV infection, transplant rejection, insulin-dependent post-transplant diabetes, pure red cell aplasia (PRCA), myocardial impairment, heart failure, ventricular and supraventricular arrhythmias, myocardial infarction, angina, pericardial effusion, QT prolongation, Torsades de pointes, acute renal failure, nephrotic syndrome, thrombotic microangiopathy, pancytopenia, thrombocytopenic purpura, agranulocytosis, hemolytic anemia, bowel obstruction, bacterial infection, viral infection, fungal infection, protozoan infection, fever, lymphoma, central nervous system disorders, generalized seizures, altered consciousness, confusion, speech impairment, visual impairment, hemiplegia, cerebral infarction, cerebral hemorrhage, aspiration pneumonia, worsening diabetes, hyperglycemia, pancreatitis, Stevens-Johnson syndrome, dyspnea, acute respiratory distress syndrome, myasthenic crisis, renal impairment, decreased urine output, polyuria, frequency of urination, acidosis, hypercholesterolemia, hyperphosphatemia, hypophosphatemia, hypertriglyceridemia, hyperchloridemia, hypercalcemia, hypocalcemia, hyponatremia, hypokalemia, anemia, increased or decreased platelet count, leukopenia, leukocytosis, lymphocytopenia, pruritus, alopecia, erythema, rash, tubular necrosis, hypertrophic cardiomyopathy, gynecomastia, vasodilation, decreased serum phosphate concentration, pleural effusion, ascites, asthma, weight loss, flushing, general malaise, menorrhagia, myalgia, arthralgia, dysgeusia, aplastic anemia, cerebral infarction, toxic epidermal necrolysis, glaucoma, ketosis, nystagmus, mania, meningitis, cachexia, thrombophlebitis, thrombosis, vasculitis, sensation of foreign body in the throat, pain, eye pain, erythema, excessive sweating, thirst, temperature changes, optic neuropathy, febrile neutropenia, diarrhea, hypertension, nausea, constipation, anorexia, vomiting, melena, hematochezia, gastrointestinal perforation, elevated amylase, liver function abnormalities, jaundice, thrombocytopenia, fever, asthenia, back pain, ascites, limb edema, pleural effusion, atelectasis, increased cough, arthralgia, rash, pruritus, chest pain, abdominal distension, intestinal motility disorder, stomatitis, gastric ulcer, duodenal ulcer, colitis, cholangitis, cholestatic jaundice, gastrointestinal bleeding, hepatitis, increased appetite, liver damage, oral candidiasis, dysphagia, esophagitis, gastritis, bowel obstruction, abnormal liver function tests, rectal disorders, duodenitis, air in the gastrointestinal tract, gastroesophageal reflux, granulomatous hepatitis, ulcerative esophagitis, pancreatic pseudocyst, chest pain, abnormal ECG, hemorrhage, hypotension, tachycardia, angina, severe vasoactive vasculitis, orthostatic hypotension, peripheral vascular disorders, arrhythmias, atrial fibrillation, bradycardia, heart palpitations, cardiac arrest, cardiovascular disorders, congestive heart failure, deep venous thrombosis, abnormal echocardiogram, abnormal ECG QRS complex, abnormal ECG ST complex, cardiac dysfunction, increased heart rate, syncope, thrombosis, vasodilation, hematuria, renal failure, cystitis, dysuria, hydronephrosis, renal tubular necrosis, nocturia, pyuria, toxic nephropathy, acute kidney injury, proteinuria, BK nephropathy, bladder spasms, decreased urine output, urgency incontinence, frequency of urination, urinary incontinence, urinary retention, vaginitis, acidosis, increased alkaline phosphatase, alkalosis, bilirubinemia, non-healing, hyperlipidemia, hyperphosphatemia, hyperuricemia, hypocalcemia, hyponatremia, hypoproteinemia, increased AST, increased ALT, decreased bicarbonate, dehydration, hyperglycemia, hypoglycemia, increased lactate dehydrogenase, weight gain, increased BUN, edema, gout, hypercalcemia, hypercholesterolemia, hyperkalemia, hypophosphatemia, peripheral edema, diabetes mellitus, Cushing's syndrome, coagulopathy, purpura, hypochromic anemia, leukopenia, thrombocytopenia, erythrocytosis, decreased prothrombin, decreased plasma iron, increased hematocrit, abnormal hemoglobin, leukocytosis, generalized seizures, limb spasms, myalgia, myasthenia, osteoporosis, joint disorders, painful muscle cramps, decreased mobility, asthma, bronchitis, lung disease, pulmonary edema, pharyngitis, pneumonia, respiratory distress, rhinitis, sinusitis, voice changes, pneumothorax, hiccups, decreased lung function, alopecia, herpes simplex, hirsutism, skin disorders, sweating, acne, fungal dermatitis, skin discoloration, skin ulcer, exfoliative dermatitis, shingles, benign skin neoplasms, abdominal enlargement, abscess, chills, hernia, peritonitis, phototoxic reactions, allergic reactions, cellitis, influenza-like illness, sepsis, abdominal pain, incidental injury, back pain, soft tissue infection, falls, sensory disturbances, temperature intolerance, ulcers, heartburn, epigastric discomfort, retinopathy, cardiac arrest, lumbago, hoarseness, cold, shingles, warts, autoimmune response, soft tissue infection, pneumonia
Not everyone experiences these, and they can vary from person to person.
This drug may be sensitive to air and moisture, so it should be stored in a tightly sealed container. It is advisable to maintain the storage temperature between 1 to 30 degrees Celsius at room temperature. This helps in preserving the efficacy of the drug for a longer period.
A hard capsule of white color containing white powder
100 capsules (10 capsules/PTP × 10)
Even with the same ingredient, strength, dosage form and how it is taken can differ.
Viewing nowTacrolimus Hydrate 1.02mg
Hard capsule · Prescription medication
Korea PMG Pharmaceutical Co., Ltd.
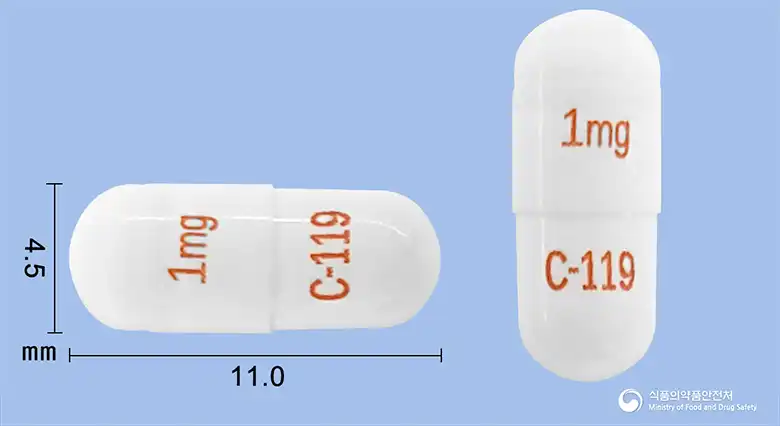
Tacrolimus Hydrate 1.02mg
Hard capsule · Prescription medication
Chongkundang Corporation
 Combination
Tacrolimus Hydrate 0.51mg · Tacrolimus Hydrate 0.51mg
Hard capsule · Prescription medication · Combination
Chongkundang Corporation
Tacrolimus Hydrate 0.255mg
Hard capsule · Prescription medication
Chongkundang Corporation

Tacrolimus Hydrate 1.02mg
Hard capsule · Prescription medication
Ilyun Pharmaceutical Co., Ltd.

Tacrolimus Hydrate 1.02mg
Hard capsule · Prescription medication
Hanmi Pharmaceutical Co., Ltd.
Tacrolimus Hydrate 5.1mg
Prescription medication
Korea Astellas Pharma Co., Ltd.
Tacrolimus Hydrate 0.51mg
Hard capsule · Prescription medication
Korea Astellas Pharma Co., Ltd.
Even with the same ingredient, the dose and directions can differ by strength and dosage form. Talk to a doctor or pharmacist before switching from a medication you are already taking.
No questions yet.
For anything that needs medical judgment, consult a doctor or pharmacist.
This drug information is based on data provided by the Korea Ministry of Food and Drug Safety.
Consult a doctor or pharmacist for accurate dosage, administration, and usage instructions.