
 한국어
 English
 日本語
 中文(简体)
 Viewing now
Rapamune 2 mg (Sirolimus)
Sirolimus Dispersion Solution 13.3mg
Prescription medication
Pfizer Korea Co., Ltd.
MFDS item code 200906599 · Approved 2009.08.31 · Insurance code 648902330
Prevention of kidney transplant rejection; treatment of lymphangioleiomyomatosis
This medication is used to prevent organ rejection in kidney transplant patients aged 13 and older. Initially, it is administered in combination with other medications for patients with low to moderate immunological risk, and some medications are discontinued after a few months. Combination therapy is also recommended for patients with high immunological risk. Additionally, this drug is used to treat a rare disease known as lymphangioleiomyomatosis. However, its use may be restricted in certain patient populations, so consultation with a physician is important. This drug is effectively used for the modulation of immune responses in kidney transplant patients and the treatment of lymphangioleiomyomatosis.
This medication is administered orally once daily. To minimize variability in exposure to this medication, it should be administered consistently either with food or on an empty stomach. Do not crush, chew, or split this medication. 1. General dosage in kidney transplant patients The initial dose of this medication should be administered as soon as possible after transplantation. It is recommended that this medication be administered 4 hours after administration of cyclosporine oral solution and/or cyclosporine capsules. Therapeutic drug monitoring is recommended for all patients receiving this medication. Because this medication has a long half-life, frequent dose adjustments based on concentrations measured during the non-steady state may result in overdosage or underdosage. Once the maintenance dose of this medication has been adjusted, maintain that dose for at least 7~14 days before readjusting the dose based on blood concentration monitoring. The following equation may be used to adjust the dose in most patients: New dose of this medication = Current dose X (Target blood concentration / Current blood concentration) If a substantial increase in the trough blood concentration of this medication is desired, a loading dose should also be considered in addition to the new maintenance dose: Loading dose of this medication = 3 X (New maintenance dose - Current maintenance dose) The maximum daily dose of this medication should not exceed 40mg. If administration of a loading dose would cause the planned daily dose to exceed 40mg, the loading dose should be administered over 2 days. The trough concentration of this medication should be monitored at least 3-4 days after administration of the loading dose. Clinical trial results in patients at low or moderate immunologic risk demonstrated that taking 2mg of this medication is clinically equivalent to taking 2mg of sirolimus oral solution; therefore, the oral solution and tablets may be substituted for one another. However, it is not known whether the oral solution and tablets are clinically equivalent when doses greater than 2mg are administered. 2. Kidney transplant patients at low or moderate immunologic risk Combination therapy with this medication and cyclosporine: Initially, it is recommended that this medication be administered in combination with cyclosporine and corticosteroids. New kidney transplant recipients should receive a loading dose that is 3 times the maintenance dose. For kidney transplant patients, an initial loading dose of 6mg/day and a maintenance dose of 2mg/day are recommended. Maintain sirolimus concentrations within the target range through therapeutic drug monitoring. Administration of this medication after cyclosporine withdrawal: Patients undergoing cyclosporine withdrawal for the first time should be receiving this medication in combination with cyclosporine. Cyclosporine withdrawal is recommended 2~4 months after transplantation. At 2-4 months after transplantation, cyclosporine should be gradually discontinued over 4-8 weeks, and the dose of this medication should be adjusted so that its trough blood concentration is within 16-24ng/mL (chromatographic method) during the first year after transplantation. Thereafter, the target blood concentration of this medication should be 12-20 ng/mL (chromatographic method). Cyclosporine inhibits the metabolism and transport of this medication; therefore, its concentration will decrease unless the dose of this medication is increased when cyclosporine is discontinued. In the absence of cyclosporine, the dose of this medication needs to be increased approximately 4-fold because there is no pharmacokinetic interaction (requiring an approximately 2-fold dose increase) and the need for immunosuppression increases (requiring an approximately 2-fold dose increase). 3. Kidney transplant patients at high immunologic risk For patients at high immunologic risk, combination therapy with cyclosporine and corticosteroids is recommended for 12 months after transplantation. The safety and efficacy of administering this combination therapy for more than 1 year in patients at high immunologic risk have not been studied. Therefore, based on the patient's clinical condition, a change in immunosuppressive therapy after the first 12 months following transplantation should be considered. Patients receiving this medication in combination with cyclosporine should receive a 15mg loading dose on the day of transplantation. Starting on day 2, a 5mg maintenance dose should be administered. Measure the trough concentration on days 5-7 of treatment and adjust subsequent doses of this medication so that its trough blood concentration is within 10-15ng/mL (chromatographic method). The initial dose of cyclosporine should be 7mg/kg/day in divided doses, and the dose should continue to be adjusted until the target whole-blood trough concentration is reached. The target whole-blood trough concentration is 200-300ng/mL through day 14, 150-200ng/mL from day 15 through week 26, and 100-150ng/mL from week 27 through week 52. Prednisolone should be administered at a dose of at least 5mg/day. Antibody induction therapy may be used. 4. Dosage in patients with lymphangioleiomyomatosis The initial dose of this medication in patients with lymphangioleiomyomatosis is 2 mg once daily. The whole-blood trough concentration of this medication should be measured on days 10-20, and the dose should be adjusted to maintain the concentration within 5-15 ng/mL. The following equation may be used to adjust the dose in most patients: New dose of this medication=Current doseX(Target blood concentration/Current blood concentration). Because this medication has a long half-life, frequent dose adjustments based on concentrations measured during the non-steady state may result in overdosage or underdosage. Once the maintenance dose of this medication has been adjusted, maintain that dose for at least 7-14 days before readjusting the dose based on blood concentration monitoring. Once a stable dose has been established, therapeutic drug monitoring should be performed at least once every 3 months. 5. Dose adjustment In patients with hepatic impairment, a maintenance dose of approximately 2/3 of the dose used in patients with normal hepatic function is recommended for patients with mild to moderate hepatic impairment. For patients with severe hepatic impairment, a maintenance dose of approximately 1/2 of the dose used in patients with normal hepatic function is recommended. No change to the loading dose is necessary. No dose adjustment is required in patients with renal impairment. 6. Therapeutic drug monitoring (see Precautions for Use, 4. General Precautions, 12) “Differences in the trough concentrations of this medication reported by chromatographic and immunoassay methods”) Dose adjustment of this medication should not be based solely on therapeutic drug monitoring. Clinical symptoms/signs, biopsy findings, and laboratory parameters should also be taken into account. The whole-blood trough concentration of this medication should be monitored in patients undergoing blood concentration-guided therapy with this medication. Monitoring is particularly necessary in patients who may have altered drug metabolism, patients with hepatic impairment, patients receiving concomitant potent CYP3A4 and/or P-glycoprotein (P-gp) inducers and inhibitors, and/or when the cyclosporine dose changes substantially or cyclosporine is discontinued.
For patients 13 years and older who weigh less than 40kg, adjust the initial loading dose to 3mg/m2/day and the maintenance dose to up to 1mg/m2/day based on body surface area. Among patients receiving therapeutic drug monitoring with this medicine, monitor the whole-blood trough concentration of this medicine in patients 13 years and older who weigh less than 40kg.
This medication suppresses the immune system, which may increase the risk of infections. Special caution is needed as there is a possibility of developing malignancies such as lymphoma. Its safety and efficacy have not been established in patients receiving liver or lung transplants, and it is not recommended for them. For patients starting this medication after liver transplantation, combining it with other immunosuppressants may increase mortality and the risk of transplant failure. During treatment, patients should be vigilant for symptoms of infection and should consult healthcare professionals immediately if infection is suspected. Caution is needed when co-administering with certain medications to monitor blood concentration, and it is not recommended to take it with some antifungals or antibiotics. It should not be used by individuals with lactose intolerance or allergies to this medication's components. Regular blood tests and liver function tests are required during treatment, and adverse reactions such as hyperlipidemia, hyperglycemia, and renal function decline may occur. This medication may delay wound healing, so special caution is necessary post-surgery. Women who are pregnant or planning to become pregnant must consult a physician before using this medication and should use effective contraception. If breastfeeding, it is recommended to cease breastfeeding or stop the medication as it may be excreted in breast milk. In case of overdose, there is no specific antidote, so immediate treatment at a medical facility is required. This medication must be taken under a physician's prescription and guidance, and regular monitoring and management by healthcare professionals are necessary.
Increased susceptibility to infections, lymphoma, malignant tumors, skin lymphomas, opportunistic infections, sepsis, fatal infections, hepatic artery thrombosis, bronchial anastomosis dehiscence, thrombocytopenia, anemia, leukopenia, hemolytic uremic syndrome, neutropenia, pancytopenia, thrombotic thrombocytopenic purpura, tachycardia, pericardial effusion, abdominal pain, constipation, diarrhea, nausea, pancreatitis, stomatitis, ascites, impaired healing, edema, peripheral edema, fever, pain, hypersensitivity, angioedema, anaphylactic reactions, anaphylactoid reactions, pneumonia, fungal infections, viral infections, bacterial infections, herpes simplex, urinary tract infections, pyelonephritis, cytomegalovirus infection, shingles, mycobacterial infections, Epstein-Barr virus infection, abnormal liver function tests, increased serum creatinine, increased serum lactate dehydrogenase, hypokalemia, hypophosphatemia, hyperlipidemia, hypercholesterolemia, hyperglycemia, hypertriglyceridemia, fluid retention, diabetes, arthralgia, osteonecrosis, squamous cell carcinoma, basal cell carcinoma, malignant melanoma, post-transplant lymphoproliferative disorder, neuroendocrine carcinoma, headaches, reversible posterior leukoencephalopathy syndrome, proteinuria, nephrotic syndrome, focal segmental glomerulosclerosis, menstrual disorders, ovarian cysts, pulmonary embolism, interstitial pneumonia, pleural effusion, nosebleeds, pulmonary hemorrhage, alveolar proteinosis, rashes, acne, exfoliative dermatitis, hypersensitivity vasculitis, hypertension, venous thrombosis, lymphedema, weakness, abdominal distension, chills, cold symptoms, hernias, fatigue, atrial fibrillation, congestive heart failure, bleeding, hypervolemia, hypotension, palpitations, peripheral vascular disorders, orthostatic hypotension, syncope, vasodilation, dyspepsia, vomiting, appetite loss, dysphagia, belching, esophagitis, gastric distension, gingival hyperplasia, intestinal obstruction, oral moniliasis, Cushing's syndrome, petechiae, leukocytosis, lymphadenopathy, erythrocytosis, hyperkalemia, weight gain, acidosis, increased BUN, increased creatine phosphokinase, dehydration, hypercalcemia, hypocalcemia, hyperphosphatemia, hypoglycemia, hypomagnesemia, hyponatremia, weight loss, arthropathy, leg cramps, myalgia, osteoporosis, stiffness, tremors, anxiety, confusion, depression, dizziness, emotional instability, muscular hypertonicity, sensory decreases, muscle hypotonia, insomnia, neuropathy, sensory abnormalities, drowsiness, dyspnea, asthma, atelectasis, increased cough, hypoxia, pulmonary edema, fungal dermatitis, hirsutism, pruritus, skin thickening, skin ulcers, sweating, abnormal vision, cataracts, hearing loss, tinnitus, dysuria, hematuria, hydronephrosis, erectile dysfunction, renal colic, tubular necrosis, nocturia, oliguria, pyuria, testicular disorders, toxic nephropathy, frequent urination, urinary incontinence, urinary retention, polyuria, local reactions to surgery, stomatitis, nasopharyngitis, chest pain, upper respiratory infections, dizziness, muscle pain, hypercholesterolemia, increased creatinine, shingles, pneumonia, urinary tract infections, hyperglycemia, upper respiratory infections, nasopharyngitis, gastritis, nitrogenemia, transplant rejection, fractures, agranulocytosis, abscesses, cholangitis, cystitis, vesicoureteral reflux, ascites, hyperplasia of the parathyroid glands, contact dermatitis, polyomavirus infection, dyspnea, increased plasma osmolality, worsening angina, cholangitis, renal artery occlusion, cavities
Not everyone experiences these, and they can vary from person to person.
This medication should be stored in a sealed container to prevent exposure to air or light. It should be kept away from direct sunlight and stored at room temperature between 20 and 25 degrees.
Triangular yellow to light yellow tablet
100 tablets (10 tablets/blister x 10)
Even with the same ingredient, strength, dosage form and how it is taken can differ.
Viewing nowSirolimus Dispersion Solution 13.3mg
Prescription medication
Pfizer Korea Co., Ltd.
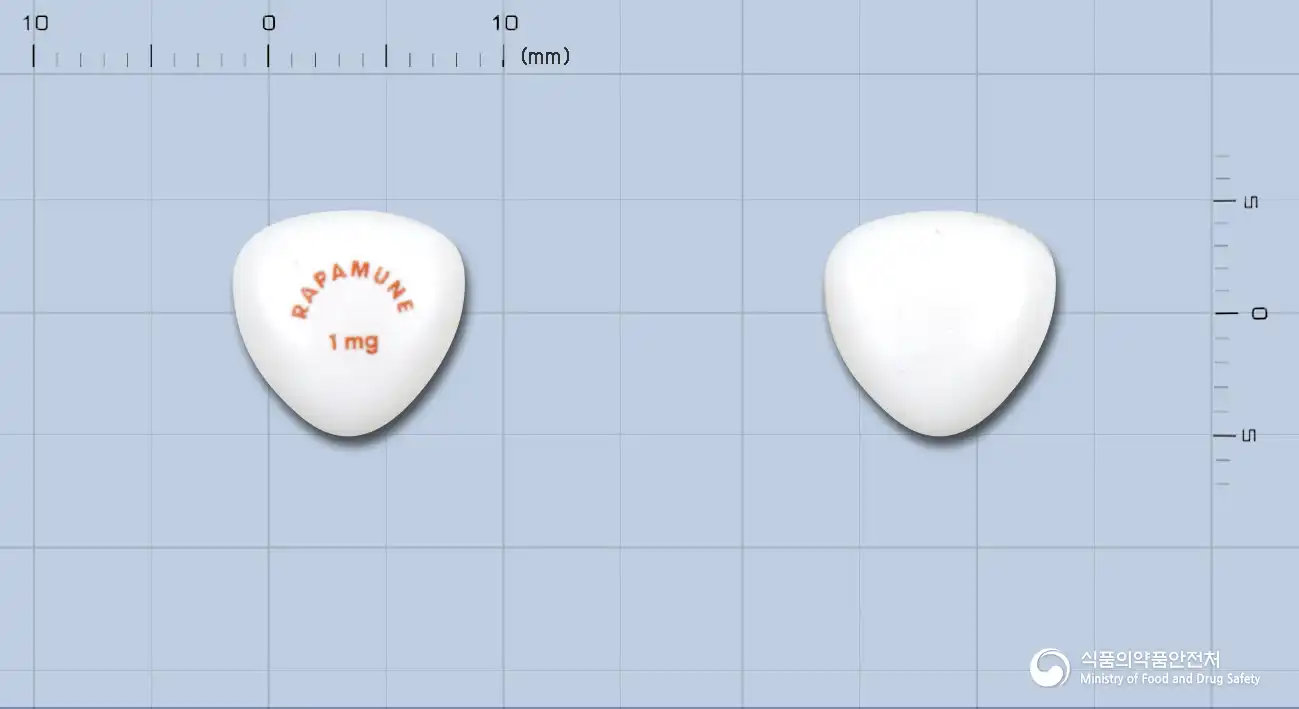
Sirolimus Dispersion Solution 6.6mg
Prescription medication
Pfizer Korea Co., Ltd.
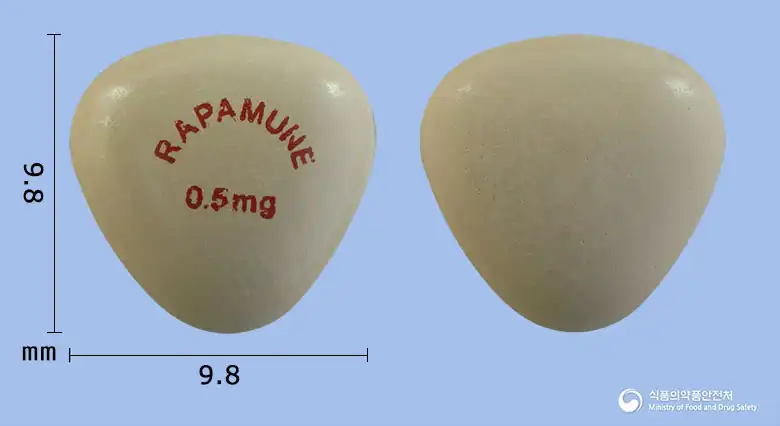
Sirolimus Dispersion Solution 3.3mg
Prescription medication
Pfizer Pharmaceuticals Korea Co., Ltd.
Even with the same ingredient, the dose and directions can differ by strength and dosage form. Talk to a doctor or pharmacist before switching from a medication you are already taking.
No questions yet.
For anything that needs medical judgment, consult a doctor or pharmacist.
This drug information is based on data provided by the Korea Ministry of Food and Drug Safety.
Consult a doctor or pharmacist for accurate dosage, administration, and usage instructions.