
 한국어
 English
 日本語
 中文(简体)
 Viewing now
Lamiat Tablets 100 mg (Lamotrigine)
Lamotrigine 100mg
Tablet · Prescription medication
Daewoong Pharmaceutical Co., Ltd.
MFDS item code 200706331 · Notified 2007.06.01 · Insurance code 641600450
Treatment of epilepsy (including partial seizures, etc.) and prevention of recurrence of depressive episodes in bipolar I disorder
This medication is used alone or as adjunctive therapy for epilepsy, particularly focal seizures and generalized tonic-clonic seizures. It also provides support as adjunctive therapy for seizures due to Lennox-Gastaut syndrome. Furthermore, it is used to prevent the recurrence of depressive mood in patients with bipolar I disorder. Therefore, this medication regulates various forms of seizures and contributes to mental health stability.
This medication may be swallowed whole, chewed, or taken after dispersing the tablet in a small amount of water (for chewable tablets only). Epilepsy, adults and adolescents aged 13 years and older: Monotherapy: Weeks 1 and 2, 25 mg (once daily); weeks 3 and 4, 50 mg (once daily); maintenance dose, 100∼200 mg (once daily or in 2 divided doses). Increase the dose by up to 50∼100 mg every 1∼2 weeks until the maintenance dose is reached. In some patients, doses of up to 500 mg/day have been used to achieve the desired response. Epilepsy, adults and adolescents aged 13 years and older: Adjunctive therapy in patients not receiving valproate and receiving glucuronidation-inducing agents: Weeks 1 and 2, 50 mg (once daily); weeks 3 and 4, 100 mg (in 2 divided doses); maintenance dose, 200∼400 mg (in 2 divided doses). Increase the dose by up to 100 mg every 1~2 weeks until the maintenance dose is reached. Epilepsy, adults and adolescents aged 13 years and older: Adjunctive therapy in patients receiving valproate, regardless of other concomitant medications: Weeks 1 and 2, 12.5 mg (25 mg every other day); weeks 3 and 4, 25 mg (once daily); maintenance dose, 100∼200 mg (once daily or in 2 divided doses). Increase the dose by up to 25~50 mg every 1~2 weeks until the maintenance dose is reached. In patients receiving medications for which pharmacokinetic interactions with lamotrigine are not known, dose increases should follow the recommended dosage and rate of dose escalation for concomitant administration of this medication with valproate. Bipolar disorder, adults aged 18 years and older: Patients receiving valproate: Weeks 1 and 2, 12.5 mg (25 mg every other day); weeks 3 and 4, 25 mg (once daily); week 5, 50 mg (once daily or in 2 divided doses); target stabilization dose (week 6), 100 mg (once daily or in 2 divided doses) (maximum daily dose: 200 mg). Bipolar disorder, adults aged 18 years and older: Patients not receiving inhibitors such as valproate and receiving glucuronidation-inducing agents: Weeks 1 and 2, 50 mg (once daily); weeks 3 and 4, 100 mg (in 2 divided doses); week 5, 200 mg (in 2 divided doses); 300 mg in week 6, with an increase to 400 mg in week 7 if necessary (in 2 divided doses). Bipolar disorder, adults aged 18 years and older: Patients receiving other medications that do not significantly inhibit or induce lamotrigine glucuronidation, or receiving lamotrigine as monotherapy: Weeks 1 and 2, 25 mg (once daily); weeks 3 and 4, 50 mg (once daily or in 2 divided doses); week 5, 100 mg (once daily or in 2 divided doses); target stabilization dose (week 6), 200 mg (once daily or in 2 divided doses). Patients receiving glucuronidation inhibitors (e.g., valproate): Administer 25 mg every other day for the first 2 weeks, then 25 mg once daily for the next 2 weeks. The target dose is 100 mg once daily or in 2 divided doses. Depending on clinical response, the dose may be increased to a maximum of 200 mg, administered once daily (or in 2 divided doses). Patients not receiving inhibitors such as valproate and receiving glucuronidation-inducing agents: Administer 50 mg once daily for the first 2 weeks, then 100 mg in 2 divided doses for the next 2 weeks. In week 5, administer 200 mg in 2 divided doses. In week 6, administer 300 mg in 2 divided doses. From week 7, 400 mg may be administered in 2 divided doses. Patients receiving other medications that do not significantly inhibit or induce glucuronidation, or receiving this medication as monotherapy: Administer 25 mg once daily for the first 2 weeks, then 50 mg once daily (or in 2 divided doses) for the next 2 weeks. In week 5, administer 100 mg once daily (or in 2 divided doses). The target dose is 200 mg once daily or in 2 divided doses. In clinical trials, doses of up to 400 mg/day were used as monotherapy; however, lamotrigine 400 mg/day provided no benefit over 200 mg/day. After discontinuation of valproate: In week 1, administer twice the stabilization dose. However, the dose increase should not exceed 100 mg/week. For example, if the target stabilization dose is 100 mg/day, administer 200 mg/day in week 1. In week 2, maintain the week 1 dose (200 mg/day) (once daily or in 2 divided doses). After discontinuation of glucuronidation-inducing agents: Select the dose according to the previous maintenance dose. Previous maintenance dose of 400 mg: 300 mg in week 1, 200 mg in week 2; 300 mg: 225 mg in week 1, 150 mg in week 2; 200 mg: 150 mg in week 1, 100 mg in week 2. After discontinuation of medications that do not significantly inhibit or induce glucuronidation: Maintain the target maintenance dose reached through dose escalation (200 mg/day) (in 2 divided doses). When adding glucuronidation inhibitors: Previous dose of 200 mg: 100 mg* in week 1, maintain this dose thereafter (100 mg/day)*; previous dose of 300 mg: 150 mg* in week 1, maintain this dose thereafter (150 mg/day)*; previous dose of 400 mg: 200 mg* in week 1, maintain this dose thereafter (200 mg/day)*. When adding glucuronidation-inducing agents in patients not receiving valproate: Previous dose of 200 mg: 200 mg** in week 1, 300 mg** in week 2, 400 mg** from week 3 onward; previous dose of 150 mg: 150 mg** in week 1, 225 mg** in week 2, 300 mg** from week 3 onward; previous dose of 100 mg: 100 mg** in week 1, 150 mg** in week 2, 200 mg** from week 3 onward. Adjunctive therapy with medications that do not significantly inhibit or induce glucuronidation: Target maintenance dose reached through dose escalation (200 mg/day)*. * : Administer once daily or in 2 divided doses, ** : Administer in 2 divided doses. Abrupt discontinuation of this medication should be avoided whenever possible. Unless immediate discontinuation is required for safety reasons, the dose of this medication should be gradually reduced over at least 2 weeks. When restarting this medication, assess the need to gradually increase the dose to the maintenance dose. In general, if the period since discontinuation of this medication exceeds 5 half-lives, the dose should be gradually increased to the maintenance dose according to an appropriate regimen. The recommended dosage schedules for adults and adolescents aged 13 years and older may also be used in elderly patients (aged 65 years and older). Start elderly patients at a low dose. In patients with moderate (Child-Pugh grade B) and severe (Child-Pugh grade C) hepatic impairment, the initial dose, dose increments, and maintenance dose should be reduced by approximately 50% and 75%, respectively. Dose increments and maintenance doses should be adjusted according to clinical response. In patients with end-stage renal impairment, the initial dose of this medication should be based on the patient's antiepileptic drug regimen. A reduced maintenance dose may be effective in patients with severe renal impairment.
Children aged 2∼12 years, epilepsy monotherapy: Adequate clinical data to support a basic recommended dose for administration of this drug as monotherapy in children aged 12 years or younger are not yet available. Children aged 2∼12 years, adjunctive therapy, patients not receiving valproate and receiving glucuronidation-inducing drugs: Weeks 1 and 2: 0.6 mg/kg/day (in 2 divided doses); weeks 3 and 4: 1.2 mg/kg/day (in 2 divided doses); maintenance dose: 5∼15 mg/kg/day (in 2 divided doses). Increase by a maximum of 1.2 mg/kg/day every 1~2 weeks until the maintenance dose is reached; maximum 400 mg/day. Children aged 2∼12 years, adjunctive therapy, patients receiving valproate regardless of other concomitant medications: Weeks 1 and 2: 0.15 mg/kg/day** (once daily); weeks 3 and 4: 0.3 mg/kg/day (once daily); maintenance dose: 1∼5 mg/kg/day (once daily or in 2 divided doses). Increase by a maximum of 0.3 mg/kg/day every 1~2 weeks until the maintenance dose is reached. Maximum 200 mg/day. ** If the calculated daily dose is 1∼2 mg, 2 mg may be administered every other day during the first 2 weeks. If the calculated daily dose is less than 1 mg, this drug should not be administered. For patients aged 2 years or older and younger than 6 years, the upper end of the recommended dose range may be the maintenance dose. Children younger than 2 years: The safety and efficacy of this drug have not been established in children aged 1 month to younger than 2 years. There are no data for neonates younger than 1 month. Use is not recommended in patients younger than 2 years, and use of this drug is particularly not recommended in patients younger than 2 years who are taking valproate. Children and adolescents younger than 18 years: Do not administer to patients with bipolar disorder.
This medication may cause serious skin rashes, which can be life-threatening, particularly in children. If a rash develops, treatment should be discontinued immediately. Rashes commonly occur within the first 8 weeks of initiating this medication and may rarely progress to more severe skin conditions such as Stevens-Johnson syndrome or toxic epidermal necrolysis. In the early stages, the rash may be mistaken for an infection, so if a rash occurs with fever, the possibility of a drug reaction must be considered. Caution is advised as administering higher than recommended doses or using this medication in combination with certain other medications may increase the risk of skin rashes. Patients with a history of rash due to this medication should not be re-treated. Rashes may accompany symptoms such as fever, lymphadenopathy, facial swelling, blood abnormalities, liver function abnormalities, and aseptic meningitis; if any of these symptoms arise, immediate consultation with healthcare professionals is necessary. If aseptic meningitis occurs, this medication should not be used again, and if photosensitivity reactions occur, exposure to sunlight and UV light should be avoided and protective measures should be taken. This medication can cause serious systemic inflammatory syndrome that may lead to abnormalities in immune cells in the blood; therefore, if symptoms like fever, rash, or organ enlargement occur, immediate evaluation is required. Seizures may worsen, and severe seizures may occur, so any changes in seizure symptoms should be discussed with healthcare professionals. Patients taking other lamotrigine-containing medications should not add this medication without consulting a physician. While taking this medication, suicidal thoughts or behavior, and depressive symptoms may occur, so patients and caregivers should report any such changes to healthcare professionals immediately. Particularly in patients with bipolar disorder, symptom worsening or suicidal risk should be closely monitored at the beginning of treatment or when doses are changed. Women taking hormonal contraceptives may need dosage adjustments due to potential interactions affecting drug concentration, and non-hormonal contraceptive methods should be considered due to the possibility of reduced contraceptive efficacy. Patients with hypersensitivity to this medication, those who have previously discontinued use due to aseptic meningitis, and those with genetic issues such as lactose intolerance should not take this medication. Patients with renal or liver dysfunction, pregnant women, nursing mothers, and individuals with heart conduction abnormalities should use this medication with caution. Various side effects such as headaches, dizziness, drowsiness, nausea, vomiting, rashes, etc., may occur during treatment; severe symptoms should be discussed with healthcare professionals. This medication should not be discontinued abruptly as seizures may worsen; any discontinuation should be done gradually under the supervision of a physician. During pregnancy, this medication should only be used when necessary, and women planning to become pregnant are advised to take folic acid supplements. While breastfeeding, this medication can be transmitted through breast milk and potentially affect the newborn, hence stopping breastfeeding during treatment is recommended. In children under 2 years of age, safety and efficacy have not been established, making it not recommended. In case of overdose, symptoms such as consciousness disturbances, seizures, or coma may occur, and patients require supportive treatment in a hospital since there is no specific antidote. This medication should be stored in a dry place at temperatures below 30 degrees Celsius, kept out of reach of children, and preferably stored in its original container.
Rash, skin rash, photosensitivity reaction, skin mucosal syndrome (Stevens-Johnson syndrome), toxic epidermal necrolysis (Lyell's syndrome), alopecia, hematological abnormalities (including neutropenia, leukopenia, anemia, thrombocytopenia, pancytopenia, aplastic anemia, agranulocytosis), lymphadenopathy, hemophagocytic lymphohistiocytosis, hypersensitivity reactions (including fever, lymphadenopathy, facial swelling, blood abnormalities, liver abnormalities, disseminated intravascular coagulation, multiple organ failure), aseptic meningitis, aggressiveness, hypersensitivity, tics, hallucinations, confusion, nightmares, headache, drowsiness, insomnia, dizziness, ataxia, eye twitching, agitation, instability, movement disorders, exacerbation of Parkinson's disease, extrapyramidal effects, chorea-like twisting movements, increased seizure frequency, diplopia, blurred vision, conjunctivitis, nausea, vomiting, diarrhea, loss of appetite, gastrointestinal disturbances, gastrointestinal disturbances, elevated liver function tests, liver dysfunction, liver failure, lupus-like reactions, fatigue, pain, pharyngitis, flu syndrome, insomnia, menstrual disorders, tremors, pulmonary disorders, depression, amnesia, abnormal thoughts, abdominal pain, indigestion, constipation, bloating, weight gain, edema, arthralgia, myalgia, frequent urination, sweating, mania, hypomania, mixed episode, reduced bone density, osteopenia, osteoporosis, fractures, DRESS syndrome, eye twitching, ataxia, coma, altered consciousness, increased seizures, grand mal seizures, QRS prolongation, loss of consciousness
Not everyone experiences these, and they can vary from person to person.
This medication should be stored in a tightly sealed container to prevent exposure to air or moisture. It should be kept at an appropriate room temperature, in a dry place, away from extreme heat or cold.
Pale yellow-brown square tablet
30 tablets/bottle
Even with the same ingredient, strength, dosage form and how it is taken can differ.
Viewing nowLamotrigine 100mg
Tablet · Prescription medication
Daewoong Pharmaceutical Co., Ltd.

Lamotrigine 100mg
Tablet · Prescription medication
GlaxoSmithKline Co., Ltd.

Lamotrigine 100mg
Tablet · Prescription medication
Yian Pharmaceutical Co., Ltd.

Lamotrigine 100mg
Tablet · Prescription medication
Hanlim Pharmaceutical Co., Ltd.
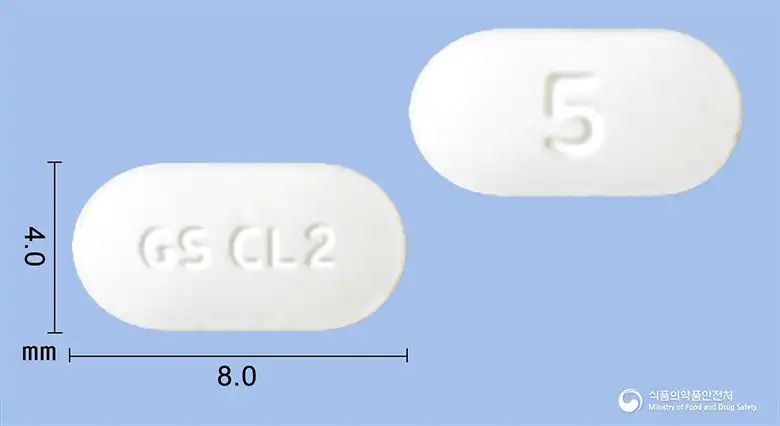
Lamotrigine 5mg
Chewable Tablet · Prescription medication
GlaxoSmithKline Co., Ltd.

Lamotrigine 2mg
Chewable Tablet · Prescription medication
GlaxoSmithKline Co., Ltd.
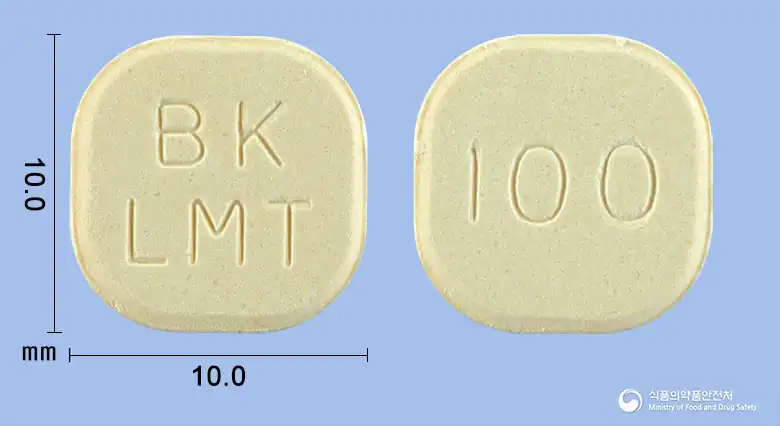
Lamotrigine 100mg
Tablet · Prescription medication
Bukwang Pharmaceutical Co., Ltd.

Lamotrigine 50mg
Tablet · Prescription medication
Hallym Pharmaceutical Co., Ltd.
Even with the same ingredient, the dose and directions can differ by strength and dosage form. Talk to a doctor or pharmacist before switching from a medication you are already taking.
No questions yet.
For anything that needs medical judgment, consult a doctor or pharmacist.
This drug information is based on data provided by the Korea Ministry of Food and Drug Safety.
Consult a doctor or pharmacist for accurate dosage, administration, and usage instructions.