
 한국어
 English
 日本語
 中文(简体)
Dosage form image
Viewing nowJournistar Sustained Release Tablet 8mg (Hydromorphone Hydrochloride)
Hydromorphone Hydrochloride
Prescription medication
Korea Janssen Co., Ltd.
MFDS item code 200703756 · Approved 2007.04.02
This product's status changed to Expired on 2023.07.01. It may no longer be sold, so consult a doctor or pharmacist before taking it.
Relief of severe pain requiring opioid analgesics
This medication is an opioid analgesic used to relieve severe pain. It reduces patient discomfort through strong pain control effects and is particularly effective for managing post-surgical pain or pain caused by cancer. For safe use, it is important to follow a doctor's prescription and guidance. This medication alleviates pain quickly and helps improve the patient's quality of life. Therefore, it is used as a suitable therapeutic agent for managing severe pain.
As with other opioid analgesics, adequate assessment of the patient is important to ensure the safe and effective administration of this drug for the treatment of pain. The patient’s current medical condition, as well as the nature of the pain, affects dose selection. Because individual patients may respond differently to opioid medications, it is recommended that treatment be started at a conservative dose in all patients and the dose adjusted to an appropriate level based on adverse reactions and analgesic effect. The drug should be administered at the lowest effective dose for the shortest possible duration. Instruct patients to take this drug once daily at approximately the same time, swallowing the tablet whole with a glass of water without chewing, cutting, or crushing it. As with other potent opioid medications, appropriate preventive treatment should be considered for known adverse reactions (e.g., constipation). This drug must not be administered more than once every 24 hours. If a patient misses a scheduled dose, they should take the next dose immediately and begin a new 24-hour dosing cycle. 1. Adult patients (18 years or older) currently receiving opioid analgesics on a regular basis It is recommended that this drug be administered once daily in the morning. For patients currently receiving opioid analgesics on a regular basis, the starting dose of this drug is based on the previous daily opioid dose, using standard equianalgesic ratios. For opioids other than morphine, first calculate the total daily dose converted to morphine, and then use the table below to calculate the total daily dose of this drug. Conversion table: Multiplication factors for converting the daily dose of an existing opioid medication to the daily dose of this drug (daily mg of existing opioid medication x factor = daily mg of this drug) Existing opioid medication Oral existing opioid medication (factor) Parenteral existing opioid medication (factor) Morphine 0.2 0.6 Hydromorphone 1 4 Because of individual patient and formulation differences, no definitive conversion ratio is satisfactory for all patients. Therefore, close patient monitoring and dose adjustment are recommended after starting treatment at the recommended starting dose of this drug. As clinically necessary, round the dose down to the nearest dose that is a multiple of 8 mg of this drug. Other opioid analgesics with a duration of action of 24 hours should be discontinued when treatment with this drug is initiated. This drug may be used with usual doses of non-opioid analgesics. 2. Supplemental analgesia In addition to once-daily treatment with this drug, supplemental analgesia in the form of an immediate-release product (e.g., immediate-release hydromorphone) may be made available to all patients with chronic pain for control of breakthrough pain. Use the conversion table when converting. For an individual patient, the dose of immediate-release hydromorphone as a supplemental medication should generally not exceed 10 % to 25 % of the 24-hour dose of this drug (see table below). Recommended starting doses for supplemental analgesics Daily dose (mg) Strength of immediate-release hydromorphone tablets (mg) 4 - 8 2 16 2 32 4 64 8 3. Individualization of dosage and maintenance of treatment After starting treatment with this drug, dose adjustment may be necessary to achieve the optimal balance between pain relief and opioid-related adverse reactions in the patient. If pain increases or analgesia is inadequate, gradual dose increases may be necessary. Increase the dose every 4 doses and do not do so more frequently. For example, if the first dose is taken on Monday, the dose may be increased after the fourth dose on Thursday. At each dose adjustment, consider increasing the current daily dose of this drug by 25∼100 %. Once a patient has stabilized on once-daily treatment with this drug, treatment may continue at that dose as long as adequate pain relief is maintained. The use of 24-hour opioid medications and changes in treatment should be reassessed periodically as appropriate. 4. Discontinuation of treatment Abrupt discontinuation of treatment with this drug in patients who are physically dependent on opioids and receive this drug daily may cause withdrawal symptoms. In general, when opioid use must be discontinued, the dose should be reduced gradually. Serious withdrawal symptoms, uncontrolled pain, and suicide have been reported when patients with physical dependence on opioids abruptly discontinued opioid analgesics. Therefore, if discontinuation of treatment with this drug is required, the dose should be reduced by 50 % every 2 days until the patient reaches the lowest possible dose at which treatment can be discontinued safely. If withdrawal symptoms occur, discontinue dose reduction, and slightly increase the dose until opioid withdrawal symptoms resolve. Then resume dose reduction by extending the intervals between dose reductions of this drug, or while switching to another opioid medication at an equianalgesic dose. 5. Patients with renal impairment For patients with moderate (creatinine clearance 40~60mL/min) or severe (creatinine clearance < 30mL/min) renal impairment, use 1/4 ~ 1/2 of the usual hydromorphone hydrochloride dose (see Precautions for Use, section 10. Administration to Patients with Renal Impairment). For patients with severe renal impairment, further extension of the dosing interval should be considered, and patients should be monitored for opioid-related adverse reactions during maintenance treatment.
This medication acts as an analgesic on the central nervous system, and caution should be taken when used with other central nervous system depressants or alcohol, as it may lead to severe respiratory depression or coma. This medication should not be used in patients with allergic reactions, elevated intracranial pressure, severe respiratory depression, chronic pulmonary diseases, or persistent asthma attacks. Patients with impaired liver function or poor kidney function, elderly patients, or those with central nervous system abnormalities should be particularly cautious while using this medication, and if they experience respiratory distress or severe drowsiness during treatment, they should consult healthcare professionals immediately. This medication may frequently cause gastrointestinal side effects such as constipation, nausea, and vomiting, so precautions should be taken for those with a history of constipation or gastrointestinal issues. Neuropsychiatric side effects may include insomnia, anxiety, depression, and confusion, and if these symptoms worsen, consultation with a doctor is advised. This medication may impair concentration and reaction speed during potentially dangerous activities such as driving or operating machinery, so it is best to avoid such activities after taking it. Women who are pregnant or may become pregnant, as well as nursing mothers, should not use this medication, and it should not be administered during labor or immediately after childbirth. This medication is not used in children and adolescents under 18 years of age, as safety and efficacy have not been established. In patients with decreased kidney function, the concentration in the body may increase, so dosage should be adjusted and used cautiously. In case of overdose, symptoms such as severe respiratory depression, decreased consciousness, and hypotension may occur, and immediate emergency care should be sought, including administration of antidotes if necessary. This medication should be stored in a safe place out of reach of children and should not be shared with others.
Enteritis, decreased appetite, insomnia, anxiety, depression, irritability, confused state, abnormal dreams, decreased libido, drowsiness, dizziness, headache, sensory abnormality, tremor, vertigo, palpitations, flushing, shortness of breath, constipation, nausea, vomiting, diarrhea, thirst, abdominal pain, indigestion, intestinal gas retention, itching, sweating, rash, joint pain, weakness, edema, fever, discomfort in the chest, weight loss, falls, contusion, dehydration, mood changes, hallucinations, sedation, sensory reduction, memory impairment, blurred vision, hypertension, exacerbation of gastroesophageal reflux, back pain, muscle cramps, limb pain, myalgia, dysuria, pain, drug withdrawal syndrome, chills, diverticulitis, hypogonadism, fluid retention, increased appetite, hyperuricemia, sleep disorders, panic attacks, discomfort, paranoia, euphoria, lethargy, aggression, dysgeusia, concentration difficulties, stuttering, fainting, decreased consciousness, balance disorders, abnormal cooperation, hypersensitivity, myoclonic-astatic seizures, movement abnormalities, crying, encephalopathy, psychomotor hyperactivity, cognitive impairment, seizures, reflex hyperactivity, diplopia, dry eyes, miosis, tinnitus, tachycardia, extrasystole, bradycardia, hypotension, rhinorrhea, bronchial spasm, hypoxemia, respiratory depression, hyperventilation, sneezing, dysphagia, hematochezia, abdominal distension, hemorrhoids, abnormal stools, intestinal obstruction, diverticulum, belching, gastrointestinal motility disorder, intestinal obstruction, colon perforation, anal fissure, bezoar, duodenitis, gastric outlet obstruction, painful defecation, erythema, skin burning sensation, urinary retention, polyuria, hesitancy in urination, urinary disorders, erectile dysfunction, sexual dysfunction, influenza-like symptoms, malaise, feeling of temperature change, abnormal sensations, anxious feelings, gait disturbances, hangover, feeling drunk, decreased serum potassium, increased liver enzymes, increased serum amylase, decreased serum testosterone, decreased body temperature, overdose, hypersensitivity reactions, angioedema, urticaria, sleep apnea syndrome, yawning, sneezing, tearing, sweating, nausea, mydriasis, delirium, spasms, tremors, pain in the muscles and joints throughout the body, respiratory distress, palpitations, slow breathing, irregular breathing, apnea, loss of consciousness, coma, skeletal muscle relaxation, cold skin, miosis, bradycardia, hypotension, weakness, edema, coldness, fever, malaise, discomfort in the chest, difficulty walking, influenza-like syndrome, pain, weight loss
Not everyone experiences these, and they can vary from person to person.
This medication is sensitive to light, so it should be stored in a container that blocks light. Additionally, it is important to store it at a cool temperature below 25 degrees Celsius to maintain the effectiveness of the medication.
Red round, biconvex sustained release tablet
28 tablets (7 tablets * 4 PTP) / box
Even with the same ingredient, strength, dosage form and how it is taken can differ.
Hydromorphone Hydrochloride
Prescription medication
Korea Janssen Co., Ltd.
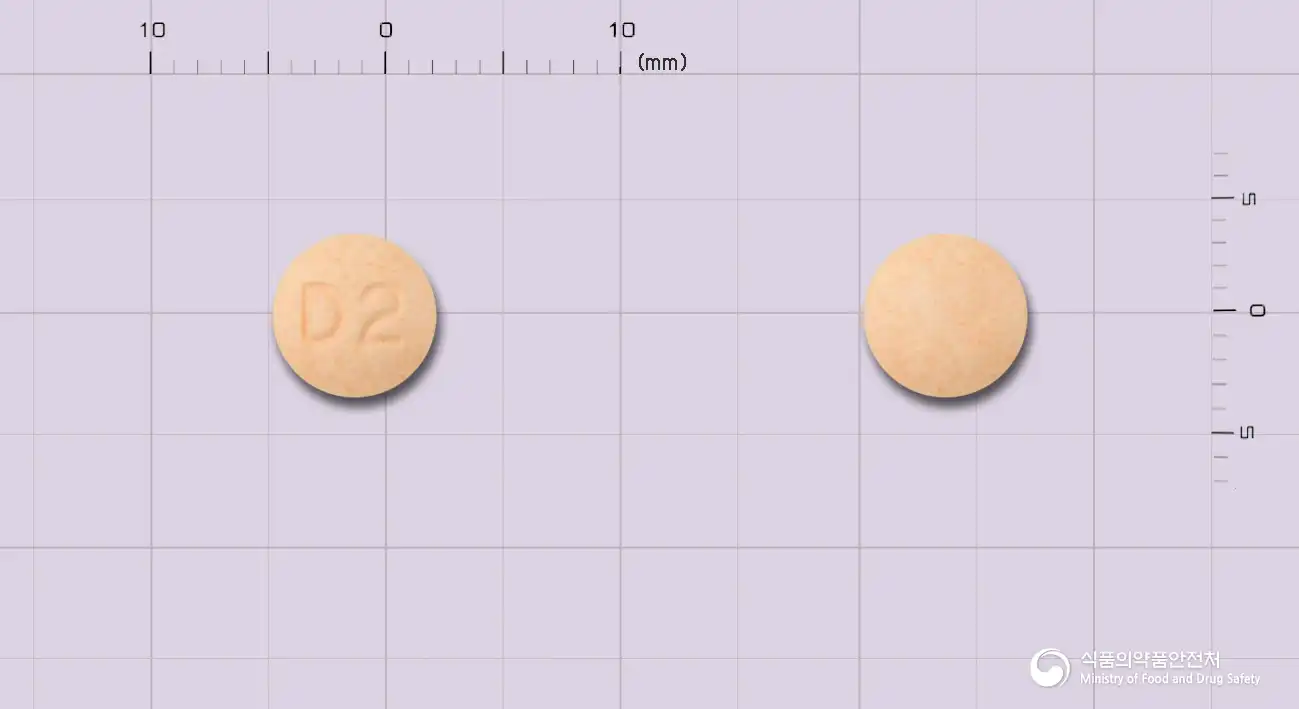
Hydromorphone Hydrochloride 2mg
Tablet · Prescription medication
Hana Pharmaceutical Co., Ltd.
Hydromorphone Hydrochloride
Prescription medication
Hana Pharmaceutical Co., Ltd.
Hydromorphone Hydrochloride
Prescription medication
Hana Pharmaceutical Co., Ltd.
Hydromorphone Hydrochloride 1mg
Solution · Prescription medication
Hana Pharmaceutical Co., Ltd.
Hydromorphone Hydrochloride 2mg
Solution · Prescription medication
Hana Pharmaceutical Co., Ltd.
Hydromorphone Hydrochloride
Prescription medication
Hana Pharmaceutical Co., Ltd.
Hydromorphone Hydrochloride
Prescription medication
Hana Pharmaceutical Co., Ltd.
Even with the same ingredient, the dose and directions can differ by strength and dosage form. Talk to a doctor or pharmacist before switching from a medication you are already taking.
No questions yet.
For anything that needs medical judgment, consult a doctor or pharmacist.
This drug information is based on data provided by the Korea Ministry of Food and Drug Safety.
Consult a doctor or pharmacist for accurate dosage, administration, and usage instructions.