
 한국어
 English
 日本語
 中文(简体)
 Viewing now
Sprycel 70 mg Tablet (Dasatinib)
Dasatinib 70mg
Tablet · Prescription medication
Korea BMS Pharmaceutical Co., Ltd.
MFDS item code 200701085 · Approved 2007.01.25
Treatment of Philadelphia chromosome-positive chronic myeloid leukemia and acute lymphoblastic leukemia
This drug is used for the treatment of newly diagnosed Philadelphia chromosome positive chronic myeloid leukemia and acute lymphoblastic leukemia, as well as for patients who exhibit resistance or intolerance to imatinib therapy. It is effective for both adults and pediatric patients aged over 1 year, making it applicable across various age groups. In particular, this drug has demonstrated treatment efficacy based on cytological and molecular response rates, helping to improve patient conditions. It is applicable to both acute and chronic conditions, contributing to the suppression of disease progression and alleviation of symptoms. In summary, this drug is widely used in the treatment of Philadelphia chromosome positive leukemia, aiding in the relief of the disease and patient recovery.
The recommended initial dose of this drug for chronic-phase chronic myeloid leukemia is 100mg orally once daily. The recommended initial dose of this drug for accelerated-phase or myeloid or lymphoid blast-phase chronic myeloid leukemia, and Philadelphia chromosome-positive acute lymphoblastic leukemia (Ph+ ALL), is 140mg orally once daily. This drug should be swallowed whole without crushing or cutting it. This drug may be taken in the morning or evening, with or without food. If this drug must be administered with a strong CYP3A4 inhibitor, dose reduction should be considered as follows. ㆍ Patients receiving 140mg of this drug once daily: 40mg once daily ㆍ Patients receiving 100mg of this drug once daily: 20mg once daily ㆍ Patients receiving 70mg of this drug once daily: 20mg once daily For patients receiving 60mg or 40mg of this drug once daily, discontinuation of this drug should be considered until the CYP3A4 inhibitor is discontinued. In clinical studies in adult patients with chronic myeloid leukemia (CML) and Philadelphia chromosome-positive acute lymphoblastic leukemia (Ph+ ALL), for patients who did not achieve a hematologic and cytogenetic response at the recommended initial dose, dose escalation to 140mg once daily (patients with chronic-phase chronic myeloid leukemia) or 180mg once daily (patients with accelerated-phase or blast-phase chronic myeloid leukemia and patients with Philadelphia chromosome-positive acute lymphoblastic leukemia) was permitted. Chronic-phase chronic myeloid leukemia (chronic phase CML): Initiate treatment at a dose of 100mg once daily Absolute neutrophil count less than 0.5 x 10⁹/L or platelet count less than 50 x 109/L: Interrupt treatment with this drug until the absolute neutrophil count is at least 1.0 x 10⁹/L and the platelet count is at least 50 x 109/L. If recovery occurs within 7 days or less, resume treatment with this drug at the starting dose. If a platelet count below 25 x 109/L or an absolute neutrophil count below 0.5 x 10⁹/L for more than 7 days recurs, repeat step 1; upon the 2nd recurrence, resume at a reduced dose of 80mg once daily. Upon the 3rd recurrence, further reduce the dose to 50mg once daily for newly diagnosed patients, and discontinue this drug in patients resistant or intolerant to prior therapy, including imatinib. Accelerated-phase or blast-phase chronic myeloid leukemia and Philadelphia chromosome-positive acute lymphoblastic leukemia: Initiate treatment at a dose of 140mg once daily Absolute neutrophil count below 0.5 x 10⁹/L or platelet count below 10 x 109/L: Determine whether the cytopenia is related to leukemia (bone marrow aspiration or biopsy). If the cytopenia is not related to leukemia, interrupt treatment with this drug until the absolute neutrophil count is at least 1.0 x 10⁹/L and the platelet count is at least 20 x 109/L, then resume treatment at the starting dose. If the cytopenia recurs, repeat step 1; upon the 2nd recurrence, resume treatment with this drug at a reduced dose of 100 mg once daily, and upon the 3rd recurrence, at a reduced dose of 80mg once daily. If the cytopenia is related to leukemia, increase the dose to 180mg once daily. In adult patients with Ph+ CML and ALL, if serious nonhematologic adverse reactions occur with this drug, treatment should be withheld until the reaction resolves or improves. Treatment may then be resumed at a reduced dose, as appropriate, depending on the symptoms and recurrence of the reaction.
10kg or more and less than 20kg: 40mg 20kg or more and less than 30kg: 60mg 30kg or more and less than 45kg: 70mg 45kg or more: 100mg Not recommended for patients weighing less than 10kg. The recommended initial dose in pediatric patients is based on body weight, as shown in Table 1. This drug is administered orally once daily, regardless of meals. Recalculate the dose every 3 months or more frequently as needed based on changes in body weight. For pediatric patients with CML who do not achieve a hematologic or cytogenetic response at the recommended initial dose, the dose increases shown in Table 2 below are recommended. Initial dose 40mg: increased dose 50mg Initial dose 60mg: increased dose 70mg Initial dose 70mg: increased dose 90mg Initial dose 100mg: increased dose 120mg Dose escalation of this drug is not recommended when it is administered in combination with chemotherapy to pediatric patients with Ph+ ALL. Dose adjustments for neutropenia and thrombocytopenia in pediatric patients with chronic-phase CML: initial dose 40mg, first dose reduction 20mg, second dose reduction ** Dose adjustments for neutropenia and thrombocytopenia in pediatric patients with chronic-phase CML: initial dose 60mg, first dose reduction 40mg, second dose reduction 20mg Dose adjustments for neutropenia and thrombocytopenia in pediatric patients with chronic-phase CML: initial dose 70mg, first dose reduction 60mg, second dose reduction 50mg Dose adjustments for neutropenia and thrombocytopenia in pediatric patients with chronic-phase CML: initial dose 100mg, first dose reduction 80mg, second dose reduction 70mg In pediatric patients with chronic-phase CML, if grade 3 or higher neutropenia or thrombocytopenia recurs during complete hematologic response (CHR), treatment with this drug should be interrupted and may subsequently be resumed at a reduced dose. Temporary dose reductions may be made as needed for moderate cytopenia and disease response. In pediatric patients with ALL, if the next treatment block is delayed for 14 days or more due to neutropenia or thrombocytopenia, this drug should be interrupted and resumed at the same dose when the next treatment block begins. If neutropenia or thrombocytopenia persists and the next treatment block is delayed for an additional 7 days, a bone marrow examination should be performed to assess cellularity and the percentage of blasts. If bone marrow cellularity is less than 10%, treatment with this drug should be interrupted until the absolute neutrophil count exceeds 500/μL(0.5 x 109/L); treatment may be resumed at the normal dose. If bone marrow cellularity exceeds 10%, resumption of treatment with this drug may be considered. In pediatric patients with Ph+ CML, if serious nonhematologic adverse reactions occur with this drug, treatment should be withheld until the reactions resolve or improve. Thereafter, when appropriate, treatment may be resumed at a reduced dose depending on the symptoms and recurrence of the reactions. For dose adjustments in pediatric patients with Ph+ ALL who develop grade 2 nonhematologic toxicity, refer to Table 5. If nonhematologic adverse reactions of grade 3 or higher occur, excluding abnormal liver function tests, treatment should be interrupted and resumed at a reduced dose once the adverse reactions resolve to grade 1 or lower. If direct bilirubin increases to more than 5 times the upper limit of normal (ULN), treatment should be interrupted until the level returns to baseline or below grade 1. If AST/ALT increases to more than 15 times the ULN, treatment should be interrupted until the levels return to baseline or below grade 1. If the above abnormalities in liver function tests recur, the dose of this drug should be reduced if the adverse reaction recurs after the drug is re-administered. Dose adjustments for nonhematologic adverse reactions in pediatric patients: initial dose 40mg, first dose reduction 20mg, second dose reduction ** Dose adjustments for nonhematologic adverse reactions in pediatric patients: initial dose 60mg, first dose reduction 40mg, second dose reduction 20mg Dose adjustments for nonhematologic adverse reactions in pediatric patients: initial dose 70mg, first dose reduction 60mg, second dose reduction 50mg Dose adjustments for nonhematologic adverse reactions in pediatric patients: initial dose 100mg, first dose reduction 80mg, second dose reduction 70mg If grade 2 nonhematologic toxicity occurs, consider interrupting this drug if the toxicity does not resolve despite treatment of the symptoms. Resume treatment at the starting dose once the adverse reaction resolves to grade 1 or lower. For recurrent adverse reactions, resume treatment at a reduced dose. If grade 3 nonhematologic toxicity occurs, interrupt this drug until it resolves to grade 1 or lower, then resume treatment at a reduced dose. If direct bilirubin increases to more than 5 times the upper limit of normal or AST/ALT increases to more than 15 times the upper limit of normal, interrupt this drug until the levels resolve to below grade 1, then resume treatment at the starting dose. For recurrent adverse reactions, resume treatment at a reduced dose.
This drug can cause serious harm to the fetus if administered to pregnant women; therefore, women who may become pregnant must strictly avoid pregnancy. Patients allergic to any of the ingredients in this drug or with genetic lactose intolerance should not take this medicine. Patients requiring antiplatelet or anticoagulant therapy should exercise caution when using this drug, as the risk of bleeding may be increased. QT interval related to heart rate may be prolonged; therefore, patients with hypokalemia, hypomagnesemia, congenital long QT syndrome, or those taking certain heart medications should use this drug cautiously. Since the metabolism of this drug may be affected in patients with impaired liver function, administration should be carefully monitored based on their liver function status. There is a risk of developing pulmonary arterial hypertension during treatment; thus, if symptoms such as shortness of breath, fatigue, or hypoxia occur, immediate consultation with a healthcare professional is necessary. Patients who are carriers of the hepatitis B virus must consult a specialist before taking this drug and should monitor for viral activation closely during treatment. This drug may suppress bone marrow function, leading to a decrease in blood cell counts; regular blood tests should be performed to monitor the condition. Fluid retention may occur, so if symptoms such as edema or shortness of breath appear, they should be reported immediately, and appropriate treatment should be sought if necessary. Severe skin reactions can occur infrequently, so if symptoms such as skin rash or mucosal abnormalities develop, discontinue use immediately and consult a healthcare professional. Elderly patients may experience side effects such as fatigue, pleural effusion, or shortness of breath more frequently when taking this drug, necessitating closer observation. In cases of overdose, severe bone marrow suppression and bleeding can occur, so recommended dosages must be followed, and in the event of overdose, medical institutions should be visited immediately. This drug should be stored at room temperature between 15 to 30 degrees Celsius, and broken or crushed tablets should be handled safely with gloves to avoid skin contact.
Not everyone experiences these, and they can vary from person to person.
This drug should be stored in a sealed container to protect it from air and moisture, and kept in a cool place at temperatures between 15 to 30 degrees Celsius. Storing it this way will help maintain the drug's effectiveness for a longer time.
White to off-white, biconvex, round film-coated tablet, engraved with 'BMS' on one side and '524' on the other side.
60 tablets/PTP
Even with the same ingredient, strength, dosage form and how it is taken can differ.
Viewing nowDasatinib 70mg
Tablet · Prescription medication
Korea BMS Pharmaceutical Co., Ltd.
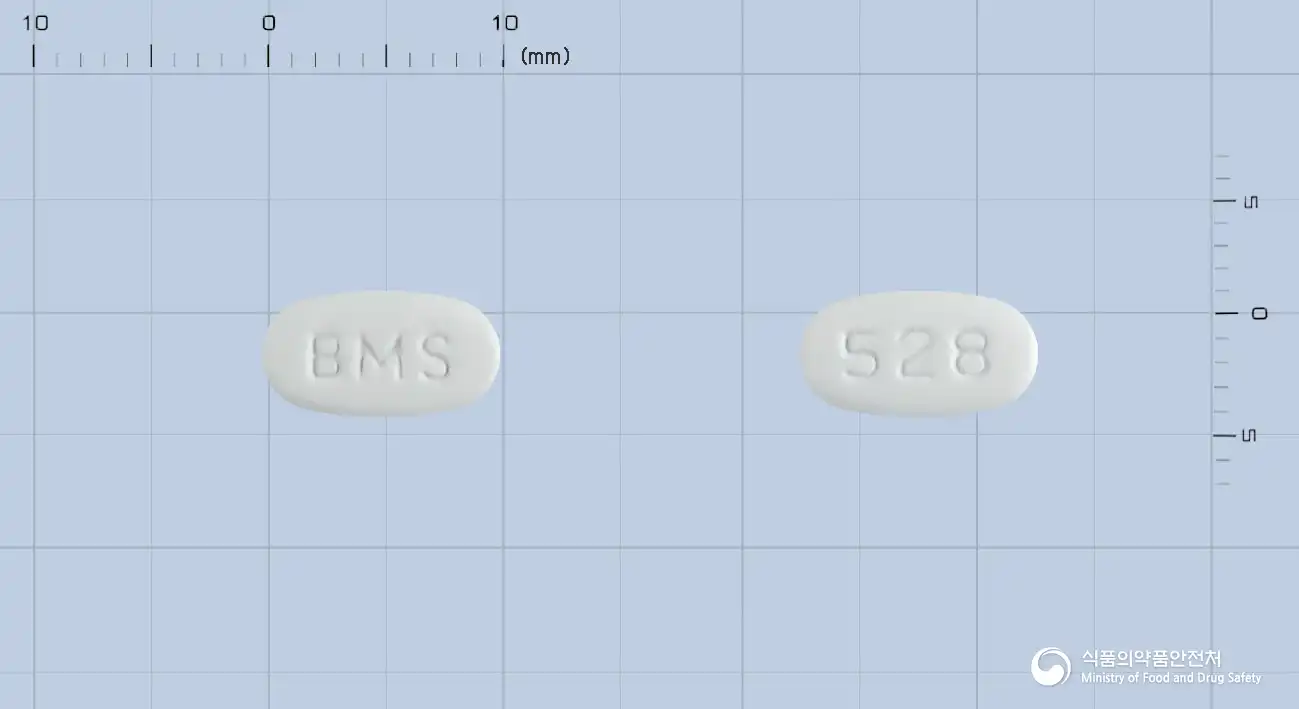
Dasatinib 50mg
Tablet · Prescription medication
Korea BMS Pharmaceutical Co., Ltd.
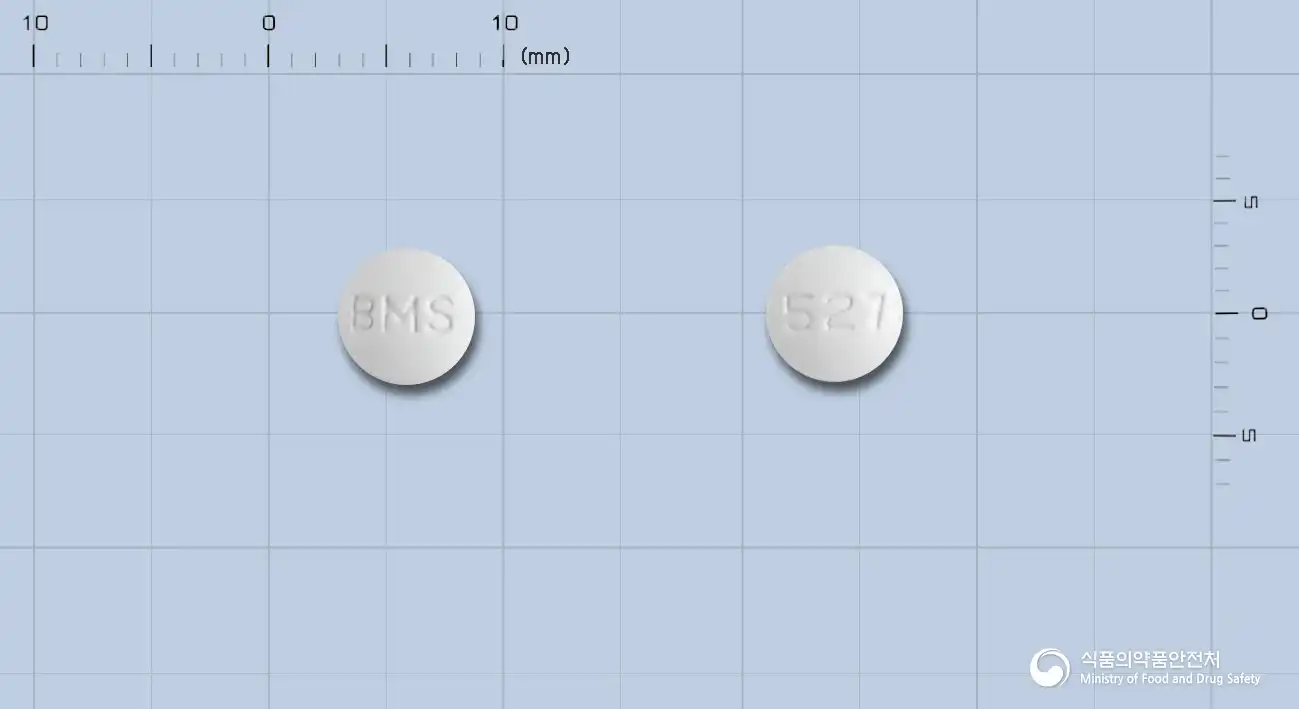
Dasatinib 20mg
Tablet · Prescription medication
Korea BMS Pharmaceutical Co., Ltd.
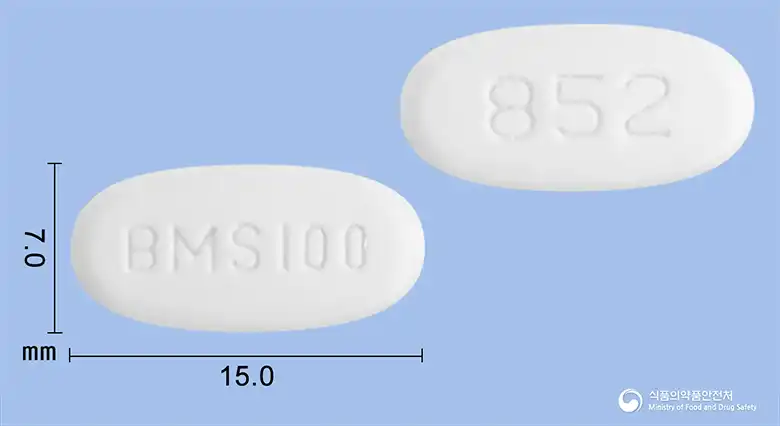
Dasatinib 100mg
Tablet · Prescription medication
(Yoo) Korea BMS Pharmaceuticals
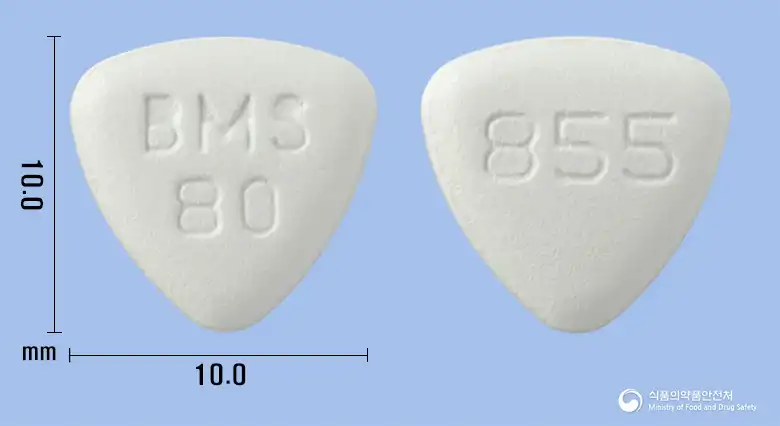
Dasatinib 80mg
Tablet · Prescription medication
(Co., Ltd.) Hanmi Pharmaceutical Company
Even with the same ingredient, the dose and directions can differ by strength and dosage form. Talk to a doctor or pharmacist before switching from a medication you are already taking.
No questions yet.
For anything that needs medical judgment, consult a doctor or pharmacist.
This drug information is based on data provided by the Korea Ministry of Food and Drug Safety.
Consult a doctor or pharmacist for accurate dosage, administration, and usage instructions.