
 한국어
 English
 日本語
 中文(简体)
 Viewing now
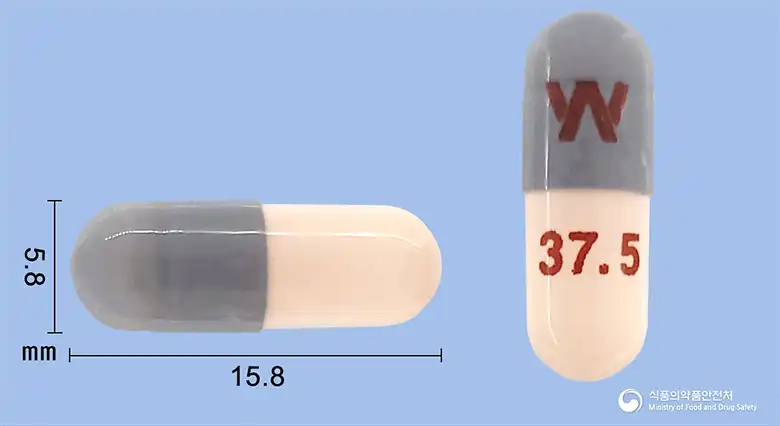
Effexor XR Extended-Release Capsule 37.5 mg
Venlafaxine Hydrochloride 42.43mg
Prescription medication
Viatriss Korea Co., Ltd.
MFDS item code 200308354 · Approved 2003.11.21 · Insurance code 073400040
Treatment of depression and anxiety disorders (generalized anxiety disorder, panic disorder, etc.)
This medication is used to treat major mental health issues such as depression, generalized anxiety disorder, social phobia, and panic disorder.
The therapeutic dose of this medicine should be adjusted according to the patient's clinical condition, and the lowest effective dose should be administered whenever possible. Take this medicine with food, at a consistent time in the morning or evening if possible. Do not divide, crush, chew, or dissolve the capsule in water before taking it. 1. Depression and generalized anxiety disorder The recommended initial dose is 75 mg of venlafaxine hydrochloride orally once daily. Depending on the patient, 37.5 mg once daily may be administered for 4∼7 days after starting treatment to allow the patient to adjust to the medicine before increasing the dose to 75 mg daily. If further clinical improvement is needed after 2 weeks of treatment, the dose may be increased to 150 mg daily. If necessary, the dose may be increased to a maximum of 225 mg daily. Dose increases should be no more than 75 mg daily and should be made at intervals of at least 4 days. Patients with depression who are currently taking immediate-release tablets containing this ingredient may be switched to this medicine at a dose closest to their tablet dose. For example, patients taking 37.5 mg of the immediate-release tablet containing this ingredient twice daily may take 75 mg of this medicine once daily. Individual dose adjustment may be necessary when switching. 2. Social anxiety disorder The recommended dose is 75 mg of venlafaxine hydrochloride orally once daily. There is no evidence of additional benefit from increasing the dose. 3. Panic disorder The recommended initial dose is 37.5 mg of venlafaxine hydrochloride once daily for 7 days. In clinical trials conducted in outpatients with panic disorder to evaluate the efficacy of this medicine, an initial dose of 37.5 mg once daily was administered for 7 days, followed by an increase to 75 mg once daily and then successive increases of 75 mg at 1-week intervals, up to 225 mg daily. Although the dose-response relationship for the efficacy of this medicine in patients with panic disorder has not been clearly established, some patients who do not respond to 75 mg/day may benefit from an increase to a maximum of 225 mg daily. If the dose is increased, it should be increased by no more than 75 mg daily as needed, at intervals of at least 7 days. 4. Dosing in special populations 1) Patients with hepatic impairment In patients with hepatic impairment, clearance of venlafaxine and O-desmethylvenlafaxine (ODV) is reduced and their half-lives are prolonged; therefore, the dose should be reduced by 50 % in patients with moderate hepatic impairment. Because drug clearance varies considerably among patients with cirrhosis, dosage adjustment should be individualized. 2) Patients with renal impairment In patients with renal impairment (GFR=10∼70 mL/min), clearance of this medicine is reduced and the half-lives of venlafaxine and ODV are increased compared with those in healthy individuals. Therefore, the total daily dose should be reduced by 25∼50%; in patients receiving hemodialysis, the total daily dose should be reduced by 50%, and the medicine should be administered after hemodialysis is complete. Because drug clearance varies considerably among patients with renal impairment, dosage adjustment should be individualized. 5. Maintenance/continuation/long-term treatment The physician should periodically assess the effectiveness of long-term treatment with this medicine for each patient. Although there is no clinical trial evidence on how long this medicine should be administered to patients with depression, generalized anxiety disorder, social anxiety disorder, or panic disorder, it is generally agreed that acute depression requires continued pharmacotherapy for several months or longer. 6. Discontinuation of treatment with this medicine If treatment is discontinued after this medicine has been administered for more than 1 week, the dose should be gradually reduced over several days to minimize withdrawal symptoms. In patients who have received this medicine for more than 6 weeks, the dose should be gradually reduced over at least 2 weeks. Although withdrawal symptoms associated with this medicine have not been fully evaluated, adverse reactions that occurred in 3% or more of patients during dose reduction and after discontinuation, and at more than twice the rate observed with placebo, included hypomania, anxiety, agitation, nervousness, confusion, insomnia or sleep disturbance, fatigue, somnolence, paresthesia, dizziness, headache, sweating, dry mouth, anorexia, diarrhea, nausea, and vomiting. These withdrawal symptoms were mild and resolved without treatment. However, the duration of dose reduction and the amount of dose reduction may vary depending on the dose, duration of treatment, and patient. In some patients, discontinuation may take several months or longer. 7. Switching from MAO inhibitors used to treat psychiatric disorders At least 14 days should elapse between discontinuing an MAO inhibitor used to treat psychiatric disorders and starting treatment with this medicine. Conversely, at least 7 days should elapse after discontinuing this medicine before starting an MAO inhibitor to treat psychiatric disorders. 8. Other MAO inhibitors, such as linezolid or methylene blue Patients receiving linezolid or intravenous methylene blue should not start treatment with this medicine because of the increased risk of serotonin syndrome. In patients requiring other interventional procedures, including hospitalization, or more urgent treatment for a psychiatric condition, treatment should be considered. It may be necessary to urgently administer linezolid or intravenous methylene blue to a patient already receiving this medicine. If no alternative to linezolid or intravenous methylene blue is available and the benefits of treatment with linezolid or intravenous methylene blue are judged to outweigh the risk of serotonin syndrome in a particular patient, discontinue this medicine immediately and administer linezolid or intravenous methylene blue. Monitor the patient for symptoms of serotonin syndrome for 7 days after administration of linezolid or intravenous methylene blue, or until 24 hours after the last dose, whichever occurs first. Treatment with this medicine may be resumed 24 hours after the last dose of linezolid or intravenous methylene blue. The risk associated with methylene blue administered by non-intravenous routes (oral tablets or local injection) or with intravenous administration of this medicine at 1mg/kg or less is unclear. Nevertheless, clinicians should be aware of the possibility of emergency symptoms of serotonin syndrome with these uses.
This medication may have a negative effect on the central nervous system when taken with alcohol, thus patients should avoid alcohol during treatment. This medication is not approved for use in children and adolescents under 18 years, and in young adults, there may be an increased risk of suicidal thoughts or behaviors, so careful observation is necessary. It may raise blood pressure, so patients should have their blood pressure measured regularly while taking this medication, and if their blood pressure consistently increases, they should consult a physician. There is a risk of severe neurological adverse reactions such as serotonin syndrome, so caution should be taken when using this medication with other serotonergic agents, and if symptoms appear, treatment should be stopped immediately and medical advice sought. This medication should not be used in conjunction with certain drugs, especially MAO inhibitors, and should not be taken by women who are pregnant or breastfeeding. When starting treatment or changing doses, careful observation for worsening depressive symptoms, suicidal thoughts, or aggressive behavior is needed, and patients and their guardians should be educated to recognize and report these symptoms immediately. Patients with a history of seizures may have an increased risk of seizures while on this medication, and if a rash or allergic reaction occurs, they should notify their physician immediately. Patients with reduced kidney or liver function may require dose adjustments, and those with a history of drug abuse should be carefully monitored for misuse potential. Abrupt discontinuation of this medication can cause withdrawal symptoms, so doses should be gradually reduced under a physician's guidance and not stopped on one's own. This medication can cause sexual dysfunction, and symptoms may persist during or after discontinuation of treatment, so this should be acknowledged and consulted about if needed. Caution is required when driving or operating hazardous machinery, especially in the initial stages of treatment, as it is necessary to check physical responses. Regular check-ups, including blood tests, are recommended to monitor liver function, blood pressure, and blood cholesterol levels during this medication.
Negative interactions with alcohol, increased risk of suicidal thoughts and behavior, persistent hypertension, serotonin syndrome, neuroleptic malignant syndrome-like reactions, insomnia, irritability, drowsiness, dizziness, headache, weakness, nausea, dry mouth, decreased appetite, vomiting, tremors, sweating, erectile dysfunction, decreased libido, abnormal ejaculation, vasodilation, increased blood pressure, anxiety, agitation, panic attacks, excitability, hostility, aggression, impulsivity, akathisia, hypomania, manic episodes, worsening of depression, suicidal ideation, rash, urticaria, sweating, sexual dysfunction, constipation, bloating, abnormal sensations, abnormal dreams, visual disturbances, yawning, treatment discontinuation due to increased blood pressure, weight loss, increased serum cholesterol, increased pulse, migraine, orthostatic hypotension, tachycardia, angina, arrhythmia, hypotension, syncope, thrombophlebitis, thyroid dysfunction, anemia, leukocyte abnormalities, platelet abnormalities, hyponatremia, edema, diabetes, liver dysfunction, arthralgia, arthritis, myasthenia gravis, tendinitis, rhabdomyolysis, forgetfulness, confusion, depersonalization, emotional instability, increased muscle tone, tremors, hallucinations, psychosis, seizures, stupor, agitation, akinesia, aphasia, dysarthria, loss of consciousness, delusions, dementia, suicidal thoughts, convulsions, neuroleptic malignant syndrome, serotonin syndrome, feeling intoxicated, impulse control disorder, incomplete paralysis, dyspnea, increased cough, asthma, pneumonia, itching, rash, acne, alopecia, dry skin, eczema, urticaria, cataracts, conjunctivitis, diplopia, ocular pain, hyperacusis, taste disturbances, visual impairment, abnormal uterine bleeding, prostatitis, urination disorders, vaginitis, galactorrhea, menorrhagia, mastalgia, urinary incontinence, miscarriage, prolonged erection, gynecomastia, renal stones, renal dysfunction, menopause, pyelonephritis, frequency of urination, urinary calculi, uterine bleeding, uterine contractions, orchitis, vaginal dryness, anaphylaxis, angioedema, ventricular tachycardia, stress-induced cardiomyopathy, pancreatitis, agranulocytosis, aplastic anemia, pancytopenia, inappropriate secretion of antidiuretic hormone syndrome, liver function test abnormalities, rhabdomyolysis syndrome, psychomotor instability, delirium, extrapyramidal symptoms, coordination and balance disorders, tardive dyskinesia, interstitial lung disease, Stevens-Johnson syndrome, toxic epidermal necrolysis, erythema multiforme, angle-closure glaucoma, fractures, tension, panic, renal failure, electric shock-like symptoms, withdrawal symptoms (hypomania, anxiety, agitation, irritability, confusion, coordination and balance disorders, depressed mood, emotional instability, insomnia, hypersomnia, nightmares, fatigue, drowsiness, sensory disturbances, convulsions, tremors, seizures, muscle fasciculations, headache, flu-like symptoms, tinnitus, dry mouth, decreased appetite, diarrhea, vomiting, visual impairment, hypertension
Not everyone experiences these, and they can vary from person to person.
This medication should be stored in a tightly closed container to protect it from air and moisture. It should be kept away from direct sunlight and stored in a cool place at or below 25 degrees Celsius.
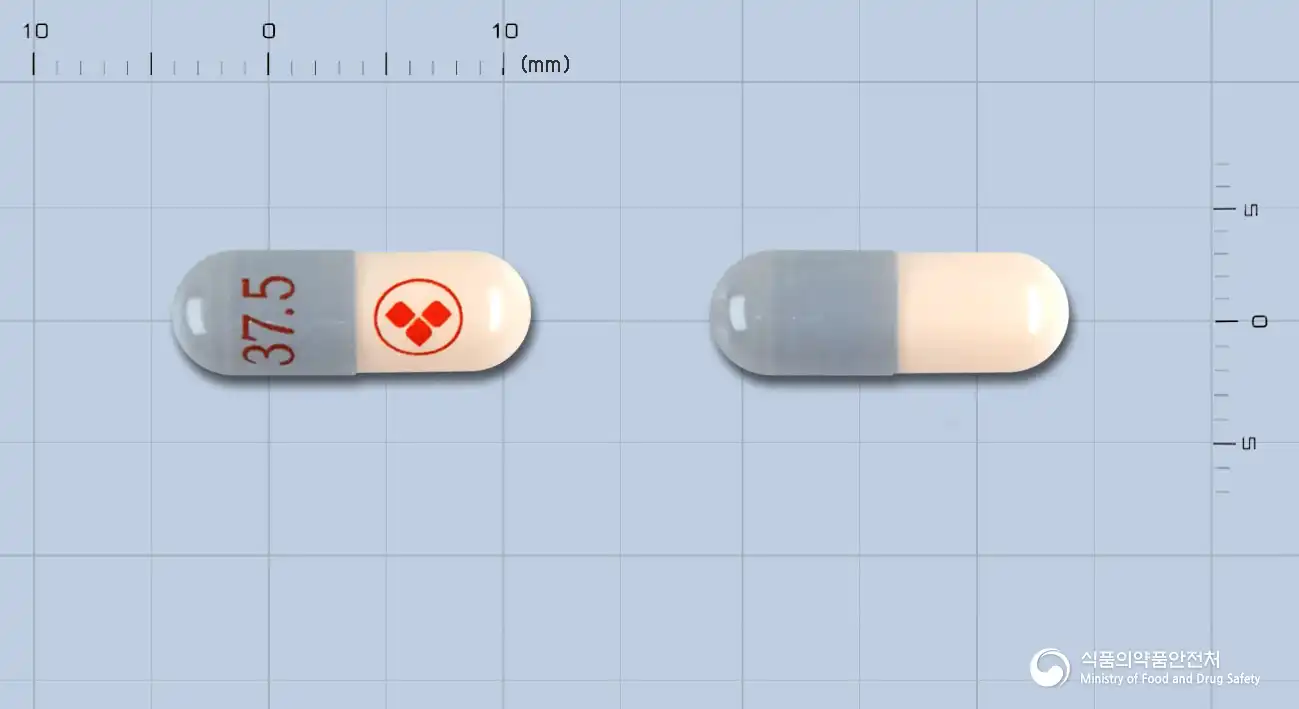
A gray capsule with white-gray granules inside for the upper part and peach-colored for the lower part
28 capsules (7 capsules/blister X 4)
Even with the same ingredient, strength, dosage form and how it is taken can differ.
Viewing nowVenlafaxine Hydrochloride 42.43mg
Prescription medication
Viatriss Korea Co., Ltd.

Venlafaxine Hydrochloride 84.85mg
Prescription medication
Viatris Korea Co., Ltd.
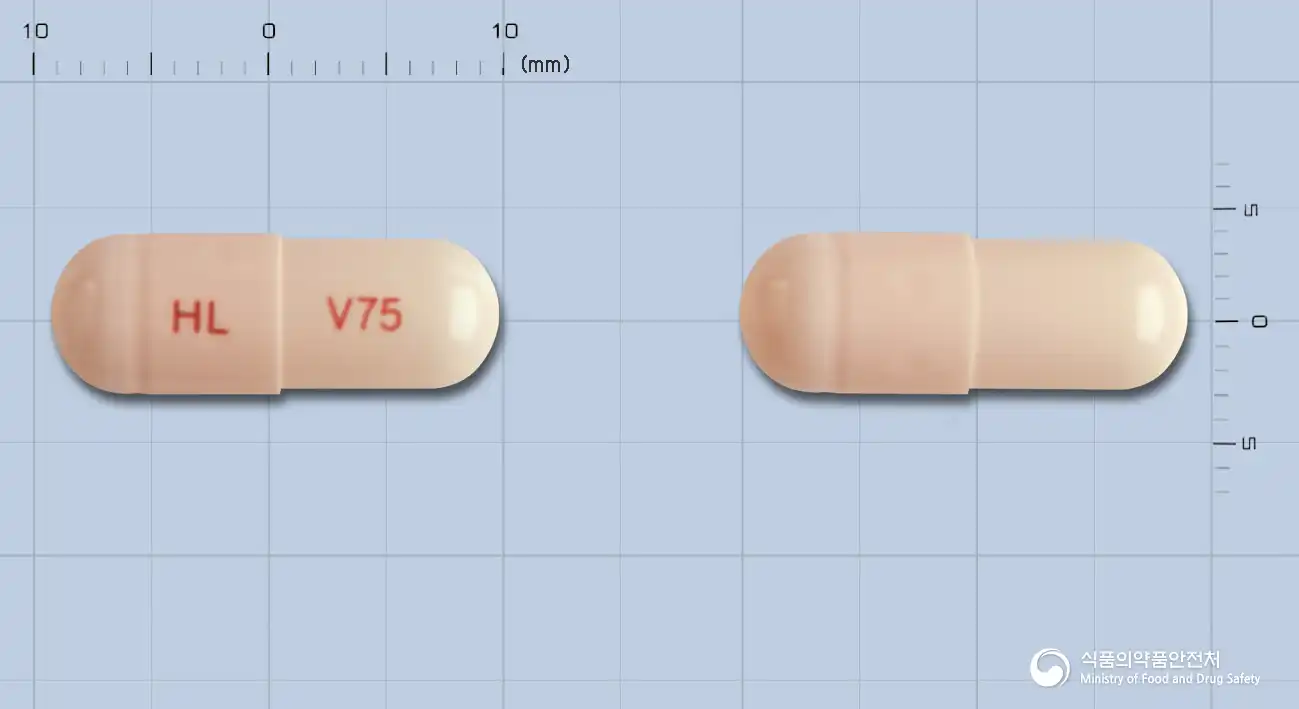
Venlafaxine Hydrochloride 84.84mg
Prescription medication
Hanlim Pharmaceutical Co., Ltd.
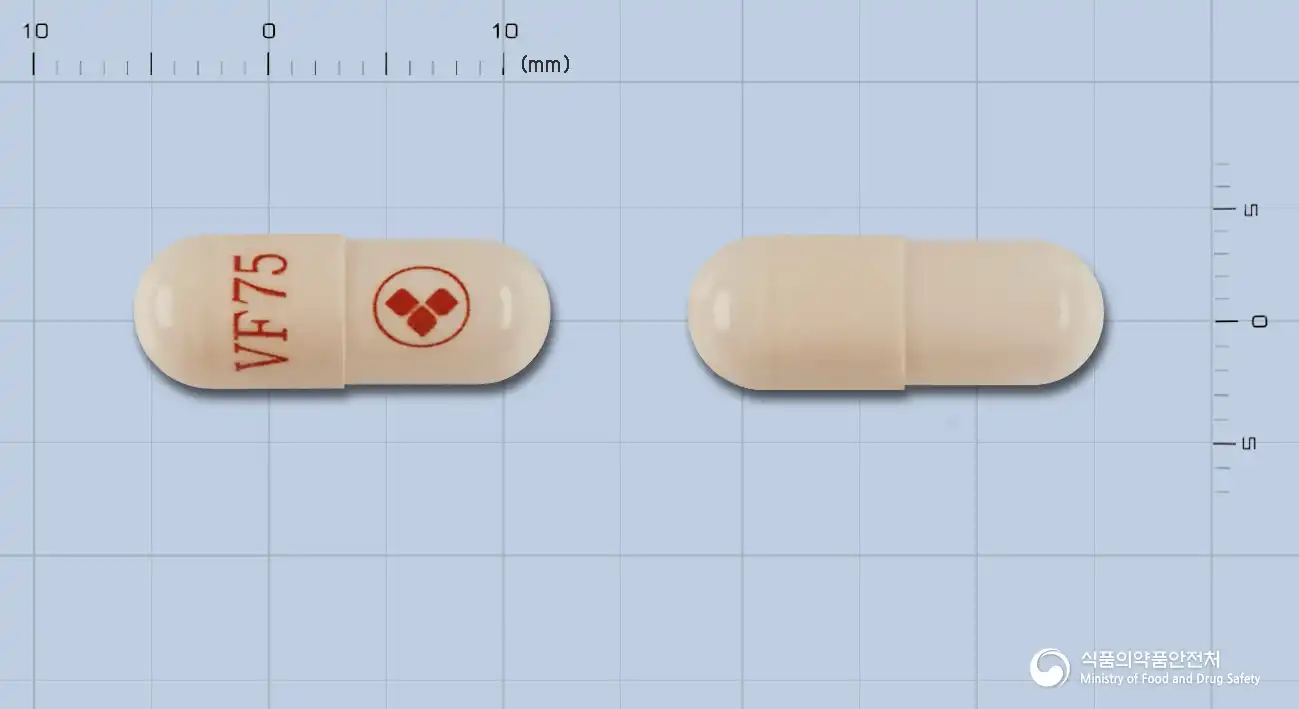
Venlafaxine Hydrochloride 84.85mg
Prescription medication
Myungin Pharmaceutical Co., Ltd.
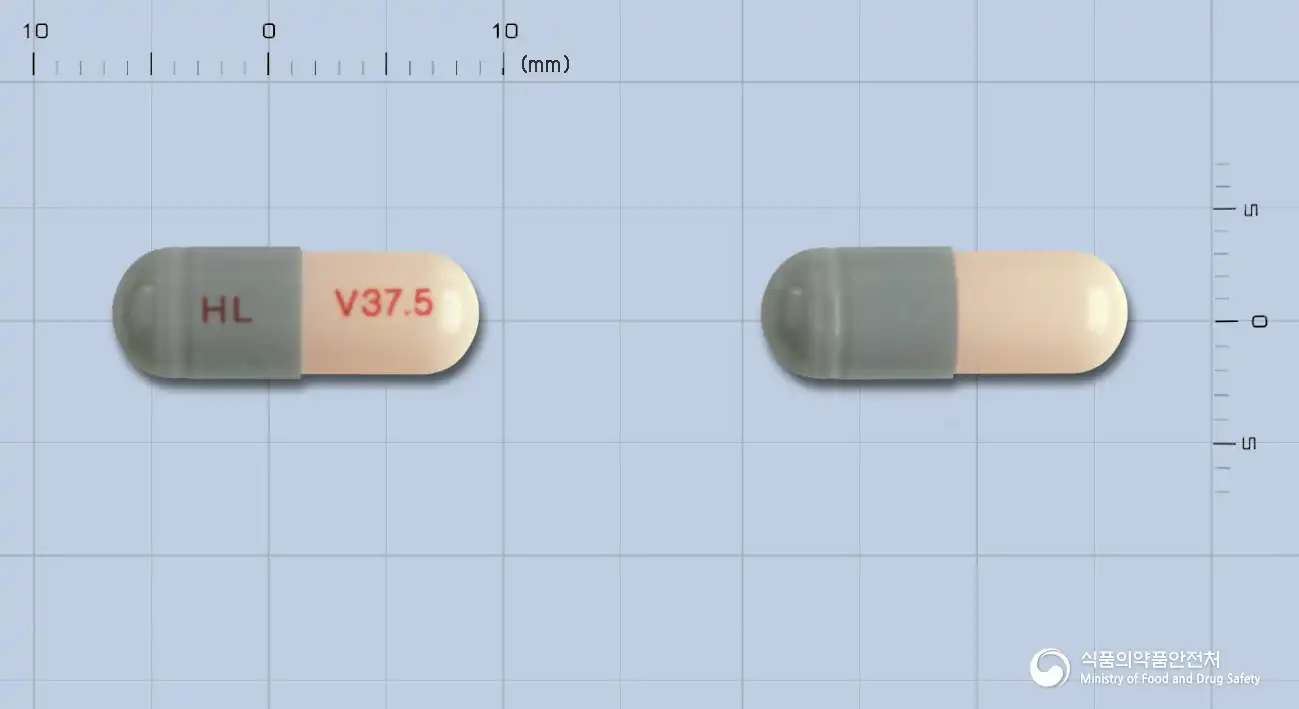
Venlafaxine Hydrochloride 42.42mg
Prescription medication
Hanhim Pharmaceutical Co., Ltd.
Venlafaxine Hydrochloride 42.425mg
Hard capsule · Prescription medication
Myungjin Pharmaceutical Co., Ltd.
Even with the same ingredient, the dose and directions can differ by strength and dosage form. Talk to a doctor or pharmacist before switching from a medication you are already taking.
No questions yet.
For anything that needs medical judgment, consult a doctor or pharmacist.
This drug information is based on data provided by the Korea Ministry of Food and Drug Safety.
Consult a doctor or pharmacist for accurate dosage, administration, and usage instructions.