
 한국어
 English
 日本語
 中文(简体)
 Viewing now
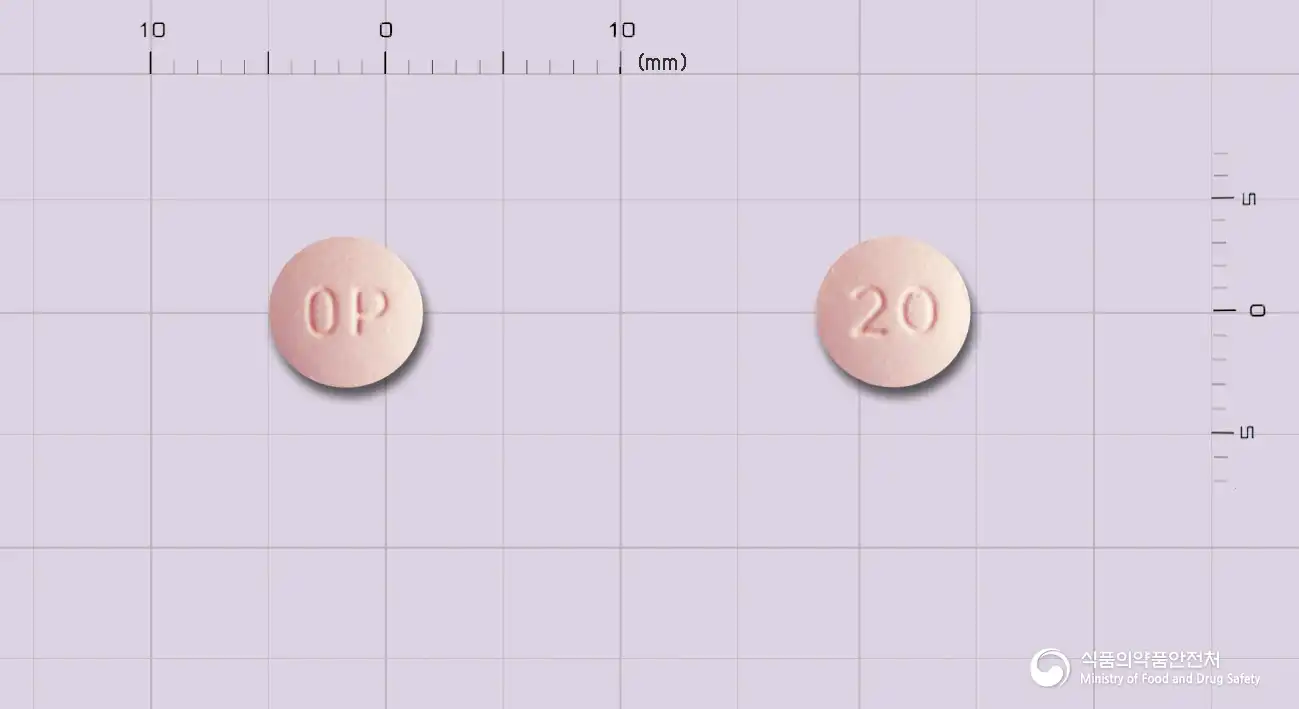
OxyContin Extended-Release Tablets 20mg (Oxycodone Hydrochloride)
Oxycodone Hydrochloride 20mg
Tablet · Prescription medication
Korea Mundi Pharma Co., Ltd.
MFDS item code 200009387 · Approved 2000.09.01 · Insurance code 678000100
Relief of moderate to severe pain requiring opioid analgesics
This medication is used to effectively control various pains ranging from moderate to severe. It particularly helps in managing severe pain, such as postoperative pain or cancer pain. Its analgesic effect is strong and contributes to pain relief and quality of life improvement for patients. When used safely, it can significantly reduce pain and allow comfortable maintenance of daily life. It should be taken exactly as prescribed by a physician, controlling pain while minimizing side effects. This medication is used for moderate to severe pain control.
This medicine should be swallowed one tablet at a time. It should be taken with plenty of water immediately after placing it in the mouth and swallowed completely. This medicine is taken orally at 12-hour intervals. For most patients, dosing times are set symmetrically at 12-hour intervals (the same time in the morning and evening), but for some patients, asymmetric dosing intervals based on their pain pattern may be preferable. In general, the lowest dose that provides effective pain relief should be selected. If a higher dose is needed, the dose may be increased by 25~50% of the current dose, whenever possible. The dose of this medicine should be increased for patients who require rescue medication more than 2 times a day. This medicine should be taken consistently either with food or on an empty stomach. Patients who have not previously taken opioid analgesics; the recommended initial dose for these patients is 10 mg of oxycodone hydrochloride every 12 hours. Patients taking combination products containing an opioid analgesic and aspirin, acetaminophen, or a nonsteroidal anti-inflammatory drug; for patients taking 1∼5 units (tablets/capsules, etc.) per day of a standard-dose combination product containing an opioid analgesic and aspirin, acetaminophen, or a nonsteroidal anti-inflammatory drug, the recommended initial dose is 10∼20 mg of oxycodone hydrochloride every 12 hours. For patients taking 6∼9 units (tablets/capsules, etc.) per day of a standard-dose combination product containing an opioid analgesic and aspirin, acetaminophen, or a nonsteroidal anti-inflammatory drug, the recommended initial dose is 20∼30 mg of oxycodone hydrochloride every 12 hours; for patients taking 10∼12 units (tablets/capsules, etc.) per day, the recommended initial dose is 30∼40 mg of oxycodone hydrochloride every 12 hours. Patients taking opioid analgesics; discontinue the previously administered opioid analgesic when starting treatment with this medicine. The usual initial dose for patients with severe pain not controlled by a weak opioid analgesic is 10mg every 12 hours. Use the standard conversion ratio table (Table 1) to calculate the total daily equivalent dose of oral oxycodone by multiplying the mg/day dose of the previously administered opioid analgesic by the appropriate conversion factor. Divide this daily oxycodone dose into 2 doses to determine the dose to be given every 12 hours. Select the dose according to the oxycodone content of the formulation (10, 15, 20, 30, 40, 60 and 80 mg per tablet). Table 1. Standard conversion ratio table for converting the daily dose of an opioid analgesic being taken to the daily dose of oral oxycodone* (dose of medication being taken mg/day × conversion factor = oral oxycodone dose mg/day) Oral medication being taken / Parenteral medication being taken Oxycodone 1 / - Codeine 0.15 / - Fentanyl TTS see below / see below Hydrocodone 0.9 / - Hydromorphone 4 / 20 Levorphanol 7.5 / 15 Meperidine 0.1 / 0.4 Methadone 1.5 / 3 Morphine 0.5 / 3 Extra caution is needed when switching medications in patients who have been using high doses of parenteral opioid analgesics. For example, for patients who have been receiving high doses of parenteral morphine, use a conversion factor of 1.5 instead of 3. Conversion between oral and parenteral administration of oxycodone: The dose should be based on the following ratio: 2mg of oral oxycodone is equivalent to 1mg of parenteral oxycodone. Conversion from morphine: Oral administration: For patients who took oral morphine before oxycodone treatment, calculate the daily dose based on the following ratio: 10mg of oral oxycodone is equivalent to 15mg or 20mg of oral morphine. Initially, it is recommended that a dose lower than the equivalent dose be administered. Patients using transdermal fentanyl; treatment with this medicine may be started 18 hours after removal of the transdermal fentanyl patch. An appropriate initial oxycodone dose is approximately 10 mg of this medicine every 12 hours for each fentanyl transdermal patch delivering 25㎍/hr. Individual dose adjustment; adjust the dose to achieve an adequate effect (approximately 2 doses of the usual adjunctive analgesic over 24 hours, with mild or no pain). Since plasma drug concentrations reach steady state in approximately 24∼36 hours, the dose should be adjusted every 1∼2 days. When adjusting the dose, it is appropriate to increase the dose administered every 12 hours while keeping the dosing interval unchanged. There are no clinical data for dosing intervals shorter than 12 hours. Except when increasing the dose from 10 mg to 20 mg every 12 hours, guidelines suggest that the total daily dose of oxycodone may generally be increased by 25∼50% of the current dose at each dose increase. If opioid-related adverse effects are observed to be too severe, the next dose may be reduced. Use of 60 mg and 80 mg tablets of this medicine (for use only in patients tolerant to opioid analgesics): Oxycodone doses exceeding 40 mg per dose or 80 mg per day may be taken only by patients tolerant to opioid analgesics. Therefore, the 60 mg and 80 mg tablets of this medicine should be used only in patients tolerant to opioid analgesics, and sufficient caution should be exercised in such cases. Adjunctive analgesic therapy; cancer patients receiving 24-hour treatment with controlled-release opioid analgesics may use immediate-release medication as rescue therapy for breakthrough pain or to prevent pain that predictably occurs during activity. As shown in Table 2, adjunctive analgesics should be prescribed at 1/4∼1/3 of the dose of this medicine administered every 12 hours. Administer the rescue medication at a dose sufficient to treat breakthrough pain, 1 hour before the expected onset of pain. If rescue medication is needed more than 2 times within 24 hours, the dose of this medicine should be increased. Table 2. Appropriate adjunctive analgesic Dose of this medicine administered every 12 hours (mg) / Dose of rescue medication used as needed, immediate-release oxycodone (㎎) 10 / 5 20 / 5 30 / 10 40 / 10 60 / 15 80 / 20 120 / 30 160 / 40 240 / 60 Maintenance therapy: If pain recurs, an increase in the medication dose is needed to control the pain. The dose-adjustment method described above also applies when readjusting the dose to control pain. During ongoing treatment, it is advisable to periodically reassess whether 24-hour continuous therapy is necessary, especially when the pain is not due to cancer (e.g., every 6∼12 months). Treatment goals and discontinuation: For patients who no longer require opioid analgesic therapy, gradual dose reduction is recommended to prevent withdrawal symptoms. Patients with renal impairment and patients with hepatic impairment: The recommended initial dose in adult patients should be reduced by up to 50%. (e.g., the total daily oral dose for patients not taking opioid analgesics is 10mg) Administer with careful titration based on each patient's clinical condition to achieve adequate pain control.
This medication should be swallowed whole and should not be chewed or crushed. Chewing or crushing the tablet can cause the medication to release too quickly, leading to serious side effects, particularly in patients using it for the first time. High-dose formulations of this medication should only be used by patients who are tolerant to opioid analgesics. If a non-tolerant patient uses high doses, it can severely suppress breathing, posing a risk to life. Taking this medication in conjunction with central nervous system depressants or alcohol can cause severe drowsiness, respiratory depression, coma, or even death. Thus, caution is advised when taking it with such substances, and it should be taken at the minimal dose for the shortest duration as directed by a physician. Patients and caregivers should also be well aware of these risk symptoms. This medication should not be administered to patients with specific diseases or those taking certain medications. For example, individuals who are allergic to the medication or have severely impaired respiratory function, severe asthma, gastrointestinal obstruction, severe pulmonary disease, or are taking specific antidepressants should not use it. Patients with weak respiratory function, older adults, and individuals with head injuries may experience exacerbation of side effects such as respiratory depression or hypotension, so utmost care is required when administering this medication. Long-term use of this medication may lead to tolerance, necessitating an increase in dosage to maintain analgesic efficacy, and sudden discontinuation may result in withdrawal symptoms. Therefore, dosages should be reduced gradually. Use of alcohol or other central nervous system depressants concurrently may increase the risk of side effects, so it is advisable not to combine them. This medication may affect the ability to drive or operate machinery, so caution is necessary while taking it. It should only be used during pregnancy when absolutely necessary, and care should be taken around labor and delivery as newborns may experience respiratory depression or withdrawal symptoms. During lactation, avoid breastfeeding while using this medication as it may pass into breast milk and affect the infant. It is not used in children as safety and efficacy have not been established. Elderly patients may have slower drug metabolism, so treatment should start with a reduced dose, and special attention should be paid to side effects. This medication must be taken strictly according to a physician's prescription and should be swallowed whole without cutting, crushing, or chewing, along with water. In cases of overdose, respiratory depression, loss of consciousness, hypotension may occur, requiring immediate emergency treatment. This medication should be kept out of reach of children and stored in its original container to prevent misuse.
Respiratory depression, apnea, respiratory arrest, cardiovascular depression, hypotension, shock, constipation, nausea, drowsiness, dizziness, itching, headache, dry mouth, sweating, weakness, loss of appetite, irritability, insomnia, fever, confusion, diarrhea, abdominal pain, indigestion, erythema, anxiety, dyskinesia, dyspnea, orthostatic hypotension, chills, single contraction, gastritis, strange dreams, abnormal thinking, bronchospasm, increased cough, hiccups, accidental injury, chest pain, facial swelling, discomfort, throat pain, pain, allergic reaction, drug dependence, mydriasis, drug tolerance, anaphylaxis, neonatal drug withdrawal syndrome, migraine, fainting, vasodilation, ST depression, palpitations, ventricular tachycardia, dysphagia, belching, abdominal distension, gastrointestinal disturbance, appetite stimulation, stomatitis, biliary pain, intestinal obstruction, dental caries, cholestasis, elevated liver enzymes, lymphadenopathy, dehydration, edema, hyponatremia, peripheral edema, inappropriate antidiuretic hormone secretion syndrome, thirst, abnormal gait, agitation, forgetfulness, depersonalization, depression, emotional instability, hallucinations, hyperactivity, sensory loss, hypotonia, discomfort, sensory abnormalities, seizures, speech disorder, confusion, tinnitus, tremor, withdrawal symptoms without or with seizures, convulsions, tension and anxiety, involuntary muscle contractions, aggression, hyperalgesia, increased cough, pharyngitis, voice alteration, central sleep apnea syndrome, dry skin, snowfall, urticaria, visual disturbances, taste distortion, amenorrhea, diminished libido, urinary disorders, hematuria, erectile dysfunction, polyuria, urinary retention, urinary disorder, male reproductive gland hypofunction, asphyxia, nausea, reflux, throat obstruction
Not everyone experiences these, and they can vary from person to person.
This medication should be stored in a tightly sealed container to prevent contact with air or moisture and is best kept at room temperature between 1 to 30 degrees Celsius. This will help maintain the effectiveness of the drug and prevent degradation.
Pink, bilayer, convex round extended-release film-coated tablets
30 tablets (10 tablets/PTP packaging X 3)
Even with the same ingredient, strength, dosage form and how it is taken can differ.
Viewing nowOxycodone Hydrochloride 20mg
Tablet · Prescription medication
Korea Mundi Pharma Co., Ltd.

Oxycodone Hydrochloride 10mg
Tablet · Prescription medication
Hanmi Mundipharma Co., Ltd.

Oxycodone Hydrochloride 40mg
Tablet · Prescription medication
Korea Mundipharma Co., Ltd.

Oxycodone Hydrochloride 5mg
Tablet · Prescription medication
Unimed Pharmaceuticals Co., Ltd.
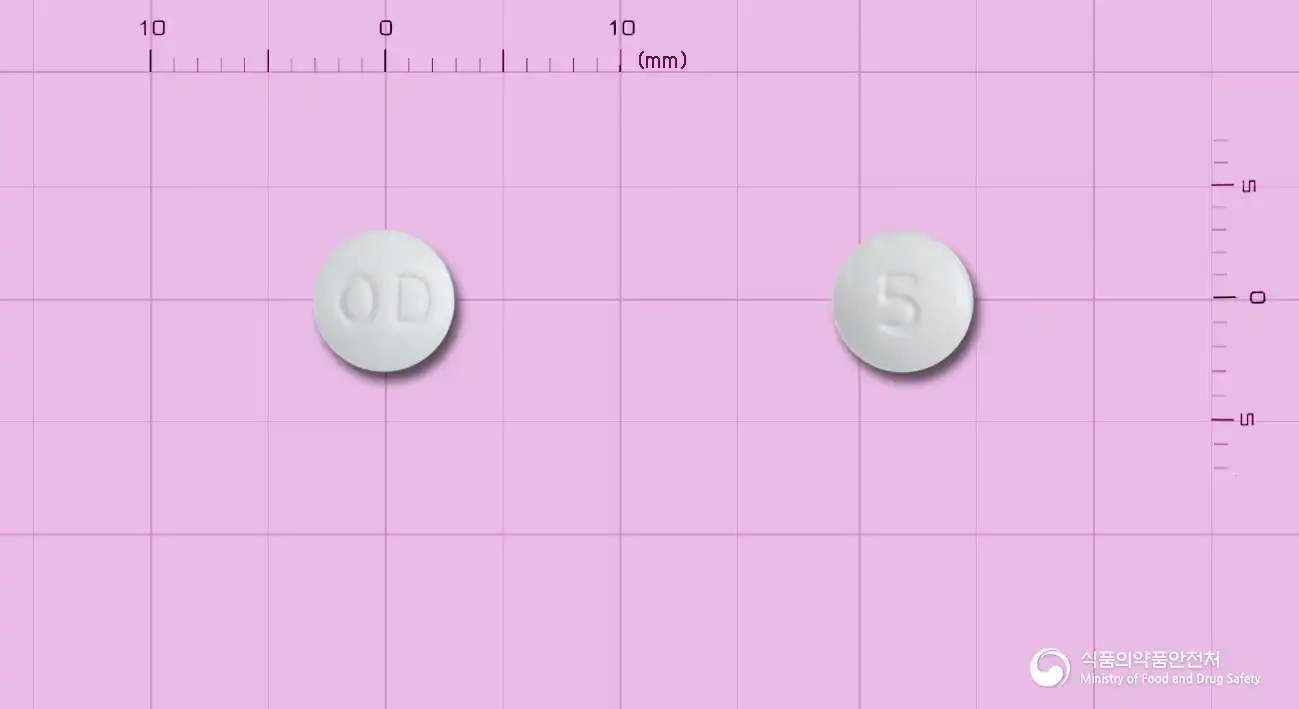
Oxycodone Hydrochloride 5mg
Tablet · Prescription medication
Hana Pharmaceutical Co., Ltd.

Oxycodone Hydrochloride 80mg
Tablet · Prescription medication
Korea Mundi Pharma Co., Ltd.
Oxycodone Hydrochloride 10mg
Solution · Prescription medication
Korea Mundipharma Co., Ltd.
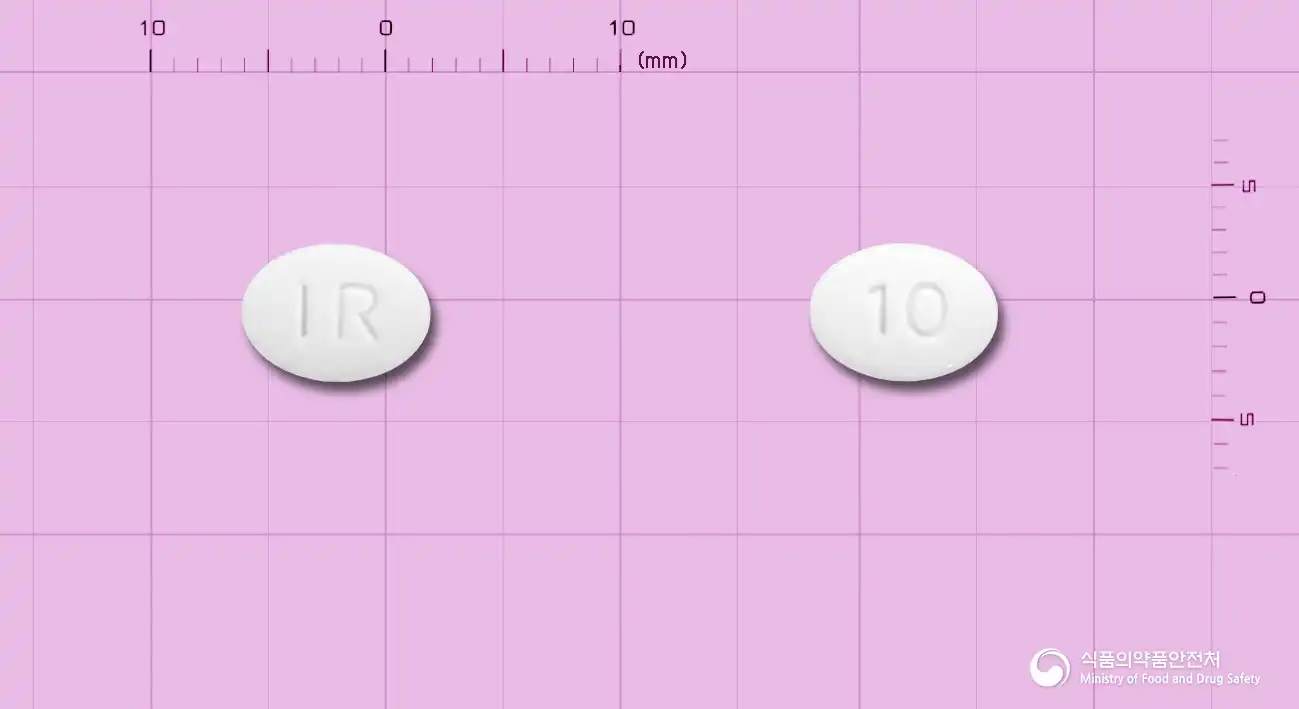
Oxycodone Hydrochloride 10mg
Tablet · Prescription medication
UNIMED PHARMACEUTICAL Co., Ltd.
Even with the same ingredient, the dose and directions can differ by strength and dosage form. Talk to a doctor or pharmacist before switching from a medication you are already taking.
No questions yet.
For anything that needs medical judgment, consult a doctor or pharmacist.
This drug information is based on data provided by the Korea Ministry of Food and Drug Safety.
Consult a doctor or pharmacist for accurate dosage, administration, and usage instructions.