
 한국어
 English
 日本語
 中文(简体)
 Viewing now
Rivaxan 15 mg (Rivaroxaban)
Rivaroxaban 15mg
Tablet · Prescription medication
Jeil Pharmaceutical Co., Ltd.
MFDS item code 202102482 · Approved 2021.03.22 · Insurance code 645405850
Prevention of embolism in atrial fibrillation, treatment and prevention of recurrence of venous thromboembolism, and prevention of postoperative thrombosis
This medication is used to reduce the risk of stroke and systemic embolism in patients with non-valvular atrial fibrillation. It is also effective in treating venous thromboembolism and pulmonary embolism, and in reducing the risk of recurrence of these conditions. Furthermore, it is utilized to prevent venous thromboembolism after major orthopedic surgeries of the legs. Overall, it is used for the prevention and treatment of thrombo-related diseases to improve patients' health.
This medicine 10 mg may be taken with or without food, while 15 mg and 20 mg should be taken with food. 1) Reduction of the risk of stroke and systemic embolism in patients with nonvalvular atrial fibrillation The recommended dose of this medicine is 20 mg once daily. The recommended dose for patients with moderate renal impairment (creatinine clearance 30-49 mL/min) is 15 mg once daily. The maximum daily dose of this medicine is 20 mg. There is limited experience with concomitant administration of rivaroxaban 15 mg once daily [10 mg once daily for patients with moderate renal impairment (creatinine clearance 30-49 mL/min)] and a P2Y12 inhibitor for up to 12 months in patients with nonvalvular atrial fibrillation who have undergone percutaneous coronary intervention (PCI) with stent placement. (See '12. Clinical Trial Information') 2) Treatment of deep vein thrombosis and pulmonary embolism / Reduction of the risk of recurrence of deep vein thrombosis and pulmonary embolism The recommended initial dose of this medicine for the treatment of acute deep vein thrombosis and pulmonary embolism is 15 mg twice daily for the first 3 weeks. Thereafter, the recommended maintenance dose for the treatment of deep vein thrombosis and pulmonary embolism and the recommended dose for reducing the risk of recurrence are 20 mg once daily. After completion of treatment (at least 6 months) for deep vein thrombosis or pulmonary embolism, the recommended dose for extended treatment to reduce the risk of recurrence is 10mg once daily. The duration of treatment and dose should be determined following an individual assessment of the risk of recurrence of deep vein thrombosis and pulmonary embolism versus the risk of bleeding. Treatment period / Dosing frequency / Daily dose Treatment of deep vein thrombosis or pulmonary embolism and reduction of the risk of recurrence Days 1-21 / 15mg twice daily / 30mg From day 22 / 20mg once daily / 20mg Reduction of the risk of recurrence of deep vein thrombosis or pulmonary embolism After at least 6 months of treatment / 10mg once daily / 10mg The maximum daily dose of this medicine is 30 mg during the first 3 weeks of treatment and 20 mg thereafter. 3) Prevention of venous thromboembolism in adult patients undergoing major orthopedic surgery of the lower limbs (knee or hip replacement) The recommended dose of this medicine is 10 mg once daily. The first dose should be started 6~10 hours after surgery, once hemostasis has been confirmed. The duration of treatment depends on each patient's risk of venous thromboembolism based on the type of surgery; however, a treatment duration of 5 weeks is recommended for patients undergoing hip replacement and 2 weeks for patients undergoing knee replacement. 4) If you forget to take this medicine If you forget to take this medicine, take the missed dose as follows. ① Patients taking 15 mg twice daily: Take this medicine immediately; in this case, 2 tablets of 15 mg may be taken at once. Starting the next day, continue taking 15 mg twice daily. ② Patients taking 10, 15, or 20 mg once daily: Take the missed dose immediately. Starting the next day, continue taking 1 tablet once daily. The daily dose should not be doubled to make up for a missed dose. 2. Switching medications 1) Switching from a vitamin K antagonist to this medicine ① Reduction of the risk of stroke and systemic embolism in patients with nonvalvular atrial fibrillation Treatment with the vitamin K antagonist should be discontinued, and this medicine should be started when the international normalized ratio (INR, International Normalized Ratio) is ≤ 3.0. ② Treatment of deep vein thrombosis and pulmonary embolism / Reduction of the risk of recurrence of deep vein thrombosis and pulmonary embolism Treatment with the vitamin K antagonist should be discontinued, and this medicine should be started when the INR is ≤ 2.5. Regardless of the dose, the INR value will be falsely elevated after taking this medicine. The INR is not suitable for measuring the anticoagulant activity of this medicine and should not be used for this purpose. 2) Switching from this medicine to a vitamin K antagonist Inadequate anticoagulation may occur when switching from this medicine to a vitamin K antagonist. Adequate anticoagulation should be maintained continuously when switching to another anticoagulant. Note that this medicine may affect the increase in INR. Patients switching from this medicine to a vitamin K antagonist should receive both medicines until the INR is ≥2.0. During the first 2 days after switching, administer the standard dose of the vitamin K antagonist, and thereafter administer the dose of the vitamin K antagonist according to INR testing. However, in patients receiving this medicine together with a vitamin K antagonist, INR testing should not be performed until 24 hours after taking this medicine. Once this medicine is discontinued, INR testing may be performed 24 hours after the last dose. 3) Switching from a parenteral anticoagulant to this medicine In patients receiving a parenteral anticoagulant, start this medicine 0~2 hours before the next scheduled dose of the parenteral agent (e.g., low-molecular-weight heparin), or at the time a continuously administered parenteral agent (e.g., intravenous unfractionated heparin) is discontinued. 4) Switching from this medicine to a parenteral anticoagulant Discontinue this medicine and start the parenteral anticoagulant at the time the next dose of this medicine would have been due. 3. Patients with renal impairment No dose adjustment is necessary in patients with mild renal impairment (creatinine clearance 50-80 mL/min). Based on limited clinical experience in patients with severe renal impairment (creatinine clearance 15-29 mL/min), blood concentrations of this medicine were significantly increased; therefore, this medicine should be administered with caution. There is no clinical experience in patients with severe renal impairment with creatinine clearance less than 15 mL/min, and use of this medicine is not recommended. 1) Reduction of the risk of stroke and systemic embolism in patients with nonvalvular atrial fibrillation The recommended dose for patients with moderate renal impairment (creatinine clearance 30-49 mL/min) and severe renal impairment (creatinine clearance 15-29 mL/min) is 15 mg once daily. 2) Treatment of deep vein thrombosis and pulmonary embolism / Reduction of the risk of recurrence of deep vein thrombosis and pulmonary embolism / Prevention of venous thromboembolism in adult patients undergoing major orthopedic surgery of the lower limbs (knee or hip replacement) No dose adjustment is necessary in patients with moderate renal impairment (creatinine clearance 30-49 mL/min). 4. Patients with hepatic impairment Avoid administering this medicine to patients with liver disease associated with coagulopathy and to patients with moderate (Child Pugh B) or severe (Child Pugh C) hepatic impairment. Increased exposure to this medicine and an increased risk of bleeding may occur in these patients. 5. Patients who are unable to swallow tablets, Immediately before use, this medicine may be crushed and mixed with water or a beverage such as applesauce for oral administration. This medicine may also be crushed and administered with a small amount of water through a gastrointestinal tube. Before administering this medicine through a gastrointestinal tube, confirm that the tube is correctly positioned, and flush the tube with water after administration.
This drug is an anticoagulant used to prevent or treat thrombus formation by inhibiting blood coagulation. Careful monitoring for signs of bleeding is required while taking this medication, and it should be administered with caution to patients at high risk of bleeding. If severe bleeding occurs, medication should be discontinued immediately, and medical consultation should be sought. This medication should not be given to patients with certain diseases or conditions, such as those with severe bleeding, significantly impaired liver function, pregnant or breastfeeding women, or those with specific genetic disorders. Caution is also needed when used in patients with renal impairment or diseases with a high risk of bleeding, and when taken with certain medications. Various adverse reactions may occur, including bleeding, anemia, gastrointestinal disorders, skin rash, liver function abnormalities, etc., so it is important to inform healthcare providers immediately if symptoms appear. Older adults or patients with renal impairment may have increased drug concentrations, raising the risk of bleeding, necessitating careful management. This medication may interact with other drugs, so patients should inform their healthcare providers of all medications being taken. Use is not recommended in pregnant or breastfeeding women, and women of childbearing age should ensure appropriate contraception while taking this medication. If surgery or invasive procedures are planned, patients should notify their healthcare providers prior to taking this medication, as there may be a need to discontinue use for a certain period before the procedure. Caution is required as symptoms such as drowsiness or fainting may occur when driving or operating machinery. The risk of bleeding may sharply increase with an overdose, so it is essential to adhere strictly to the prescribed dosage and consult medical professionals if any unusual symptoms arise.
Hemorrhage, anemia, thrombocytosis, tachycardia, ocular hemorrhage, gingival bleeding, gastrointestinal bleeding, abdominal pain, dyspepsia, nausea, constipation, diarrhea, vomiting, dry mouth, fever, peripheral edema, generalized decrease in strength and energy, discomfort, localized edema, liver dysfunction, jaundice, allergic reactions, allergic dermatitis, post-treatment bleeding, bruising, wound exudate, vascular pseudoaneurysm, increased transaminases, elevated serum bilirubin, increased alkaline phosphatase, elevated LDH, increased lipase, increased amylase, elevated enzyme levels, increased bilirubin conjugates, limb pain, hemorrhagic arthropathy, muscle bleeding, dizziness, headache, cerebral and intracranial hemorrhage, syncope, urogenital bleeding, renal impairment, non-bleeding, hemoptysis, itching, rash, petechial hemorrhage, skin and subcutaneous bleeding, urticaria, hypotension, hematoma, angioedema, allergic edema, anaphylactic shock, cholestasis, hepatitis, thrombocytopenia, agranulocytosis, Stevens-Johnson syndrome, toxic epidermal necrolysis, eosinophilia, drug reactions with systemic symptoms, eosinophilic pneumonia, anticoagulant-related kidney disease, significant uterine bleeding, syncope, drowsiness
Not everyone experiences these, and they can vary from person to person.
This medication should be stored in a tightly sealed container to protect it from exposure to air or moisture. It is best to maintain storage temperatures between 1 and 30 degrees Celsius.
Red round film-coated tablet
30 tablets/PTP [30 tablets (10 tablets/PTP packaging X 3)]
Even with the same ingredient, strength, dosage form and how it is taken can differ.
Viewing nowRivaroxaban 15mg
Tablet · Prescription medication
Jeil Pharmaceutical Co., Ltd.

Rivaroxaban 2.5mg
Tablet · Prescription medication
Hanmi Pharmaceutical Co., Ltd.

Rivaroxaban 10mg
Tablet · Prescription medication
Hanmi Pharmaceutical Co., Ltd.
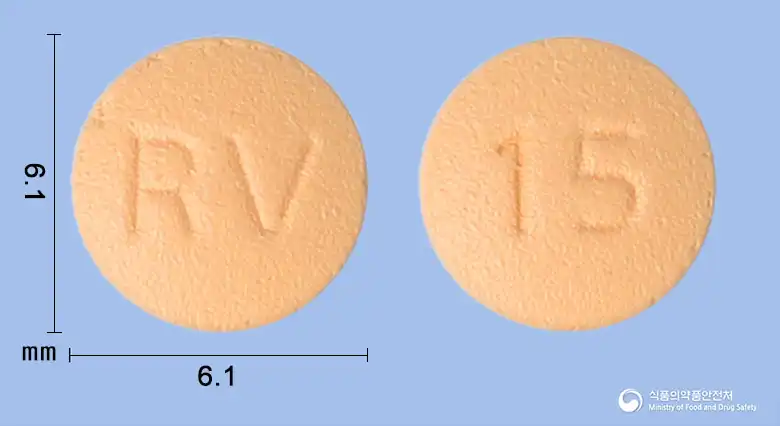
Rivaroxaban 15mg
Tablet · Prescription medication
Hanmi Pharmaceutical Co., Ltd.
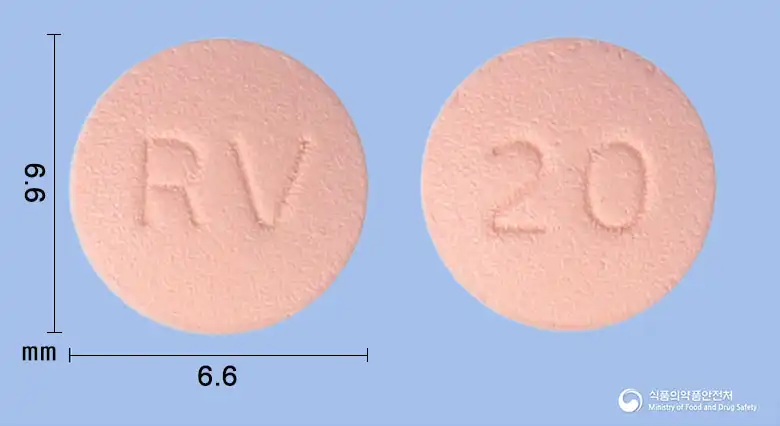
Rivaroxaban 20mg
Tablet · Prescription medication
Hanmi Pharmaceutical Co., Ltd.

Rivaroxaban 20mg
Tablet · Prescription medication
Jongkundang Co., Ltd.

Rivaroxaban 10mg
Tablet · Prescription medication
Jongkundang Co., Ltd.

Rivaroxaban 15mg
Tablet · Prescription medication
Jongkundang Co., Ltd.
Even with the same ingredient, the dose and directions can differ by strength and dosage form. Talk to a doctor or pharmacist before switching from a medication you are already taking.
No questions yet.
For anything that needs medical judgment, consult a doctor or pharmacist.
This drug information is based on data provided by the Korea Ministry of Food and Drug Safety.
Consult a doctor or pharmacist for accurate dosage, administration, and usage instructions.